Differentiation of autoimmune pancreatitis from pancreatic adenocarcinoma using CT characteristics: a systematic review and meta-analysis
Related Experiment Video For Autoimmune pancreatitis
Updated: Jul 23, 2025
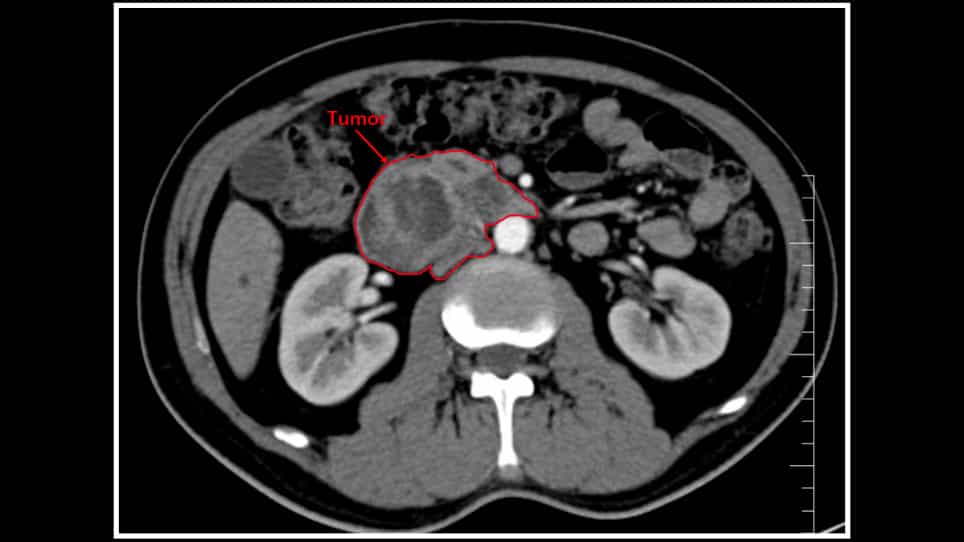
Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Seung Bae Yoon1, Tae Yeon Jeon2, Sung-Hoon Moon3
1Department of Internal Medicine, College of Medicine, The Catholic University of Korea, Seoul, South Korea.

Objectives:
To determine informational CT findings for distinguishing autoimmune pancreatitis (AIP) from pancreatic ductal adenocarcinoma (PDAC) and to review their diagnostic accuracy.
Methods:
A systematic and detailed literature review was performed through PubMed, EMBASE, and the Cochrane library. Similar descriptors to embody the identical image finding were labeled as a single CT characteristic. We calculated the pooled diagnostic odds ratios (DORs) of each CT characteristic using a bivariate random-effects model.
Results:
A total of 145 various descriptors from 15 studies (including 562 AIP and 869 PDAC patients) were categorized into 16 CT characteristics. According to the pooled DOR, 16 CT characteristics were classified into three groups (suggesting AIP, suggesting PDAC, and not informational). Seven characteristics suggesting AIP were diffuse pancreatic enlargement (DOR, 48), delayed homogeneous enhancement (DOR, 46), capsule-like rim (DOR, 34), multiple pancreatic masses (DOR, 16), renal involvement (DOR, 15), retroperitoneal fibrosis (DOR, 13), and bile duct involvement (DOR, 8). Delayed homogeneous enhancement showed a pooled sensitivity of 83% and specificity of 85%. The other six characteristics showed relatively low sensitivity (12-63%) but high specificity (93-99%). Four characteristics suggesting PDAC were discrete pancreatic mass (DOR, 23), pancreatic duct cutoff (DOR, 16), upstream main pancreatic duct dilatation (DOR, 8), and upstream parenchymal atrophy (DOR, 7).
Conclusion:
Eleven CT characteristics were informational to distinguish AIP from PDAC. Diffuse pancreatic enlargement, delayed homogeneous enhancement, and capsule-like rim suggested AIP with the highest DORs, whereas discrete pancreatic mass suggested PDAC. However, pooled sensitivities of informational CT characteristics were moderate.
Clinical Relevance Statement:
This meta-analysis underscores eleven distinctive CT characteristics that aid in differentiating autoimmune pancreatitis from pancreatic adenocarcinoma, potentially preventing misdiagnoses in patients presenting with focal/diffuse pancreatic enlargement.
Key Points:
• Diffuse pancreatic enlargement (pooled diagnostic odds ratio [DOR], 48), delayed homogeneous enhancement (46), and capsule-like rim (34) were CT characteristics suggesting autoimmune pancreatitis. • The CT characteristics suggesting autoimmune pancreatitis, except delayed homogeneous enhancement, had a general tendency to show relatively low sensitivity (12-63%) but high specificity (93-99%). • Discrete pancreatic mass (pooled diagnostic odds ratio, 23) was the CT characteristic suggesting pancreatic ductal adenocarcinoma with the highest pooled DORs.

Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management