Related Experiment Video
Updated: Aug 19, 2026

RNAscope for In situ Detection of Transcriptionally Active Human Papillomavirus in Head and Neck Squamous Cell Carcinoma
Published on: March 11, 2014
The pathology of vulvar squamous cell carcinoma and verrucous carcinoma

Abstract:
Squamous cell carcinoma is far more common than verrucous carcinoma in the vulva. The clinical and morphologic distinctions between these neoplasms are important to understand because of their contrasting biologic behavior and treatment. Both cancers present with symptoms of pruritus and a noticeable mass. On examination, both tumors commonly occur on the labia and are exophytic. If infection occurs in association with verrucous carcinoma, the resulting induration of the surrounding tissue as well as reactive regional lymph node enlargement may fool the clinician into making an erroneous diagnosis of advanced squamous cell carcinoma. In the 33 percent of cases in which a squamous cell carcinoma is flat and ulcerated, the gross distinction from verrucous carcinoma is easy to perceive. The microscopic analysis of squamous cell carcinomas should specify the neoplastic thickness, depth of stromal invasion, and presence or absence of lymphatic invasion since these parameters are important in predicting the probability of lymph node metastases in superficially invasive cancers. Verrucous carcinomas are thick neoplasms which may invade and compress the underlying stroma with "pushing" margins. It is therefore crucial to recognize the microscopic features of this well-differentiated squamous neoplasm in order not to mistake it for a squamous cell carcinoma which has the capacity to metastasize to inguinal lymph nodes. Human papilloma virus has been implicated in the development of both of these tumors. The treatment for verrucous carcinoma is wide local excision. Because recurrence may occur if the surgical resection margins are involved by the neoplasm, the pathologist must carefully evaluate these margins. It is important to note that recurrence of verrucous carcinoma connotes a poor prognosis. The treatment of a squamous cell carcinoma which is thicker than 2 mm or has a stromal invasion depth of more than 1 mm is vulvectomy and bilateral lymph node dissection. If the neoplasm is less than 2 mm in thickness, regional lymph node metastases have not been reported and lymph node dissection may not be necessary. The best treatment option is wide local excision and close follow-up. As our understanding of superficially invasive vulvar squamous cell carcinoma continues to evolve, however, these recommendations may change.
More Related Videos
 07:43
Four-color Fluorescence Immunohistochemistry of T-cell Subpopulations in Archival Formalin-fixed, Paraffin-embedded Human Oropharyngeal Squamous Cell Carcinoma Samples
Published on: July 29, 2017
 06:15
Anterior High-Resolution Optical Coherence Tomography in the Diagnosis and Therapeutic Monitoring of Ocular Surface Squamous Neoplasia
Published on: August 9, 2024
Related Concept Videos
 01:03
Rous Sarcoma Virus (RSV) and Cancer
RSV is a retrovirus that contains two copies of a plus-strand RNA genome. Its genome consists of four main open...
01:03Rous Sarcoma Virus (RSV) and Cancer
RSV is a retrovirus that contains two copies of a plus-strand RNA genome. Its genome consists of four main open...
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 01:23
Genital Herpes
 01:20
Candidiasis
 01:24
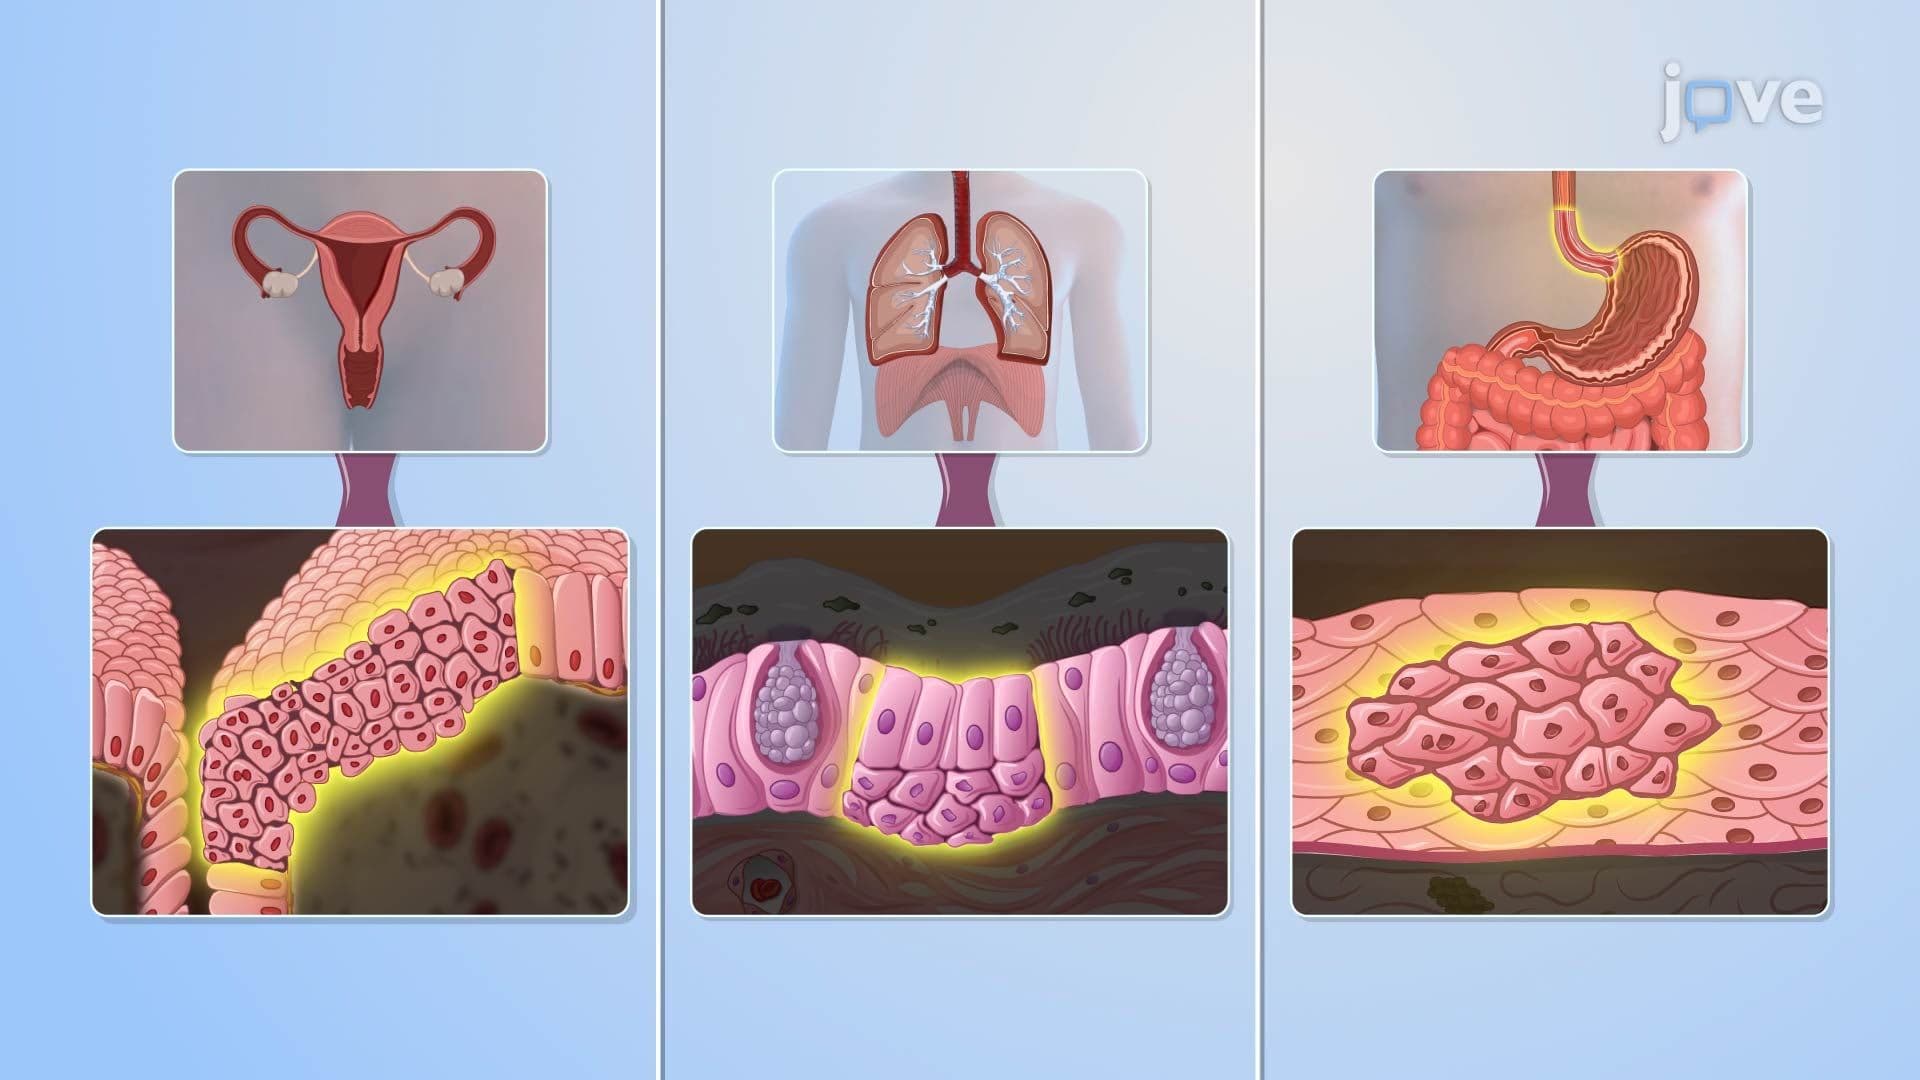
Cellular Adaptation IV: Dysplasia and Metaplasia