Related Experiment Video
Updated: Jul 21, 2025


Induction of Nephrotic Syndrome in Mice by Retrobulbar Injection of Doxorubicin and Prevention of Volume Retention by Sustained Release Aprotinin
Published on: May 6, 2018
Deruxtecan-Induced Reversible Fanconi Syndrome
Pooja Kalantri1, Koba Lomashvili1
1General Nephrology, Emory University, Atlanta, USA.

Abstract:
Increasingly complex and constantly emerging cancer treatment protocols are associated with kidney toxicities. Data clearly demonstrate that when patients with cancer develop acute or chronic kidney disease, severe fluid and electrolyte abnormalities, outcomes are inferior, and the promise of curative therapeutic regimens is lessened. We present a case of a 74-year-old woman with metastatic, recurrent ER+/PR-/HER2+ invasive ductal carcinoma of the right breast, status post bilateral mastectomies, chemotherapy, radiation therapy, and hormonal therapies, who were clinically stable on Trastuzumab/Pertuzumab maintenance for about a year. She then experienced disease progression. She was started on Trastuzumab+Deruxtecan (T-Dxt). However, due to worsening diarrhea of more than 12 episodes per day, decreased oral intake, weakness and weight loss, she got admitted to the hospital. Laboratory data showed hyponatremia, hypokalemia, non-anion gap metabolic acidosis, hypomagnesemia, and hypophosphatemia. These laboratory abnormalities were initially attributed to diarrhea. Renal losses were suspected when the electrolyte abnormalities did not correct despite improving diarrhea. Urine electrolytes were hence tested. There was evidence of Fanconi syndrome with glucosuria, proteinuria, and renal potassium and phosphorus wasting. Fanconi syndrome was attributed to the Deruxtecan component of the combination chemotherapy, as she was previously on Trastuzumab with no such abnormalities. The electrolyte abnormalities resolved over the course of a few months. To our knowledge, this is the first case of Fanconi syndrome due to T-Dxt.


Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:30
Continuous Renal Replacement Therapy
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:15
Renal Drug Excretion: Overview
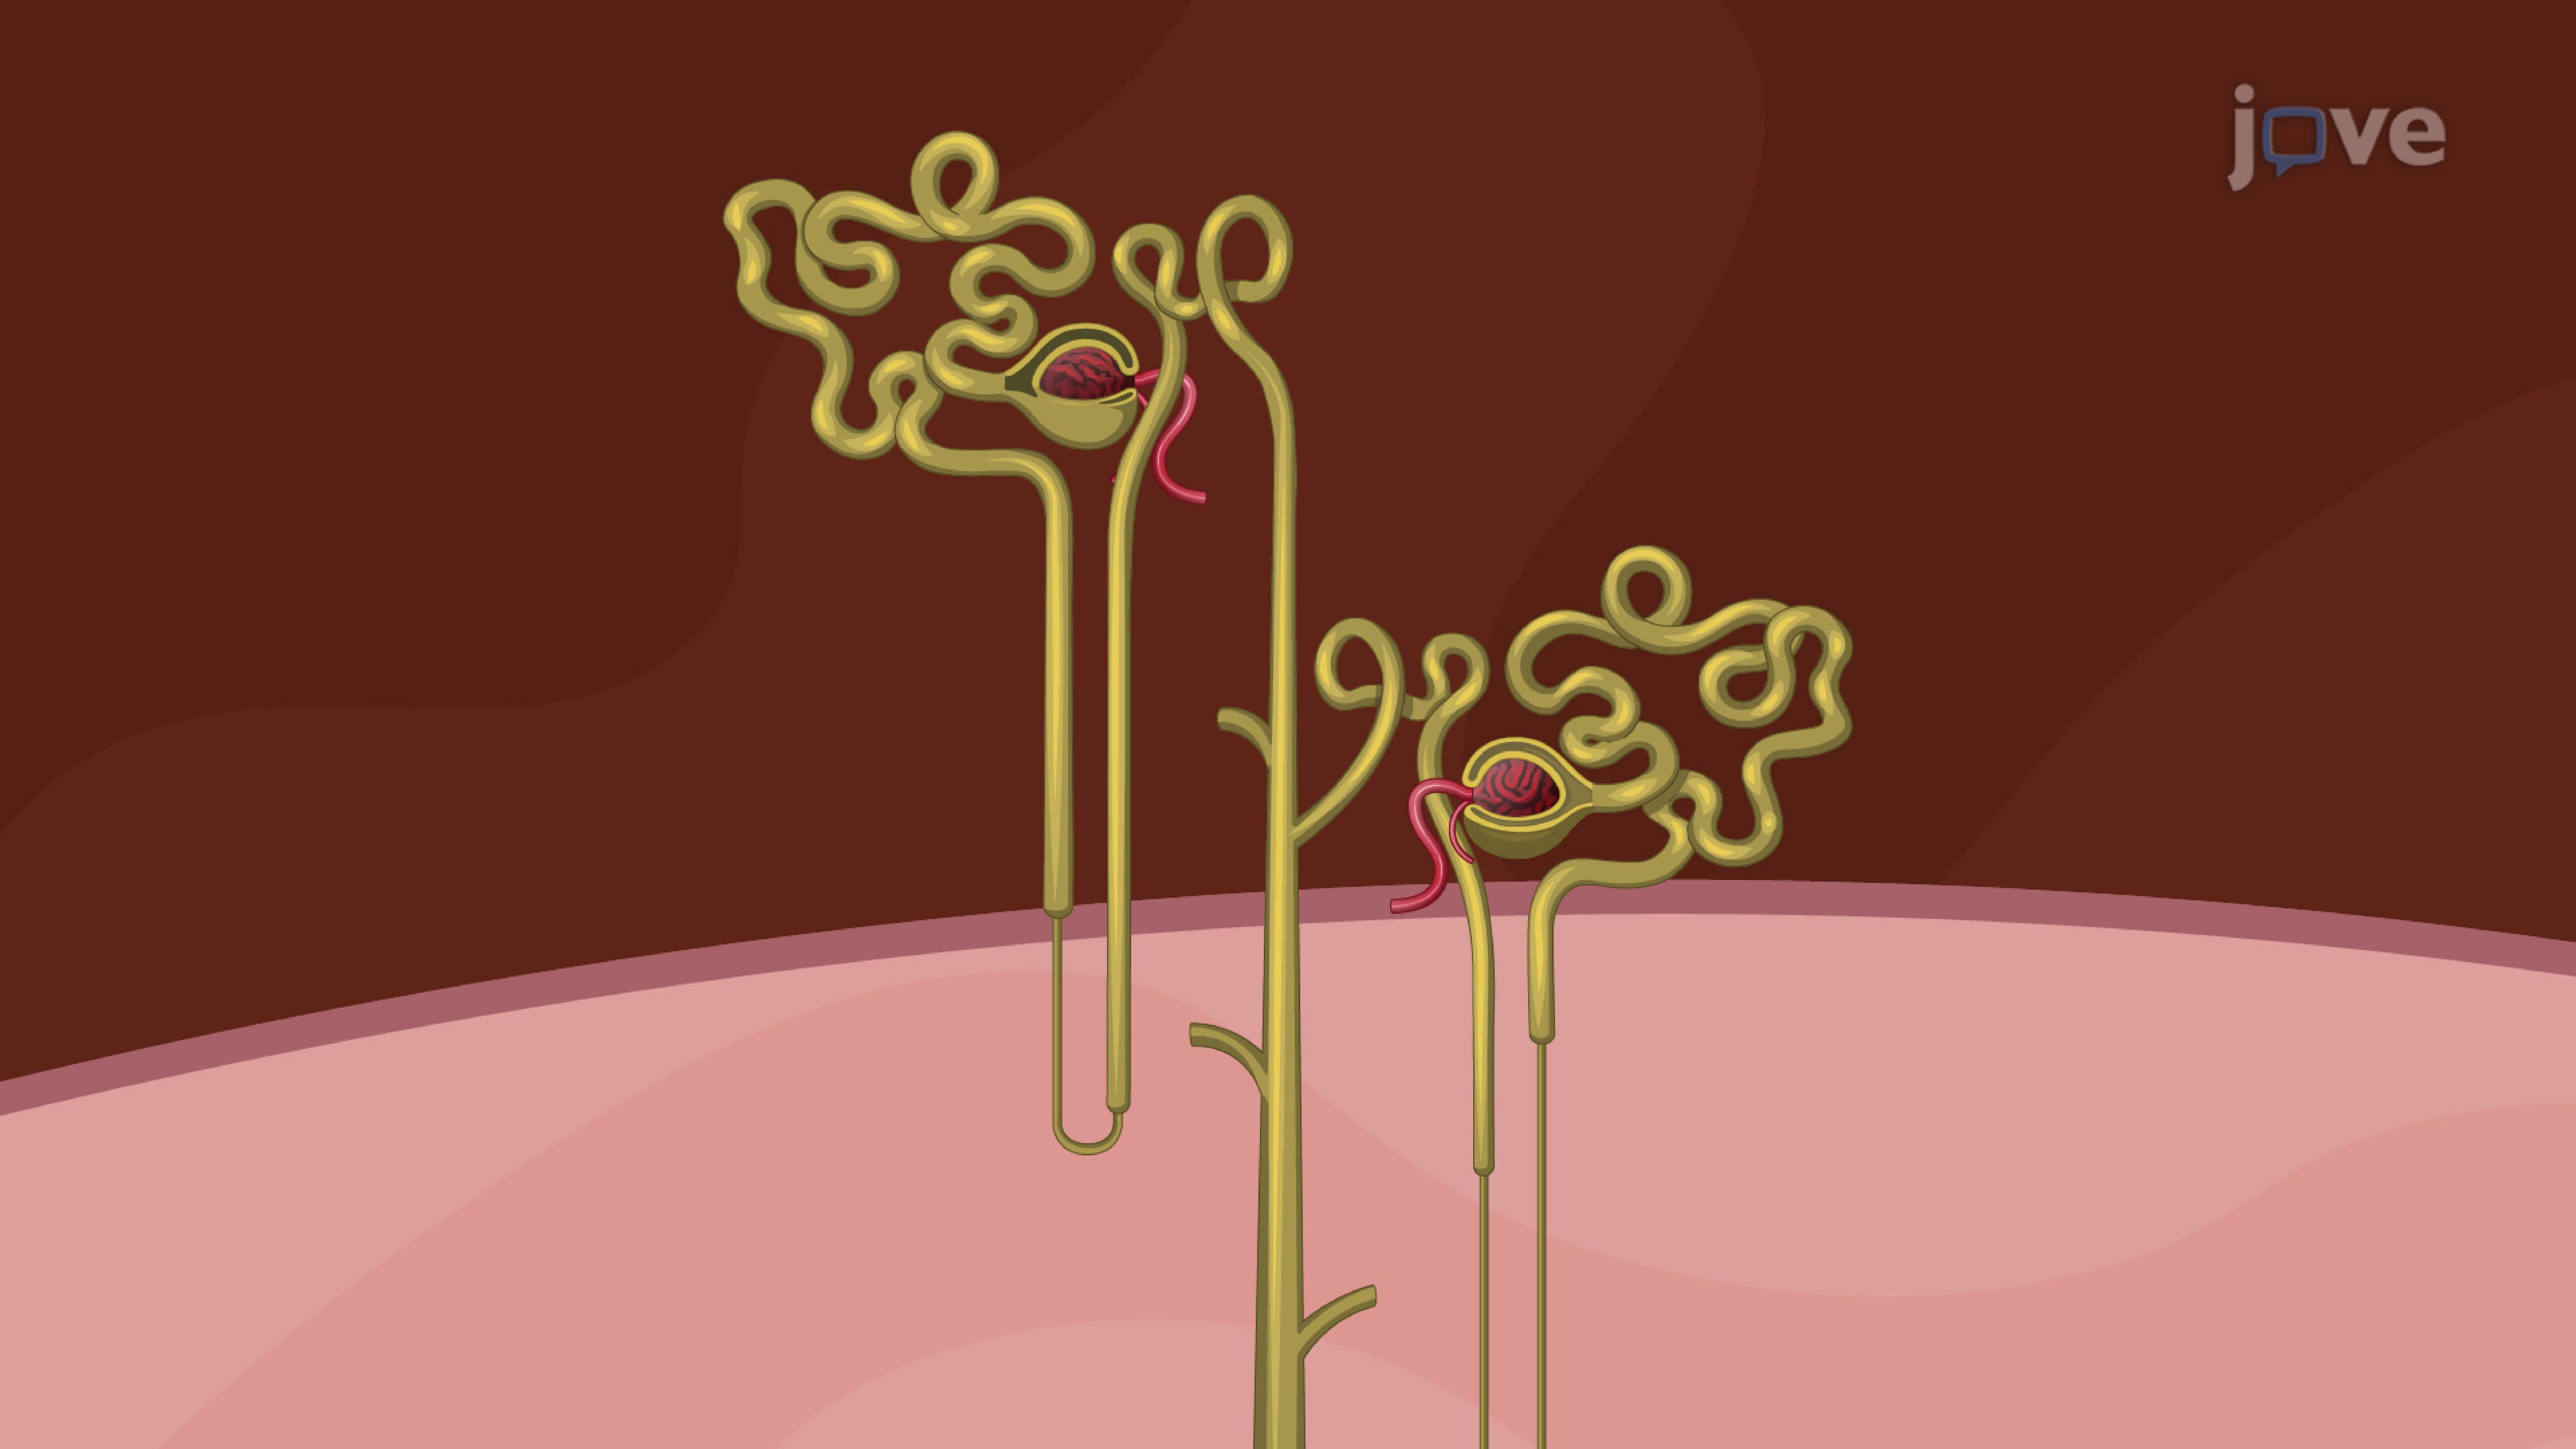
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...