

Activation recovery interval as an electrocardiographic repolarization index to detect doxorubicin-induced
Toshio Kinoshita1, Naoki Onda2, Ruiko Ohno1
1Division of Cardiovascular Medicine, Department of Internal Medicine, Toho University Sakura Medical Center, Chiba, Japan.

Background:
It has been reported that early detection and treatment of cancer therapy- related cardiac dysfunction (CTRCD) improves its prognosis. The detailed relationships between electrocardiographic repolarization indices and decreased left ventricular function in CTRCD have not been elucidated. We closely assessed such relationships in patients with doxorubicin (DOX)-induced CTRCD.
Methods:
This retrospective, single-center, cohort study included 471 consecutive patients with malignant lymphoma who received chemotherapy including DOX. Of them, 17 patients with CTRCD and 68 patients without CTRCD who underwent 12‑lead electrocardiogram and an echocardiogram before and after chemotherapy were eventually analyzed. The fluctuations of the following electrocardiographic repolarization indices were evaluated in lead V5: QT, JT, T peak to T end interval (Tp-e), and activation recovery interval (ARI). These indices were corrected by heart rate with the Fridericia formula.
Results:
The median period from the end of chemotherapy to the diagnosis of the CTRCD group was 346 days (IQR 170-1283 days). After chemotherapy, the QT interval was significantly prolonged in both with and without CTRCD groups compared with that before chemotherapy (pre QTc vs. post QTc in CTRCD group, 386 ± 27 ms vs. 411 ± 37 ms, p = 0.03, pre QTc vs. post QTc in non-CTRCD group, 388 ± 24 ms vs. 395 ± 25 ms, p = 0.04, respectively). ARIc after chemotherapy was characteristically observed only in the CTRCD group (pre ARIc vs. post ARIc in CTRCD group, 258 ± 53 ms vs. 211 ± 28 ms, p = 0.03, pre ARIc vs. post ARIc in non-CTRCD group, 221 ± 19 ms vs. 225 ± 23 ms, NS, respectively) and had negative correlations with left ventricular ejection fraction (r = -0.56, p < 0.001). Using the receiver-operating characteristic curve, the relationship between ARIc and CTRCD morbidity was examined. The optimal cut-off point of ARIc prolongation between before and after chemotherapy was 18 ms (sensitivity 75 %, specificity 79 %, area under the curve 0.76).
Conclusions:
ARIc prolongation may be useful in the early detection of developing late-onset chronic DOX-induced CTRCD and lead to early treatment for cardiac protection.

Related Concept Videos
 01:30
Cardiac Action Potential
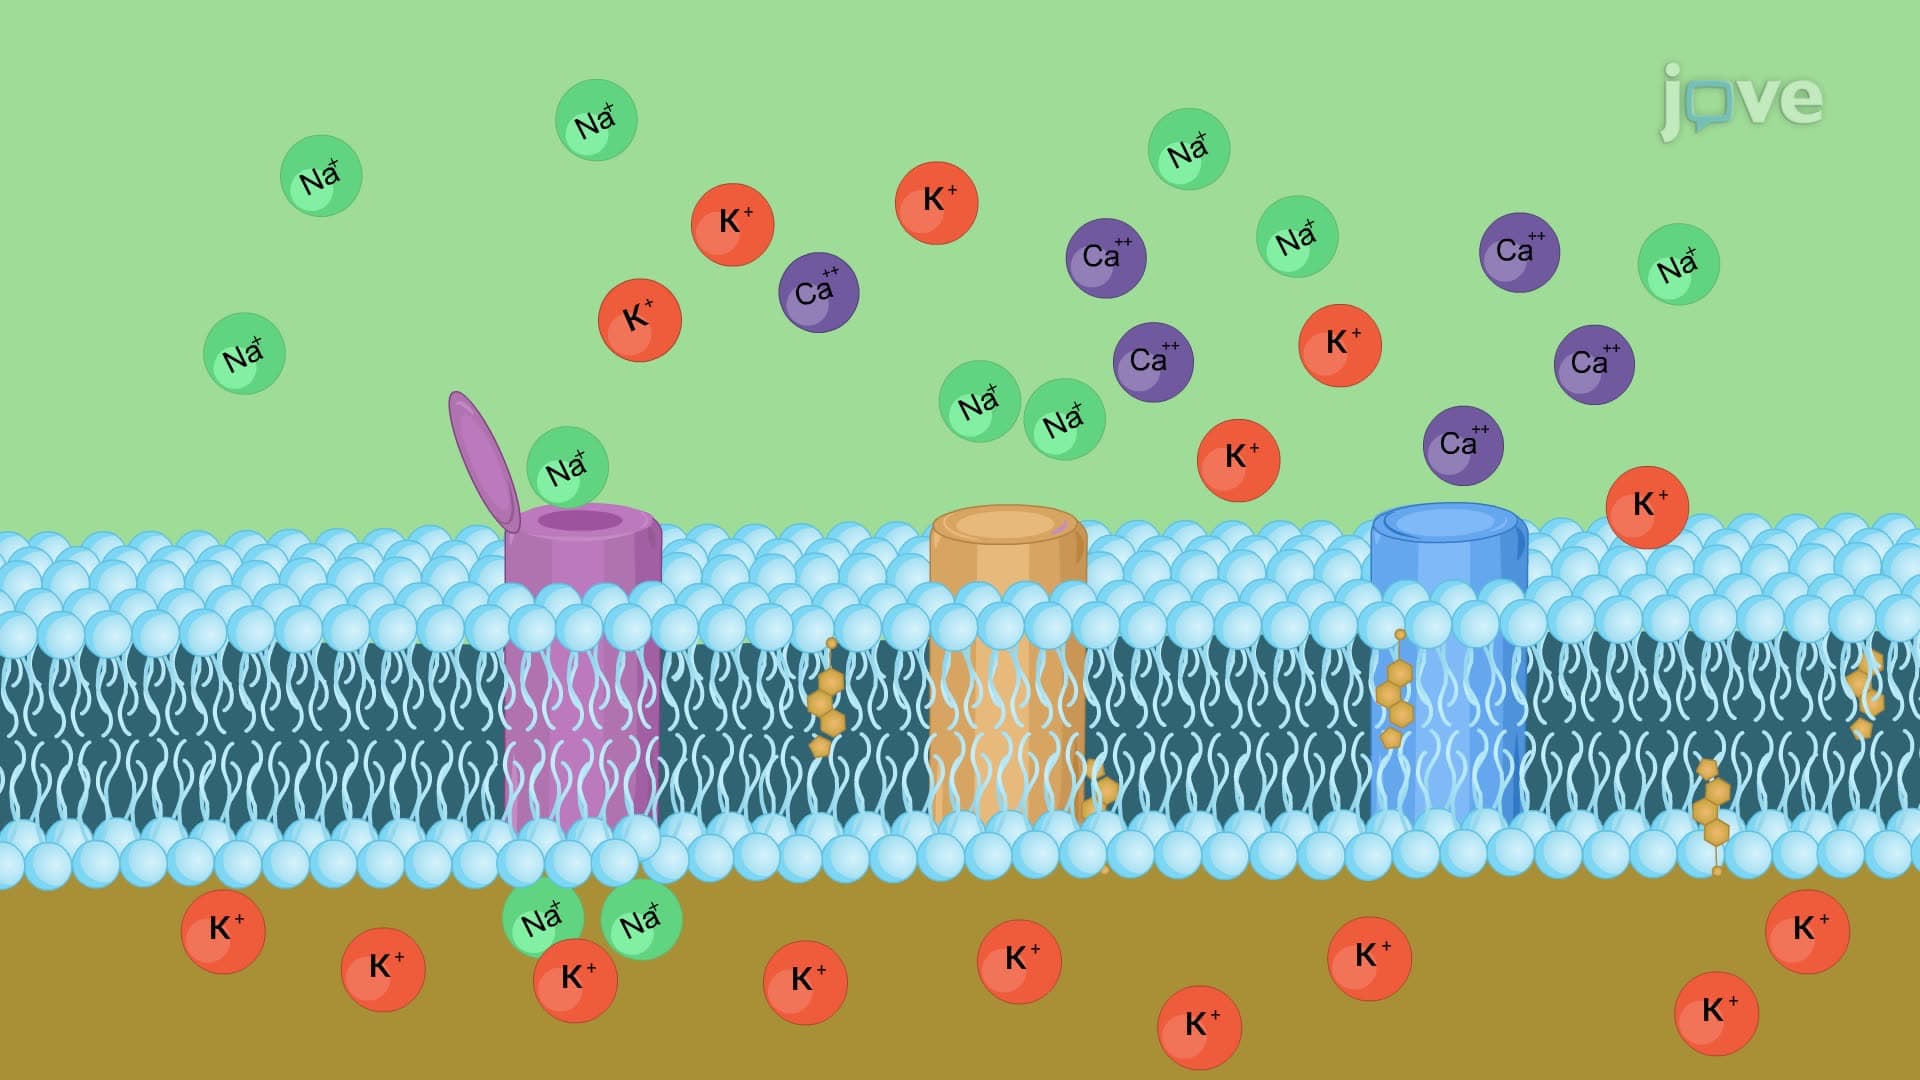
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:23
Cardiopulmonary Resuscitation III: AED Use