Related Experiment Video
Updated: Jul 20, 2025


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Characterization of sound pressure levels and sound sources in the intensive care unit: a 1 week observational study
Aileen C Naef1, Samuel E J Knobel1, Nicole Ruettgers1
1Gerontechnology and Rehabilitation Group, ARTORG Center for Biomedical Engineering Research, University of Bern, Murtenstrasse, Bern, Switzerland.

Background:
Exposure to elevated sound pressure levels within the intensive care unit is known to negatively affect patient and staff health. In the past, interventions to address this problem have been unsuccessful as there is no conclusive evidence on the severity of each sound source and their role on the overall sound pressure levels. Therefore, the goal of the study was to perform a continuous 1 week recording to characterize the sound pressure levels and identify negative sound sources in this setting.
Methods:
In this prospective, systematic, and quantitative observational study, the sound pressure levels and sound sources were continuously recorded in a mixed medical-surgical intensive care unit over 1 week. Measurements were conducted using four sound level meters and a human observer present in the room noting all sound sources arising from two beds.
Results:
The mean 8 h sound pressure level was significantly higher during the day (52.01 ± 1.75 dBA) and evening (50.92 ± 1.66 dBA) shifts than during the night shift (47.57 ± 2.23; F(2, 19) = 11.80, p < 0.001). No significant difference was found in the maximum and minimum mean 8 h sound pressure levels between the work shifts. However, there was a significant difference between the two beds in the based on location during the day (F(3, 28) = 3.91, p = 0.0189) and evening (F(3, 24) = 5.66, p = 0.00445) shifts. Cleaning of the patient area, admission and discharge activities, and renal interventions (e.g., dialysis) contributed the most to the overall sound pressure levels, with staff talking occurring most frequently.
Conclusion:
Our study was able to identify that continuous maintenance of the patient area, patient admission and discharge, and renal interventions were responsible for the greatest contribution to the sound pressure levels. Moreover, while staff talking was not found to significantly contribute to the sound pressure levels, it was found to be the most frequently occurring activity which may indirectly influence patient wellbeing. Overall, identifying these sound sources can have a meaningful impact on patients and staff by identifying targets for future interventions, thus leading to a healthier environment.
More Related Videos
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
 06:04
Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
Related Concept Videos
 00:53
Sound Intensity Level
The human ear can perceive an extensive range of sound intensity, necessitating the use of the logarithmic scale to define a physical quantity—the intensity level. It is a ratio of two intensities and...
 01:05
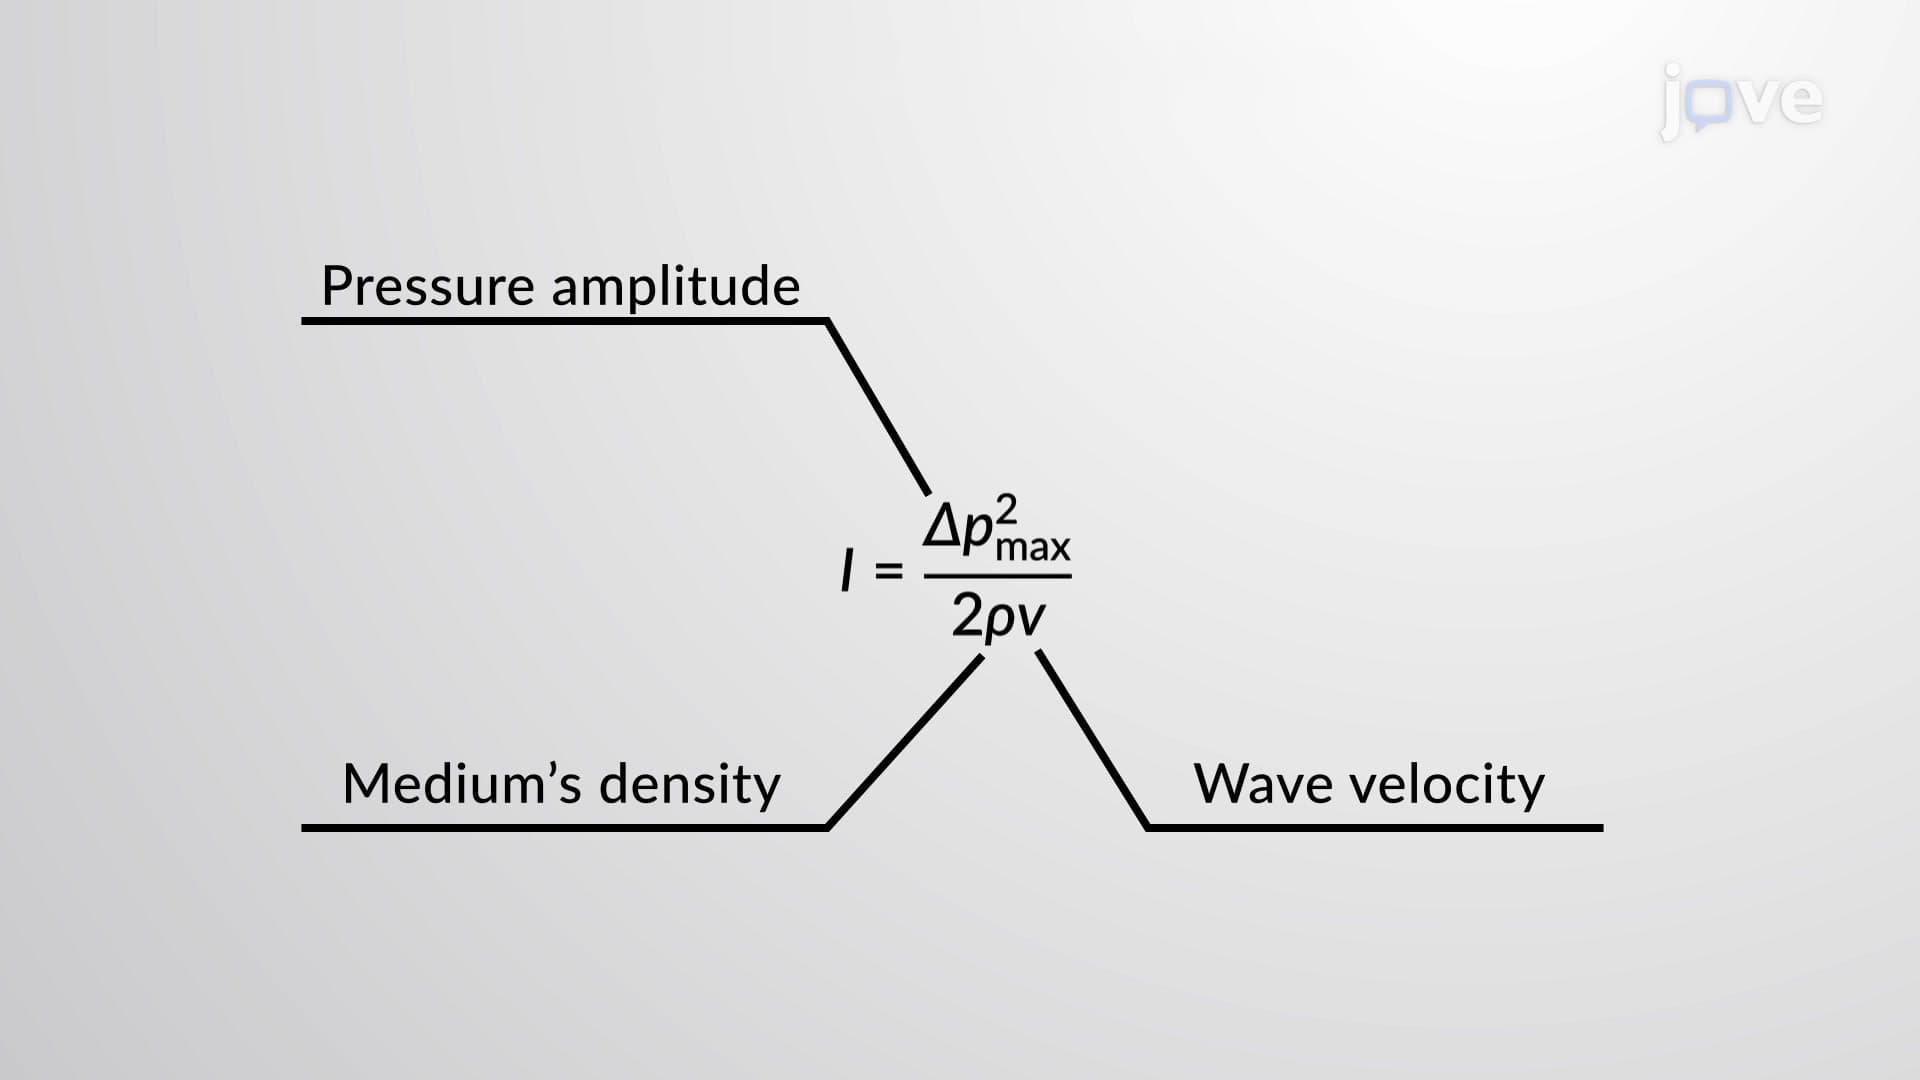
Intensity and Pressure of Sound Waves
Unlike the time average of a sinusoidal term, which is zero since it is positive...
 00:58
Sound Intensity
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities: