Related Experiment Video
Updated: Jul 20, 2025

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Abdominal Inflammatory Myofibroblastic Tumour Presenting as a Pancreatic Mass: A Case Report
Afafe Taiymi1, Nasiri Meryem2, Mohammed Bouziane3
1Gastroenterology and Hepatology, Digestive Disease Research Laboratory, Mohammed First University, Oujda, MAR.

Abstract:
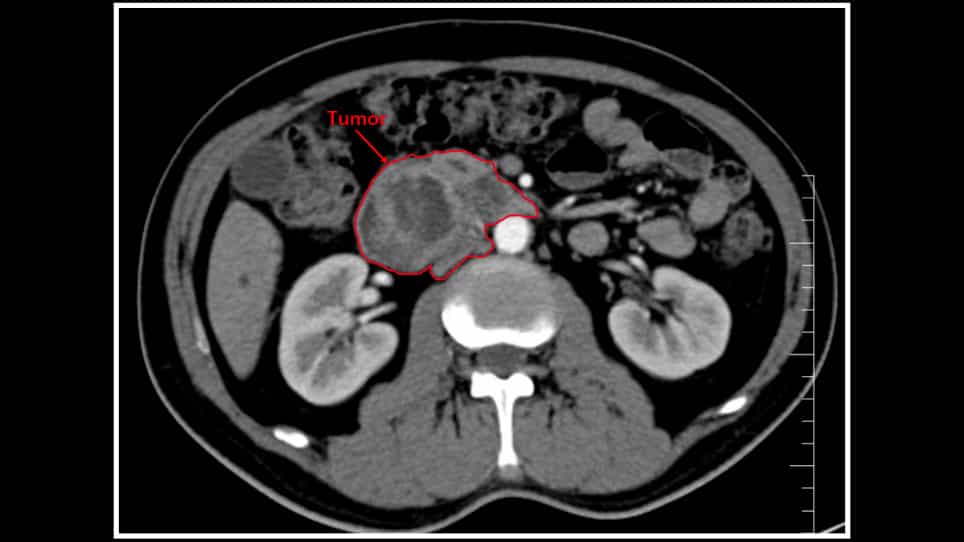
An abdominal inflammatory myofibroblastic tumor (AIMT), is a rare benign tumor composed of inflammatory and other mesenchymal cells. It can affect the entire body, predominantly in children and young adults. The diagnosis is challenging considering the wide clinical presentation and can often be mistaken for malignant tumors. We report a rare case of a 46-year-old female patient, who presented with intermittent abdominal pain weight loss, and an abdominal palpable mass. Abdominal ultrasound found a well-defined 18 cm, rounded mass, with solid and cystic components. Abdominal CT demonstrated a well-defined, hypodense, retro gastric mass of 20 cm, with thickened wall and heterogenous enhancement. The mass had contact with the pancreatic tail, transverse colon, spleen, left kidney pedicles, abdominal aorta, superior mesenteric vein, and mesaraic trunk with no invasion signs. The mass was initially thought to be pancreatic cancer, but given the large size, other diagnoses like sarcoma, lymphoma, or abdominal hydatid cyst were suggested. Endoscopic ultrasound found a rounded retro gastric mass of 18/12 cm, with a thickened wall and well-limited calcifications. The content was both cystic and solid with mobile vegetations, with no visible Doppler flow. The mass had contact with the body and tail of the pancreas, spleen hilum, the upper pole of the spleen, and the hepatic pedicle behind, with no invasion sign. After a multidisciplinary team meeting, a decision was taken to perform surgical resection with mass resection, distal splenopancreatectomy, and transverse and sigmoid colectomy. Pathological and immunostaining results were consistent with inflammatory pseudotumor. The postoperative recovery was uncomplicated. The patient remains asymptomatic with no obvious signs of metastasis or recurrence. AIMT represents a reel diagnostic challenge. Clinical symptoms are unspecific. Radiological and endoscopic features can often be mistaken for malignant tumors. Surgical management remains to be the best therapeutic option. We report a rare case of AIMT treated by surgery with complete resection. We suggested a long-term follow-up given the local recurrence risk.
Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...