Related Experiment Video
Updated: Jul 20, 2025


Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
Recurrent pleural effusion as a rare manifestation after prolonged PD1 inhibitor (camrelizumab)-based immunotherapy:
Xiao-Hong Xie1, Pan-Xiao Shen1, Jian-Hui Wu1
1The State Key Laboratory of Respiratory Disease, National Clinical Research Center for Respiratory Disease, Guangzhou Institute of Respiratory Health, The First Affiliated Hospital of Guangzhou Medical University, Guangzhou, Guangdong, China.

Immune-related adverse events (irAEs) pose a significant challenge for the widespread adoption of immuno-oncology therapies, but their symptoms can vary widely. In particular, the relationship between irAEs and pleural effusion (PE) in patients with advanced non-small cell lung cancer (NSCLC) remains unclear. In this report, we present the case of an advanced NSCLC patient who developed persistent PE despite receiving camrelizumab (an anti-programmed death receptor 1 [PD-1] antibody) and chemotherapy as first-line treatment. While the patient's tumor biomarkers decreased after multiple cycles of treatment, the PE persisted despite negative findings on cytology and pleural biopsy. Additionally, the use of anti-angiogenic drugs failed to alleviate the PE. Screening for rheumatic connective tissue markers and tuberculosis yielded negative results, but intrathoracic dexamethasone injections in two doses resulted in a significant reduction of the PE. This case suggests that PE may represent a rare type of irAE that should be monitored for during prolonged immuno-oncology therapy.
Immune-related adverse events (irAEs) pose a significant challenge for the widespread adoption of immuno-oncology therapies, but their symptoms can vary widely. In particular, the relationship between irAEs and pleural effusion (PE) in patients with advanced non-small cell lung cancer (NSCLC) remains unclear. In this report, we present the case of an advanced NSCLC patient who developed persistent PE despite receiving camrelizumab (an anti-programmed death receptor 1 [PD-1] antibody) and chemotherapy as first-line treatment. While the patient's tumor biomarkers decreased after multiple cycles of treatment, the PE persisted despite negative findings on cytology and pleural biopsy. Additionally, the use of anti-angiogenic drugs failed to alleviate the PE. Screening for rheumatic connective tissue markers and tuberculosis yielded negative results, but intrathoracic dexamethasone injections in two doses resulted in a significant reduction of the PE. This case suggests that PE may represent a rare type of irAE that should be monitored for during prolonged immuno-oncology therapy.


Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
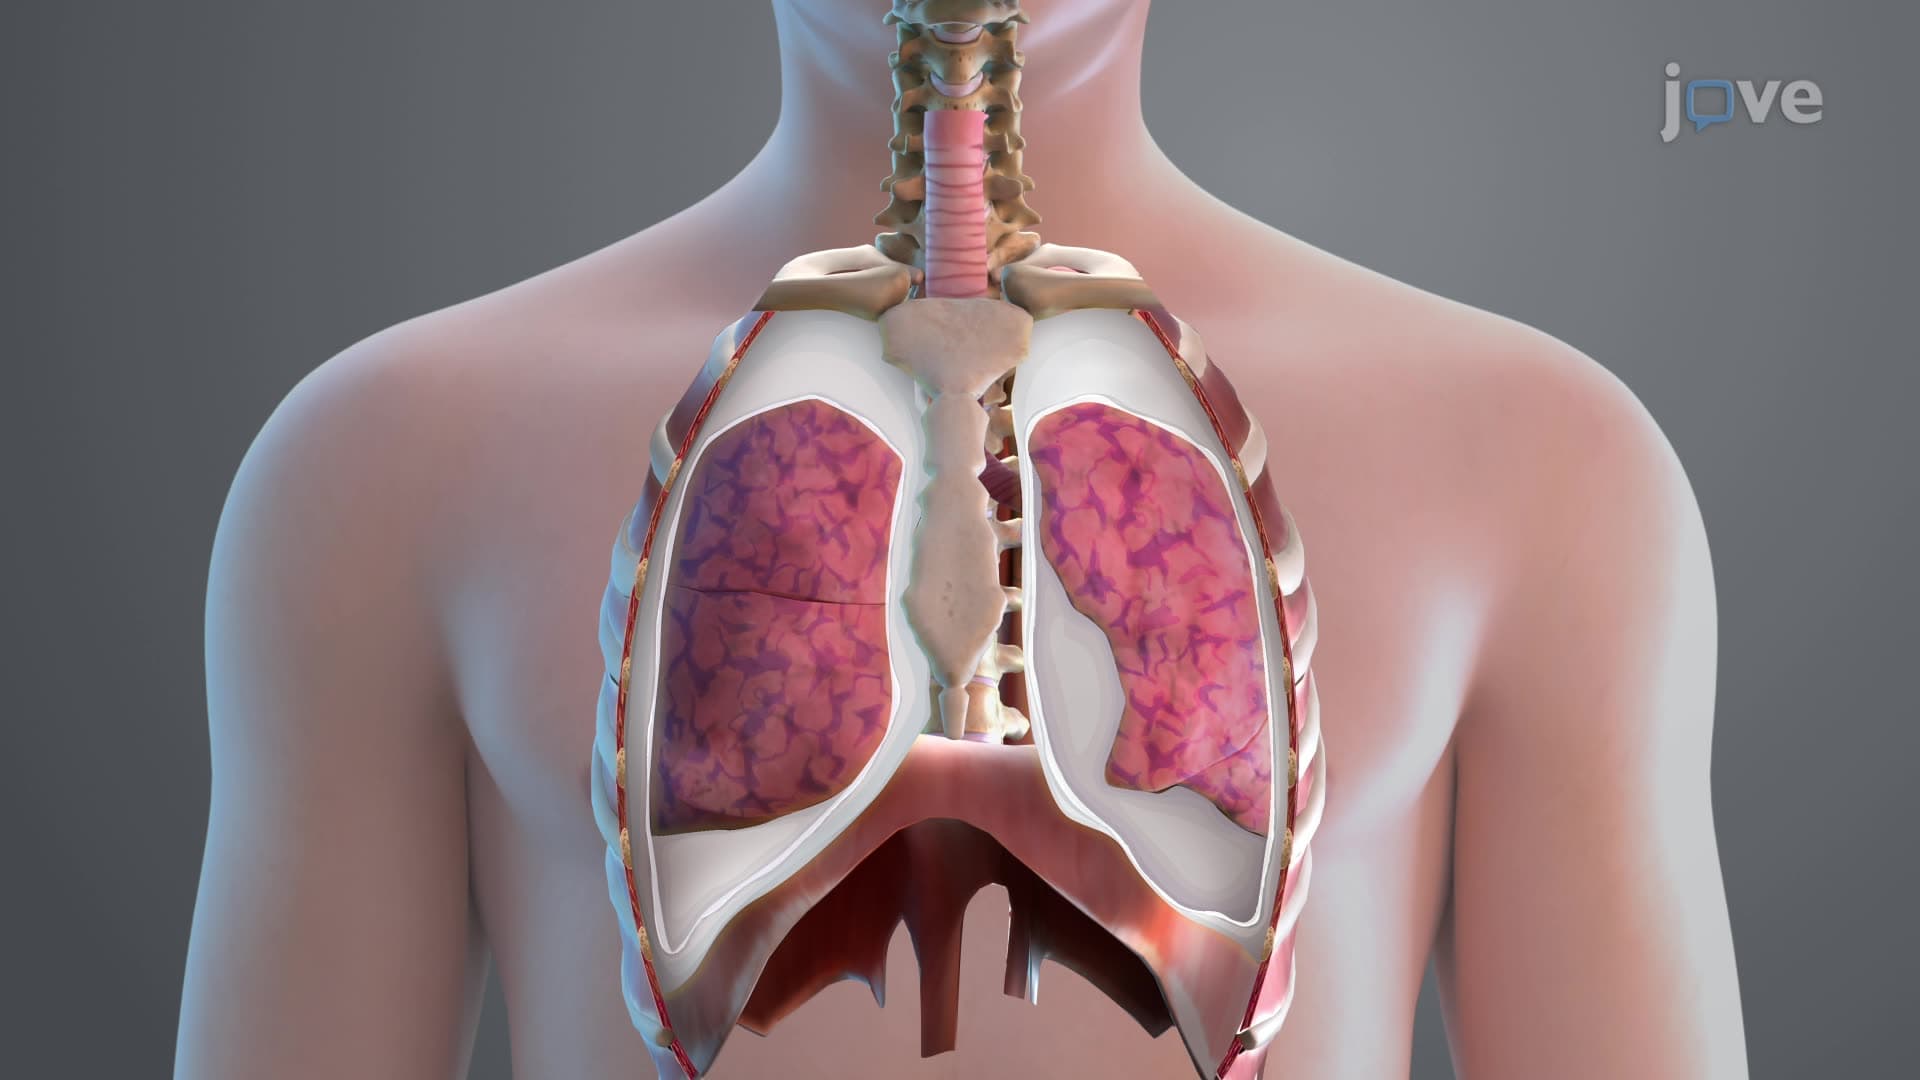
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Pleural Disorders: Types and Brief Description
 01:13
Pleura of the Lungs
 01:29
Pneumonia II: Pathophysiology