Related Experiment Video
Updated: Jul 20, 2025
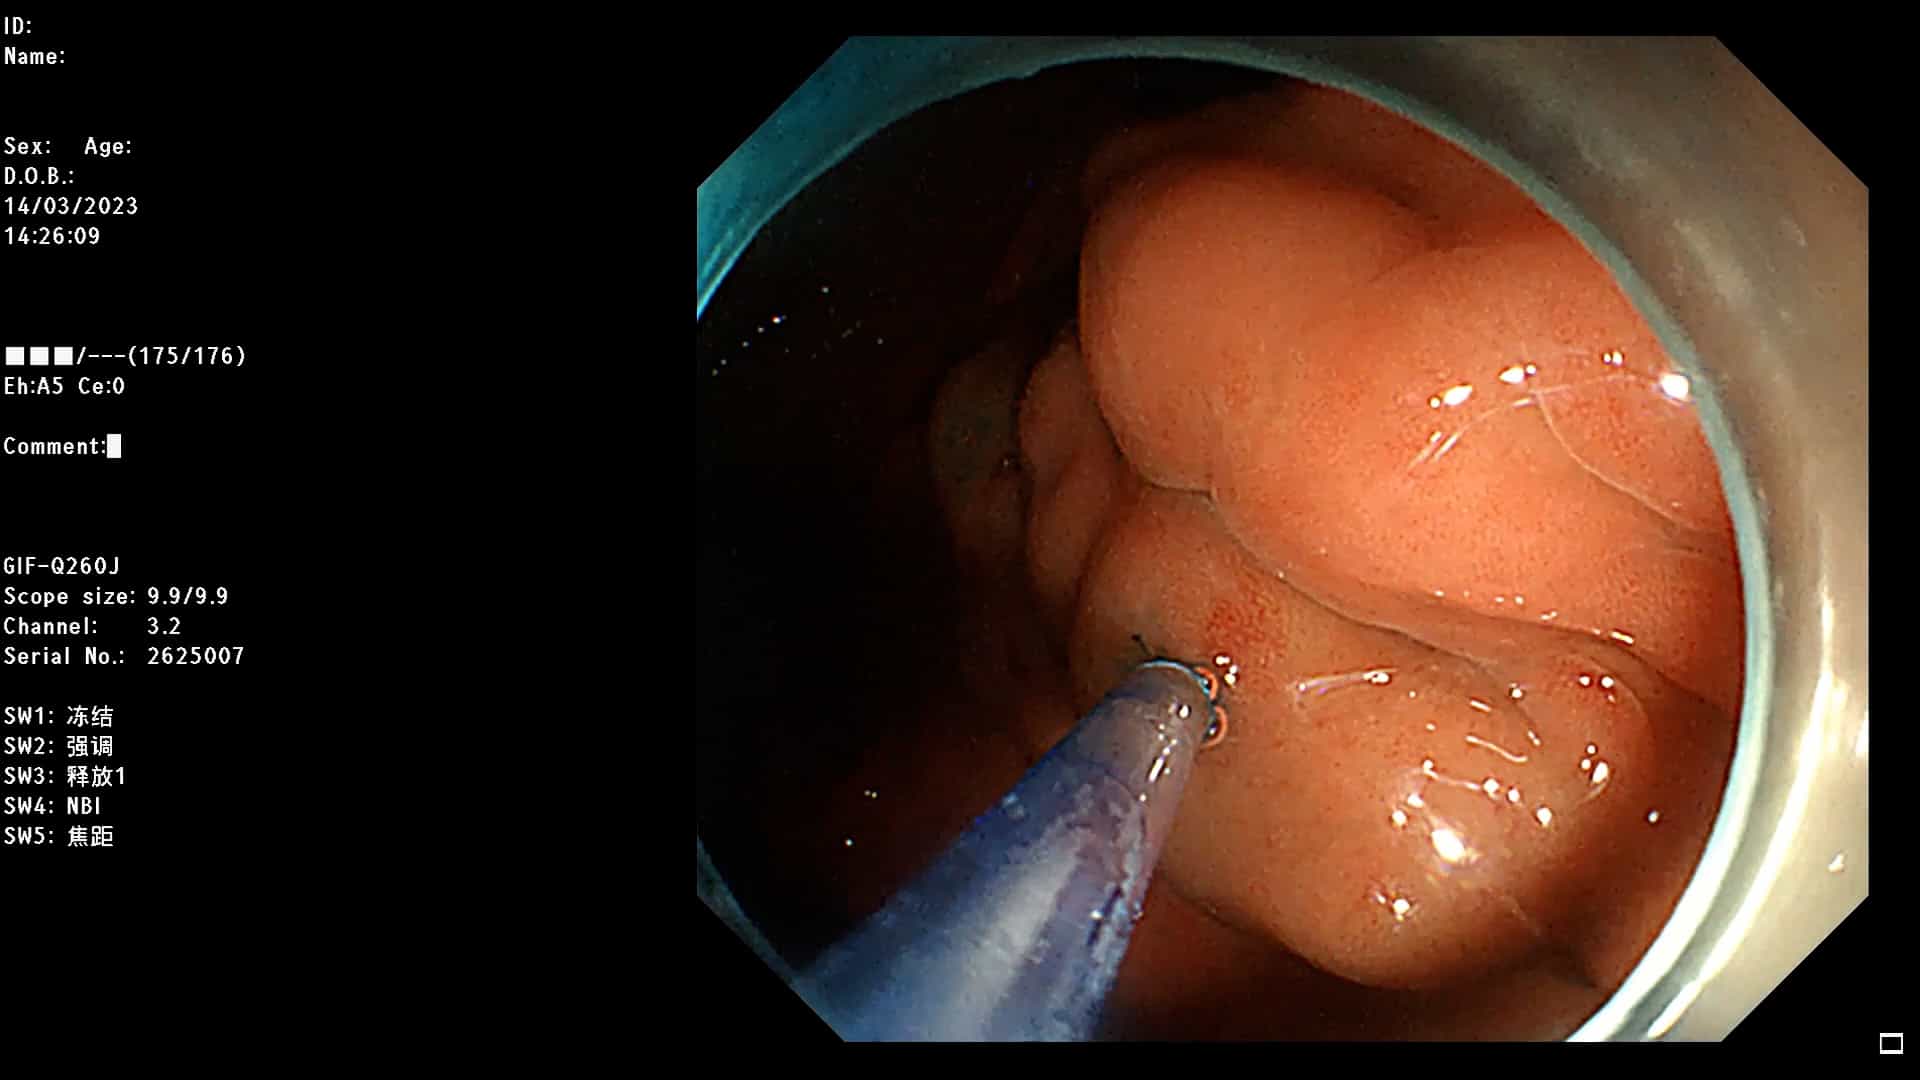
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
EUS-guided coil injection therapy in the management of gastric varices: the first U.S. multicenter experience (with
Ahmad Najdat Bazarbashi1, Elizabeth S Aby2, J Shawn Mallery2
1Division of Gastroenterology and Hepatology, Washington University in St. Louis School of Medicine/Barnes Jewish Hospital, St. Louis, Missouri, USA.

Background And Aims:
Despite the significant morbidity associated with gastric variceal bleeding, there is a paucity of high-quality data regarding optimal management. EUS-guided coil injection therapy (EUS-COIL) has recently emerged as a promising endoscopic modality for the treatment of gastric varices (GV), particularly compared with traditional direct endoscopic glue injection. Although there are data on the feasibility and safety of EUS-COIL in the management of GV, these have been limited to select centers with particular expertise. The aim of this study was to report the first U.S. multicenter experience of EUS-COIL for the management of GV.
Methods:
This retrospective analysis included patients with bleeding GV or GV at risk of bleeding who underwent EUS-COIL at 10 U.S. tertiary care centers between 2018 and 2022. Baseline patient and procedure-related information was obtained. EUS-COIL entailed the injection of .018 inch or .035 inch hemostatic coils using a 22-gauge or 19-gauge FNA needle. Primary outcomes were technical success (defined as successful deployment of coil into varix under EUS guidance with diminution of Doppler flow), clinical success (defined as cessation of bleeding if present and/or absence of bleeding at 30 days' postintervention), and intraprocedural and postprocedural adverse events.
Results:
A total of 106 patients were included (mean age 60.4 ± 12.8 years; 41.5% female). The most common etiology of GV was cirrhosis (71.7%), with alcohol being the most common cause (43.4%). Overall, 71.7% presented with acute GV bleeding requiring intensive care unit stay and/or blood transfusion. The most common GV encountered were isolated GV type 1 (60.4%). A mean of 3.8 ± 3 coils were injected with a total mean length of 44.7 ± 46.1 cm. Adjunctive glue or absorbable gelatin sponge was injected in 82% of patients. Technical success and clinical success were 100% and 88.7%, respectively. Intraprocedural adverse events (pulmonary embolism and GV bleeding from FNA needle access) occurred in 2 patients (1.8%), and postprocedural adverse events occurred in 5 (4.7%), of which 3 were mild. Recurrent bleeding was observed in 15 patients (14.1%) at a mean of 32 days. Eighty percent of patients with recurrent bleeding were successfully re-treated with repeat EUS-COIL. No significant differences were observed in outcomes between high-volume (>15 cases) and low-volume (<7 cases) centers.
Conclusions:
This U.S. multicenter experience on EUS-COIL for GV confirms high technical and clinical success with low adverse events. No significant differences were seen between high- and low-volume centers. Repeat EUS-COIL seems to be an effective rescue option for patients with recurrent bleeding GV. Further prospective studies should compare this modality versus other interventions commonly used for GV.
More Related Videos
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
 02:58
Combination of High Ligation and Intraoperative Embolization using Polidocanol for Treatment of Varicoceles
Published on: December 22, 2023
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...