Related Experiment Video
Updated: Jul 20, 2025
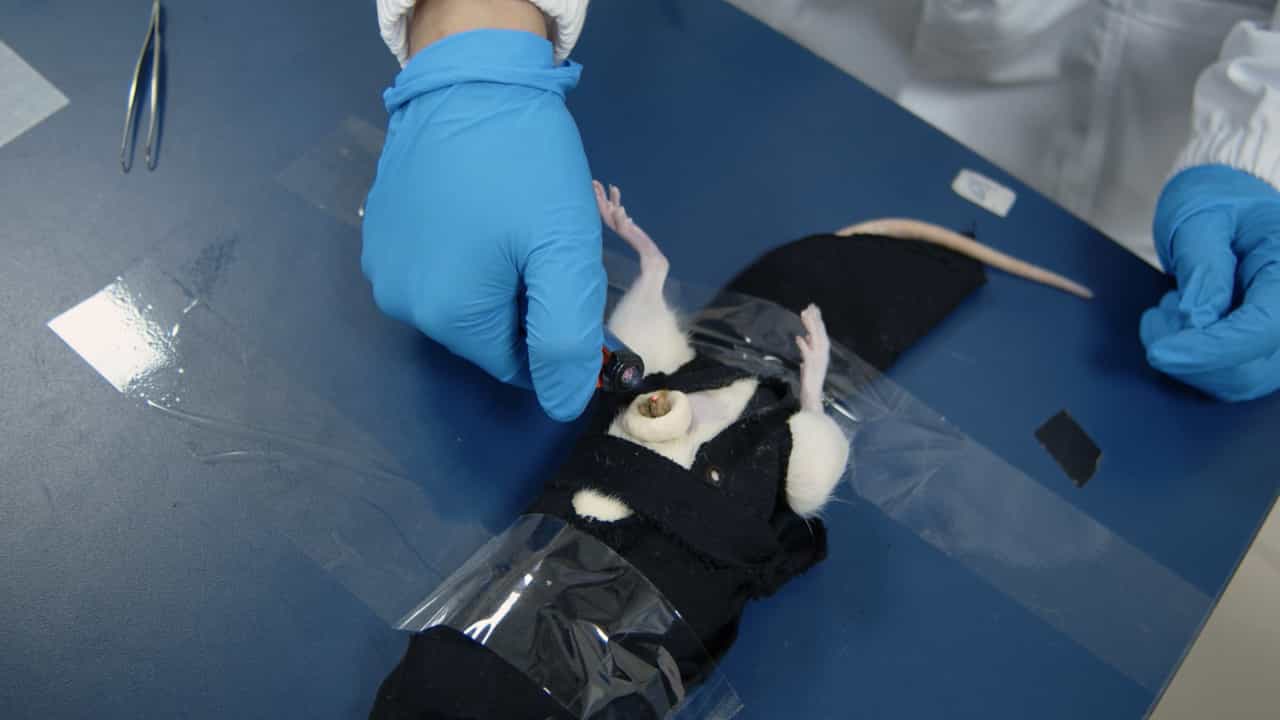

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Vitamin D and vitamin D receptor polymorphism in Asian adolescents with primary dysmenorrhea
Ainur Donayeva1, Ainur Amanzholkyzy1, Roza Nurgaliyeva1
1Department of Normal Physiology, West Kazakhstan Marat Ospanov Medical University, Aktobe, Kazakhstan.

Background:
The expression of vitamin D receptor in the normal endometrium and ovaries supports the role of vitamin D in local immunity and inflammatory cytokines regulation.
Objective:
This study aimed to detect the relation between serum 25(OH)D and primary dysmenorrhea in Asian Adolescents.
Methods:
Two hundred and five (205) adolescents complaining of primary dysmenorrhea (study group) were compared in this prospective study to matched controls (210 controls) after informed consent following the Helsinki Declaration. After thorough evaluation, including a thorough history and pelvic ultrasound examination, blood samples were collected from the studied adolescents to measure serum 25(OH)D and for vitamin D receptor TaqI (rs731236) genotyping. The studied adolescents' data were analyzed using the Pearson's correlation to detect the relation between serum 25(OH)D and primary dysmenorrhea (primary outcome). The secondary outcome measures the odds of primary dysmenorrhea in Asian adolescents with vitamin D receptor TaqI (rs731236) polymorphism.
Results:
The serum 25(OH)D was significantly lower in the studied-dysmenorrhea group compared to controls (16.17 ± 7.36 versus 17.65 ± 6.36 ng/ml, respectively), (P = 0.01). The correlation analysis showed a significant negative correlation between the serum 25(OH)D and visual analogue scale of dysmenorrhea (r = -0.9003, P < 0.0001). The studied-dysmenorrhea cases with vitamin D receptor T/t and t/t genotypes had significantly lower serum 25(OH)D (16.7 ± 8.05 and 14.4 ± 4.1 ng/ml, respectively) compared to controls (18.97 ± 6.7 and 21.4 ± 2.45 ng/ml, respectively), (P = 0.02 and 0.004, respectively). The VDR T/t and t/t polymorphisms significantly increase the odds of primary dysmenorrhea (OR 1367.2, P < 0.0001 and OR 106.2, P = 0.001, respectively).
Conclusion:
The serum 25(OH)D was significantly lower in the studied-dysmenorrhea group compared to controls. The studied-dysmenorrhea cases with VDR T/t and t/t TaqI genotypes had significantly lower serum 25(OH)D compared to controls. The VDR T/t and t/t polymorphisms significantly increase the odds of primary dysmenorrhea.
More Related Videos
 07:36
Analysis of Raw and Processed Cyperi Rhizoma Samples Using Liquid Chromatography-Tandem Mass Spectrometry in Rats with Primary Dysmenorrhea
Published on: December 23, 2022
 10:46
A Method of Trigonometric Modelling of Seasonal Variation Demonstrated with Multiple Sclerosis Relapse Data
Published on: December 9, 2015
Related Concept Videos
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin...
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...