Related Experiment Video
Updated: Jul 19, 2025


Use of Two Intracorporeal Ventricular Assist Devices As a Total Artificial Heart
Published on: May 11, 2018
Effect of Hematocrit and Elevated Beat Rate on the 12cc Penn State Pediatric Ventricular Assist Device
Sailahari V Ponnaluri1, Brady L Houtz1, Emma C Raich1
1From the Department of Biomedical Engineering, The Pennsylvania State University, University Park, Pennsylvania.

Insights
Pediatric ventricular assist devices (PVADs) show consistent flow fields across varying hematocrit and heart rates. Adjusting operating conditions can optimize PVAD performance and reduce clot risk in children.
Area of Science:
- Biomedical Engineering
- Pediatric Cardiology
- Fluid Dynamics
Background:
- Congenital heart disease (CHD) impacts ~40,000 US infants annually, with 25% needing intervention.
- Pediatric ventricular assist devices (PVADs) serve as a critical bridge to transplant for children due to donor heart scarcity.
- Existing PVADs are optimized for nominal conditions, but pediatric patients exhibit unique physiological variations like fluctuating hematocrit and heart rates.
Purpose of the Study:
- To evaluate the performance of the 12cc pneumatic Penn State PVAD under pediatric-specific physiological conditions.
- To investigate the impact of varying hematocrit and heart rates on flow dynamics and surface washing within the PVAD.
- To determine if operational adjustments can mitigate risks of platelet adhesion and thrombus formation in pediatric patients.
Main Methods:
- Utilized particle image velocimetry (PIV) to analyze fluid flow within the PVAD.
- Employed three non-Newtonian blood analogs with hematocrit levels of 20%, 40%, and 60%.
- Tested the device at two distinct beat rates: 75 bpm and 120 bpm, simulating pediatric heart rate variability.
Main Results:
- Consistent flow field patterns, including an inlet jet and solid body rotation during diastole, were observed across all tested hematocrit levels and beat rates.
- Higher velocity magnitudes were noted at 120 bpm compared to 75 bpm.
- Minor variations in flow field timing and surface washing efficiency were associated with different hematocrit levels.
Conclusions:
- The Penn State PVAD demonstrates robust flow characteristics irrespective of pediatric hematocrit or heart rate variability.
- Effective surface washing, crucial for reducing platelet adhesion, can be achieved by optimizing PVAD operating conditions.
- These findings support the potential for tailored PVAD operation to enhance safety and efficacy in pediatric CHD patients.
Abstract:
Congenital heart disease affects approximately 40,000 infants annually in the United States with 25% requiring invasive treatment. Due to limited number of donor hearts and treatment options available for children, pediatric ventricular assist devices (PVADs) are used as a bridge to transplant. The 12cc pneumatic Penn State PVAD is optimized to prevent platelet adhesion and thrombus formation at patient nominal conditions; however, children demonstrate variable blood hematocrit and elevated heart rates. Therefore, with pediatric patients exhibiting greater variability, particle image velocimetry is used to evaluate the PVAD with three non-Newtonian hematocrit blood analogs (20%, 40%, and 60%) and at two beat rates (75 and 120 bpm) to understand the device's performance. The flow fields demonstrate a strong inlet jet that transitions to a solid body rotation during diastole. During systole, the rotation dissipates and reorganizes into an outlet jet. This flow field is consistent across all hematocrits and beat rates but at a higher velocity magnitude during 120 bpm. There are also minor differences in flow field timing and surface washing due to hematocrit. Therefore, despite patient differences in hematocrit or required pumping output, thorough surface washing can be achieved in the PVAD by altering operating conditions, thus reducing platelet adhesion potential.
More Related Videos


Related Concept Videos
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
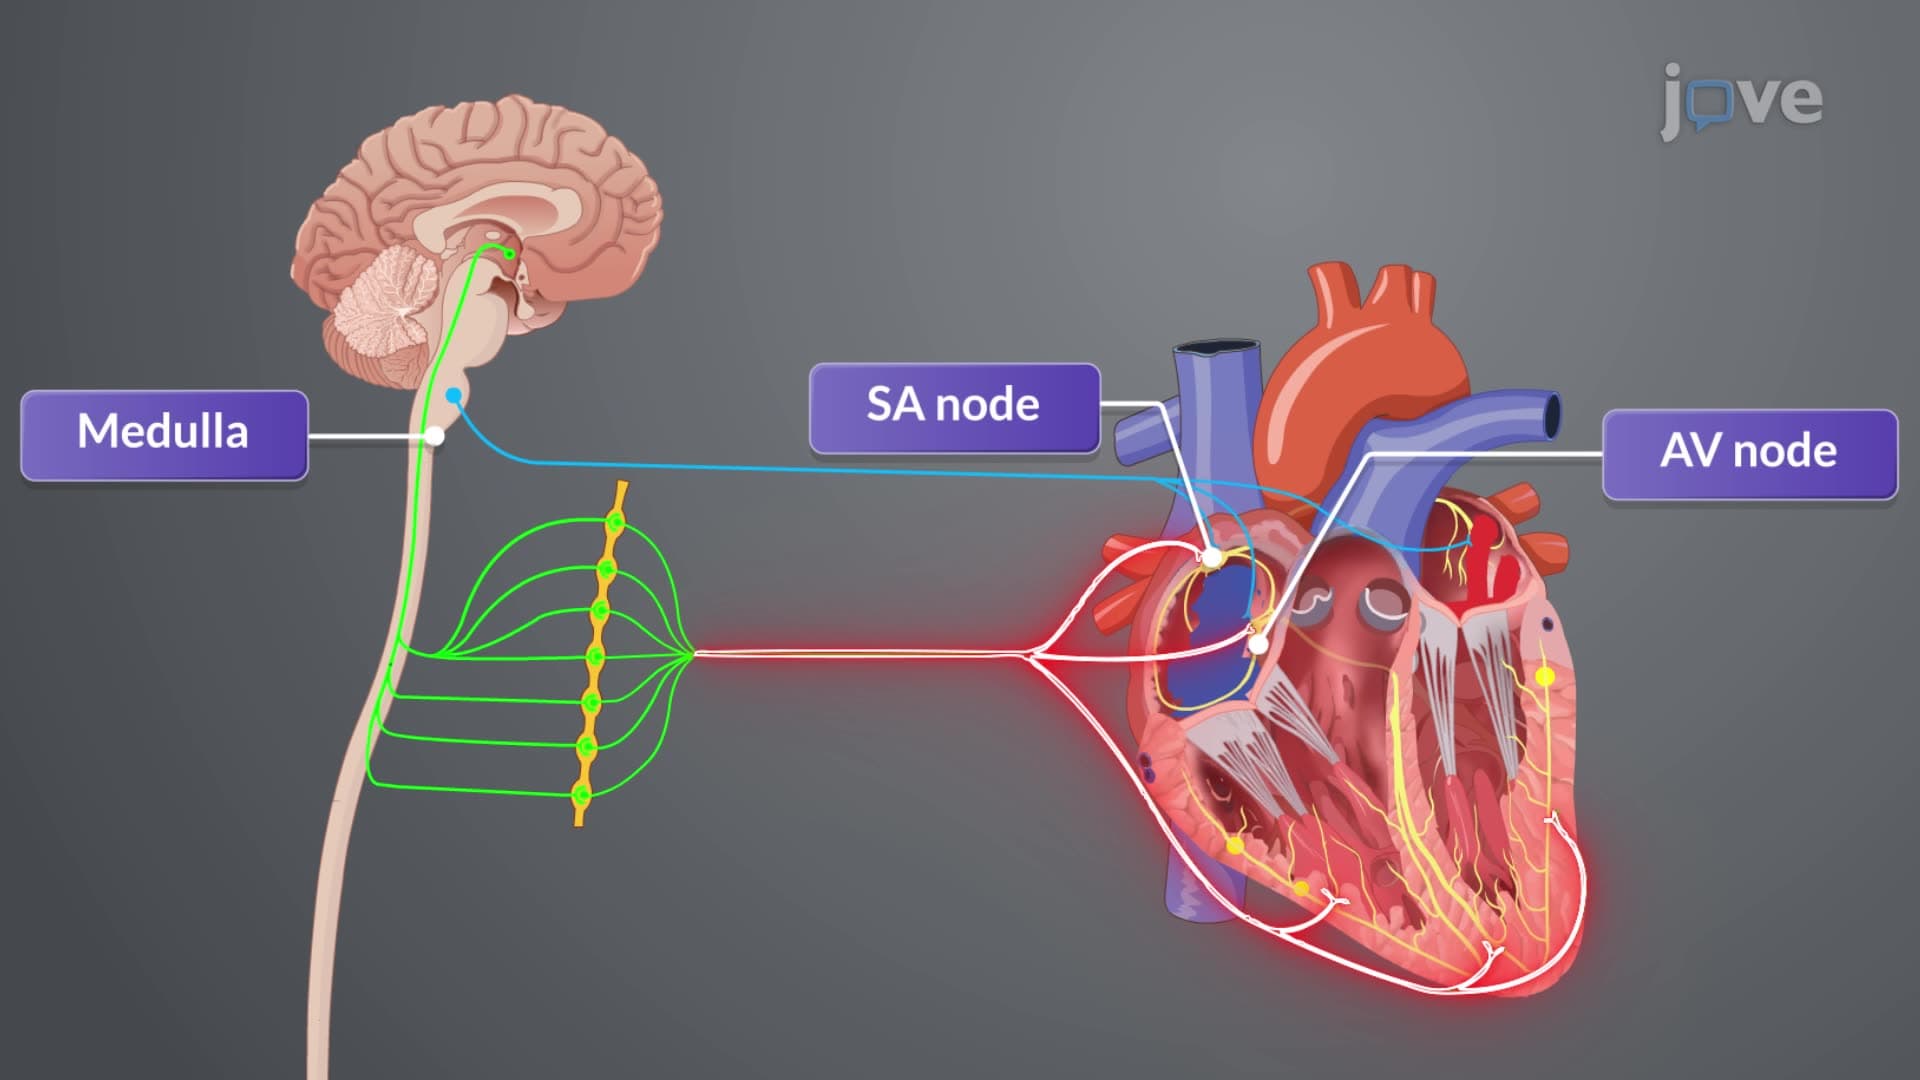
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...