Related Experiment Video
Updated: Jul 19, 2025
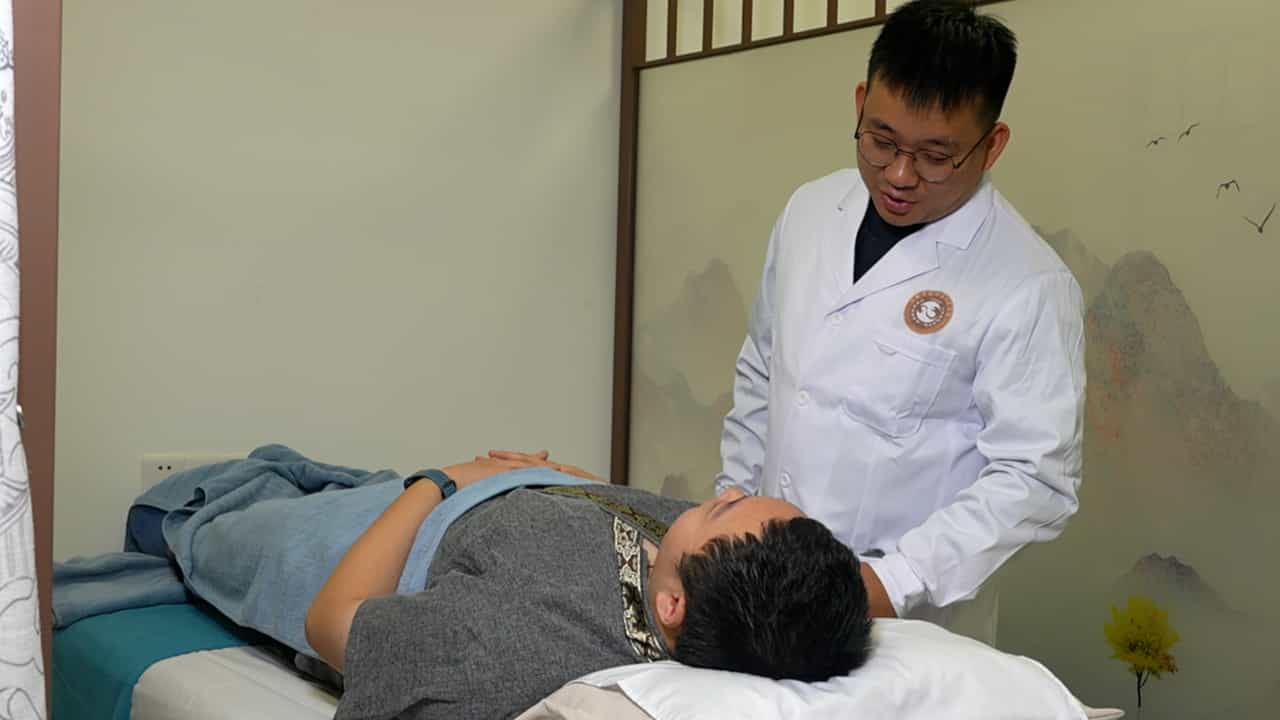

Author Spotlight: Evaluating the Therapeutic Efficacy of Moving Cupping Along Meridians for Acute Exacerbation of COPD
Published on: September 27, 2024
Complexity in clinical diagnoses of acute exacerbation of chronic obstructive pulmonary disease
Alexandre J Pratt1, Andrew Purssell2, Tinghua Zhang3
1Department of Medicine, University of Ottawa, Ottawa, ON, Canada.

Background:
Acute exacerbation of chronic obstructive pulmonary disease (AECOPD) is a clinical syndrome with various causes. It is not uncommon that COPD patients presenting with dyspnea have multiple causes for their symptoms including AECOPD, pneumonia, or congestive heart failure occurring concurrently.
Methods:
To identify clinical, radiographic, and laboratory characteristics that might help distinguish AECOPD from another dominant disease in patients with a history of COPD, we conducted a retrospective cohort study of hospitalized patients with admitting diagnosis of AECOPD who were screened for a prospective randomized controlled trial from Sep 2016 to Mar 2018. Clinical characteristics, course in hospital, and final diagnosis at discharge were reviewed and adjudicated by two authors. The final diagnosis of each patient was determined based on the synthesis of all presenting signs and symptoms, imaging, and laboratory results. We adhered to AECOPD diagnosis definitions based on the GOLD guidelines. Univariate and multivariate analyses were performed to identify any associated features of AECOPD with and without other acute processes contributing to dyspnea.
Results:
Three hundred fifteen hospitalized patients with admitting diagnosis of AECOPD were included. Mean age was 72.5 (SD 10.6) years. Two thirds (65.4%) had spirometry defined COPD. The most common presenting symptom was dyspnea (96.5%), followed by cough (67.9%), and increased sputum (57.5%). One hundred and eighty (57.1%) had a final diagnosis of AECOPD alone whereas 87 (27.6%) had AECOPD with other conditions and 48 (15.2%) did not have AECOPD after adjudication. Increased sputum purulence (OR 3.35, 95%CI 1.68-6.69) and elevated venous pCO2 (OR 1.04, 95%CI 1.01 - 1.07) were associated with a diagnosis of AECOPD but these were not associated with AECOPD alone without concomitant conditions. Radiographic evidence of pleural effusion (OR 0.26, 95%CI 0.12 - 0.58) was negatively associated with AECOPD with or without other conditions while radiographic evidence of pulmonary edema (OR 0.31; 95%CI 0.11 - 0.91) and lobar pneumonia (OR 0.13, 95%CI 0.07 - 0.25) suggested against the diagnosis of AECOPD alone.
Conclusion:
The study highlighted the complexity and difficulty of AECOPD diagnosis. A more specific clinical tool to diagnose AECOPD is needed.
More Related Videos

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: