Related Experiment Video
Updated: Jul 18, 2025

Author Spotlight: Unraveling the Molecular Mechanisms in PCO and Fibrosis Following Cataract Surgery
Published on: December 1, 2023
Cataract surgery following penetrating keratoplasty in children
Rajendran Janani1, Pandurangan Sneha1
1Department of Paediatric Ophthalmology and Strabismus, Aravind Eye Hospital, Madurai, Tamil Nadu, India.

Insights
This study details modifications for cataract surgery after penetrating keratoplasty to maximize graft survival. Key techniques include avoiding the graft-host junction and protecting the corneal endothelium during surgery.
Area of Science:
- Ophthalmology
- Surgical Techniques
Background:
- Penetrating keratoplasty (PKP) is a corneal transplant procedure.
- Cataract surgery following PKP requires specific adaptations to preserve graft integrity.
Purpose of the Study:
- To highlight intraoperative challenges in combined PKP and cataract surgery.
- To outline essential surgical manipulations for successful outcomes.
Main Methods:
- Creating a superior sclerocorneal tunnel, avoiding the graft-host junction.
- Utilizing dispersive viscoelastic agents for endothelial protection (soft shell technique).
- Employing low phacoemulsification energy and specific probe orientation to protect the graft.
Main Results:
- Maintaining graft-host junction integrity throughout the procedure.
- Ensuring good intraoperative corneal visibility.
- Successful placement of intraocular lens within the capsular bag.
Conclusions:
- Modified cataract surgery techniques are crucial for graft survival post-PKP.
- Careful surgical planning and execution are essential to avoid complications.
- Adherence to specific steps ensures optimal outcomes in these complex cases.
Background:
Following penetrating keratoplasty, cataract surgery warrants certain modifications to ensure maximum survival of the graft.
Purpose:
To emphasize the intraoperative challenges and surgical manipulations to be followed.
Synopsis:
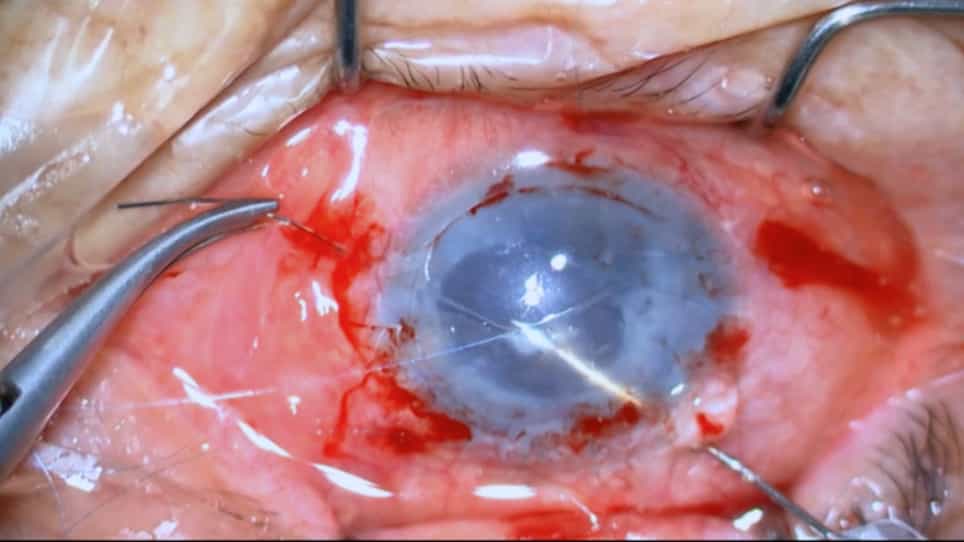
The surgeon makes a superior sclerocorneal tunnel avoiding the graft host junction. Dispersive viscoelastic is used. Continuous curvilinear capsulorhexis is done. Cataractous lens aspirated with a low flow rate. The intraocular lens is placed in the bag. Superior peripheral iridectomy and primary posterior capsulorhexis are done. The wound closed with two interrupted 10-0 nylon sutures. Graft host junction integrity is maintained.
Highlights:
Ensure 1. Good intraoperative corneal visibility, 2. Avoid graft host junction for main port incision 3. Generous dispersive viscoelastic use/soft shell technique to protect the corneal endothelium, 4. Avoid phaco energy in case of soft cataracts/low phaco energy and flow rates, 5. Phaco probe to be meticulously oriented away from corneal endothelium, 6. Primary posterior capsulorhexis to be done as in any pediatric cataract surgery, 7. Make sure of the graft host junction integrity at the end of the surgery, 8. Restrict to a single port whenever possible.
Video Link:
https://youtu.be/tu4R5JangYs.