Validation of a clinical model for predicting left versus right ventricular outflow tract origin of idiopathic ventricular arrhythmias
Related Experiment Video
Updated: Jul 18, 2025
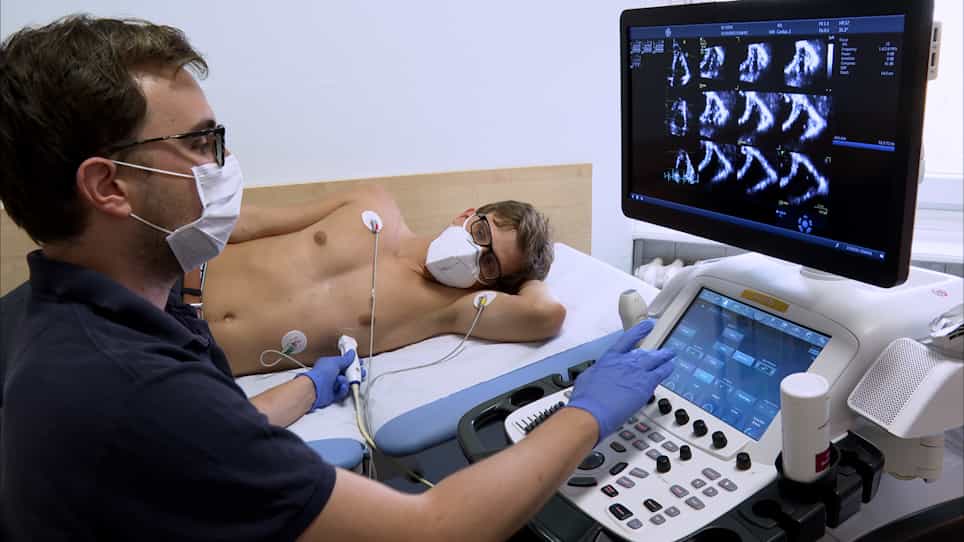
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Luc Bourquin1, Thomas Küffer2, Babken Asatryan2
1Department of Cardiology and Cardiovascular Research Institute Basel (CRIB), University Hospital Basel, Basel, Switzerland.

Insights
Predicting the origin of outflow tract ventricular arrhythmias (OTVA) is difficult. A clinical score combining age, sex, and hypertension showed moderate accuracy, but improved significantly when paired with an ECG algorithm for specific cases.
Area of Science:
- Cardiology
- Electrophysiology
- Medical Diagnostics
Background:
- Outflow tract ventricular arrhythmias (OTVA) present a diagnostic challenge.
- Identifying the chamber of origin is crucial for effective treatment.
- A prior clinical risk score (age, sex, hypertension) suggested LVOT origin.
Purpose of the Study:
- To validate a clinical risk score for predicting left ventricular outflow tract (LVOT) origin in OTVA patients.
- To assess the score's performance in a new cohort.
- To explore combined diagnostic approaches.
Main Methods:
- Two-center observational cohort study of 187 patients undergoing catheter ablation for idiopathic OTVA.
- Utilized an electroanatomical mapping system.
- Defined successful ablation by ≥80% PVC burden reduction at 3 months.
Main Results:
- A clinical score (age, sex, hypertension) showed 73% sensitivity and 67% specificity for LVOT origin.
- The score's performance was lower than initially reported.
- Combining the clinical score with an ECG algorithm (V2 S/V3 R-index) improved prediction to 81% sensitivity and 70% specificity for PVCs with R/S transition at V3.
Conclusions:
- The validated clinical score demonstrated moderate predictive value for LVOT origin in OTVA.
- The combination of the clinical score and a specific ECG algorithm significantly enhances predictability for certain arrhythmia types.
- Further refinement of diagnostic tools for OTVA is warranted.
Background:
Prediction of the chamber of origin in patients with outflow tract ventricular arrhythmias (OTVA) remains challenging. A clinical risk score based on age, sex and presence of hypertension was associated with a left ventricular outflow tract (LVOT) origin. We aimed to validate this clinical score to predict an LVOT origin in patients with OTVA.
Methods:
In a two-center observational cohort study, unselected patients undergoing catheter ablation (CA) for OTVA were enrolled. All procedures were performed using an electroanatomical mapping system. Successful ablation was defined as a ≥80% reduction of the initial overall PVC burden after 3 months of follow-up. Patients with unsuccessful ablation were excluded from this analysis.
Results:
We included 187 consecutive patients with successful CA of idiopathic OTVA. Mean age was 52 ± 15 years, 102 patients (55%) were female, and 74 (40%) suffered from hypertension. A LVOT origin was found in 64 patients (34%). A score incorporating age, sex and presence of hypertension reached 73% sensitivity and 67% specificity for a low (0-1) and high (2-3) score, to predict an LVOT origin. The combination of one ECG algorithm (V2 S/V3 R-index) with the clinical score resulted in a sensitivity and specificity of 81% and 70% for PVCs with R/S transition at V3 .
Conclusion:
The published clinical score yielded a lower sensitivity and specificity in our cohort. However, for PVCs with R/S transition at V3, the combination with an existing ECG algorithm can improve the predictability of LVOT origin.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Mechanism of Cardiac Arrhythmias
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests