Related Experiment Video
Updated: Jul 18, 2025
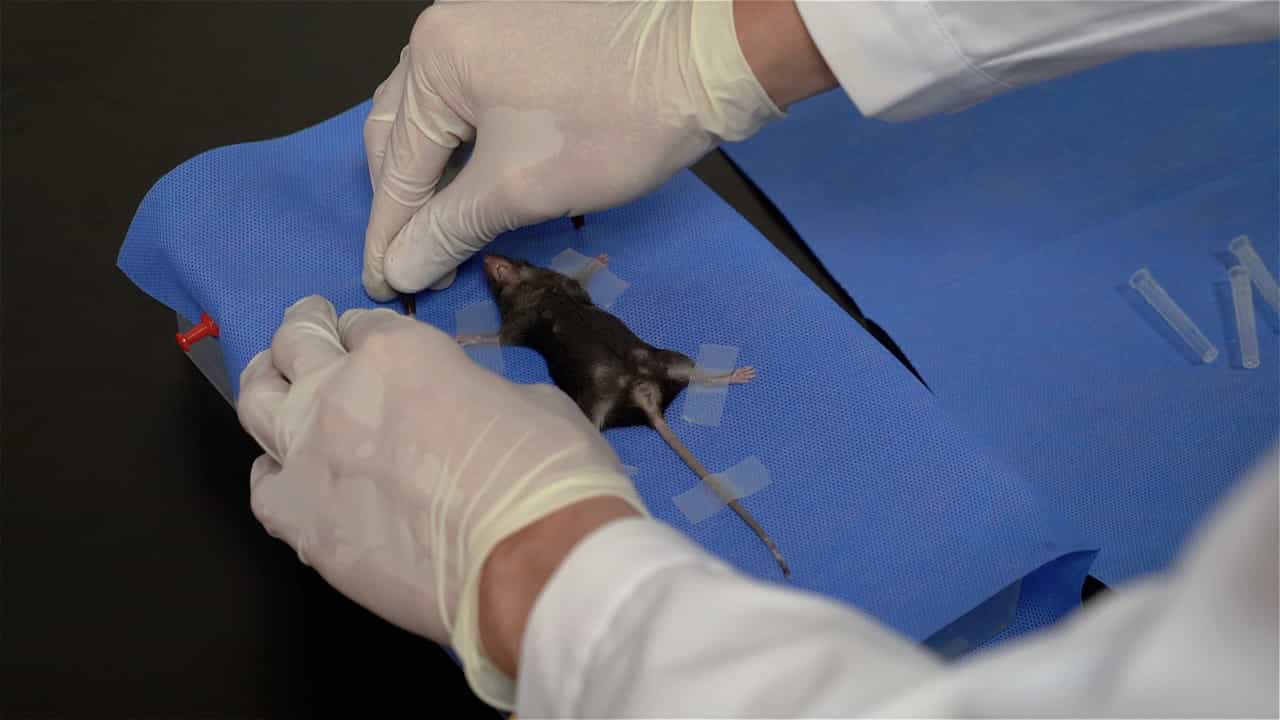
Author Spotlight: Insights into an Efficient Murine Maxillary Orthodontic Model Protocol
Published on: October 27, 2023
Multicentre Prospective Study Analysing Relevant Factors Related to Marginal Bone Loss: A Two-Year Evolution
Iñigo Fernández-Figares-Conde1, Lizett Castellanos-Cosano1, Juan-Alberto Fernandez-Ruiz2
1Department of Stomatology, School of Dentistry, University of Seville, C/Avicena s/n, 41009 Seville, Spain.

Introduction:
The aim of this prospective descriptive study was to analyse the possible variables associated with marginal bone loss in rehabilitated implants (Proclinic S.A.U, Zaragoza, Spain) two years after their prosthetic loading.
Materials And Methods:
Three clinical centres collaborated for a period of two years after the prosthetic rehabilitation of the implants (Proclinic S.A.U, Zaragoza, Spain), in which marginal bone loss and the possible associated variables were evaluated. The collection form comprised different variables throughout different stages of the implant procedure, from implant insertion to the subsequent prosthetic rehabilitation, over a two-year period. Data of the patients and implant characteristics were studied. Statistical analysis was performed with SPSS for qualitative (univariate logistic regressions, Chi2 test, and Haberman's corrected standardised residuals) and quantitative variables (Kolmogorov-Smirnov test).
Results:
The total study sample consisted of 218 implants (Proclinic S.A.U, Zaragoza, Spain). The sample presented a frequency of 99 men (45.4%) and 119 women (54.6%). The mean age of the patients among the reported cases was 58.56 ± 10.12 years. A statistically significant association was found between marginal bone loss 2 years after prosthetic rehabilitation placement and several variables, including age (under 55 years, 0.25 mm ± 0.56; 55-64 years, 0.74 mm ± 0.57; over 65 years, 0.63 mm ± 0.55; p < 0.0001), gender (female, 0.74 mm ± 0.61; male, 0.34 mm ± 0.51; p < 0.0001), bone quality (D1, 0.75 mm ± 0.62; D2, 0.43 mm ± 0.57; D3, 0.65 mm ± 0.60; p < 0.01), implant diameter (up to 4 mm, 0.49 mm ± 0.58; more than 4 mm, 1.21 mm ± 0.30; p < 0.0001), prosthetic connection type (direct to implant, 0.11 mm ± 0.58; transepithelial straight, 0.67 mm ± 0.57; transepithelial angled, 0.33 mm ± 0.25; p < 0001), implant model (internal conical, 0.17 mm ± 0.24; external conical, 0.48 mm ± 0.61; external cylindrical, 1.12 mm ± 0.32; p < 0.0001), prosthetic restoration type (full denture, 0.59 mm ± 0.59; partial denture, 0.50 mm ± 0.85; unitary crown, 0.08 mm ± 0.19; p < 0.05), and insertion torque (>35 N/cm, 0.53 mm ± 0.58; <35 N/cm, 1.04 mm ± 0.63; p < 0.01).
Conclusions:
At 2 years, marginal bone loss following prosthetic rehabilitation was shown to be influenced by multiple factors. Correct implantological planning is of vital importance for successful rehabilitation.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:31
Osteoclasts in Bone Remodeling
 01:20
Study Designs in Epidemiology
Observational studies are those where the researcher does not intervene but rather observes natural variations. They include cross-sectional, cohort, and...