Related Experiment Video
Updated: Jul 18, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Vertebral compression fractures managed with brace: risk factors for progression
R Gutierrez-Gonzalez1,2, C Ortega3, A Royuela4
1Department of Neurosurgery, IDIPHISA, Puerta de Hierro University Hospital, Manuel de Falla 1, 28222, Majadahonda, Madrid, Spain. rgutierrezgonzalez@yahoo.es.

Purpose:
The aim of this study is to identify risk factors for vertebral compression fracture (VCF) progression in patients treated conservatively with a brace. Then, a case-control study was designed.
Methods:
All patients over 50 years old with diagnosis of thoracic or lumbar VCF (T5 to L5) in absence of underlying oncological process, treated conservatively with brace, and consecutively attended at our department from January 2017 to June 2021 were retrospectively selected for analysis. Patients missed for follow-up or dead during the first 3 months of follow-up were excluded.
Results:
Five hundred and eighty-two consecutive patients were recorded. Incomplete follow-up excluded 74 patients and other 19 died in the first three months after diagnosis, so 489 cases were finally analyzed. Median follow-up was 21 (IQR 13;30) weeks. Increased collapse of the vertebral body was found in 29.9% of VCFs with a median time to progression of 9 (IQR 7;13) weeks. Male gender (OR 1.6), type A3 fracture of the AOSpine classification (OR 2.7), thoracolumbar junction location (OR 1.7), and incorrect use of the brace (OR 3.5) were identified as independent risk factors for progression after multivariable analysis.
Conclusion:
Male gender, type A3 fracture of the AOSpine classification, thoracolumbar junction location, and incorrect use of the brace were identified as independent risk factors for VCF progression, which resulted in worse pain control, when treated with brace. Thus, other treatments such as percutaneous vertebral augmentation could be considered to avoid progression in selected cases, since collapse rate has been demonstrated lower with these procedures.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
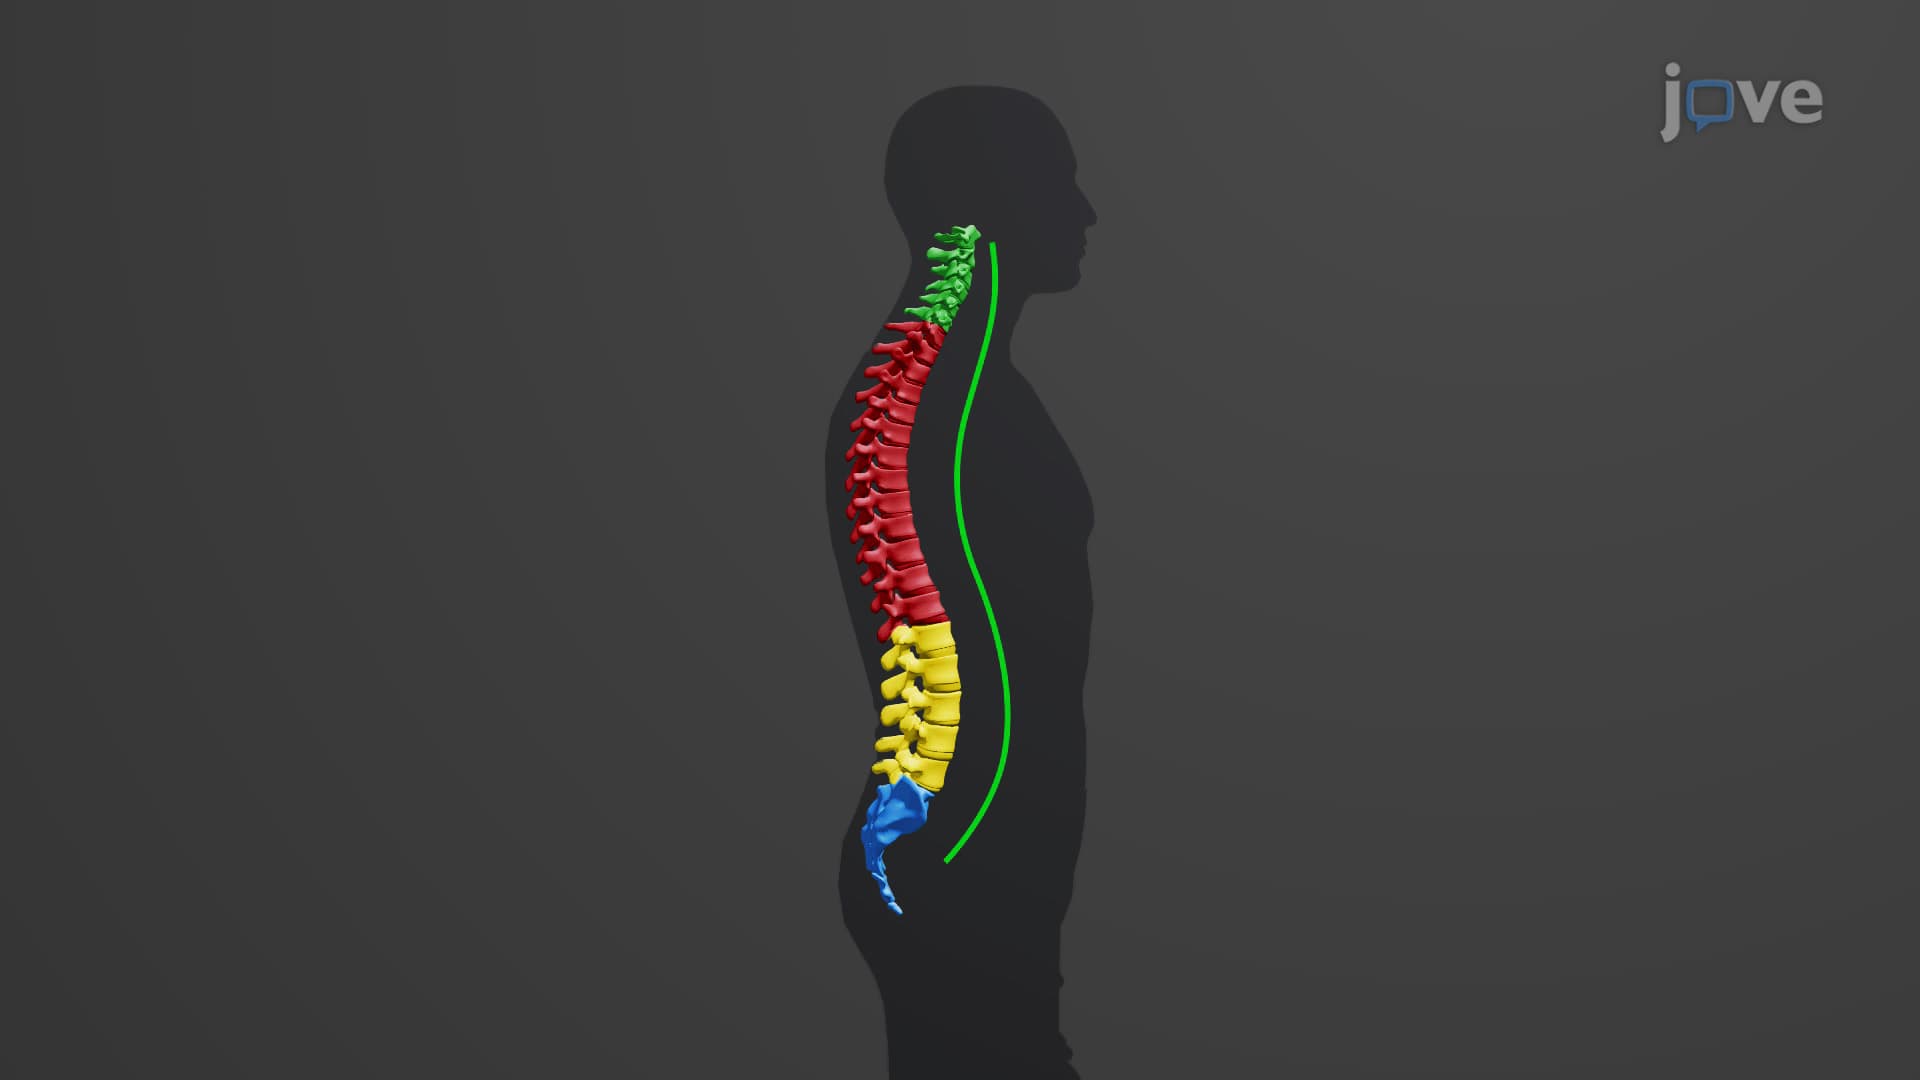
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:29
Venous Thrombosis III: Interprofessional Care