Related Experiment Video
Updated: Jul 18, 2025

Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
Effect of modified high-flow oxygen therapy on positive end-expiratory pressure and end-expiratory lung volume based
Kunming Cheng1, Wanqing Li2, Yanqiu Lu1
1Department of Intensive Care Unit, The Second Affiliated Hospital of Zhengzhou University, Zhengzhou, China.

Objective:
The aim of this study was to assess the effect of modified high-flow oxygen therapy on end-expiratory lung volume (EELV) and positive end-expiratory pressure (PEEP) in tracheotomized patients with normal pulmonary, acute hypoxic respiratory failure (AHRF) or chronic obstructive pulmonary disease (COPD).
Methods:
A ventilator and an artificial lung model were used to simulate the normal or strong inspiratory effort state of normal lung, AHRF and COPD patients. The traditional high-flow respiratory humidification therapy device connected with a standard interface (group A), and the modified therapy device added two types of resistance valves (group B, inner diameter 7.7 mm, length 24.0 mm; group C, inner diameter 7.7 mm, length 34.0 mm) to the exhalation end of the standard interface. The changes of end-expiratory lung volume (ΔEELV) and PEEP with the increase of flow rate (10 L/min, 20 L/min, 30 L/min, 40 L/min, 50 L/min, 60 L/min) in the three groups was recorded.
Results:
Under simulated conditions of normal lung, AHRF and COPD, as the flow rate increased by using the modified therapy device, the PEEP values in all groups showed an exponential increasing trend, and the ΔEELV also increased accordingly. In addition, under the same flow rate level, the PEEP values of the two modified high-flow oxygen therapies (Group B and Group C) were significantly higher than those of the standard high-flow oxygen therapy (Group A) (p < 0.05). In the normal lung model with normal or strong inspiratory effort, and in the AHRF or COPD model with strong inspiratory effort, when the flow rate was higher than 30 L/min, the PEEP levels of Group B were significantly lower than those of Group C (p < 0.05). In the AHRF model with normal inspiratory effort, when the flow rate was between 10 L/min and 60 L/min, the PEEP levels of Group B were significantly lower than those of Group C (p < 0.05). Moreover, in the COPD model with normal inspiratory effort, the PEEP levels of Group B were significantly lower than that of Group C only when the flow rate was 60 L/min (p < 0.05).
Conclusion:
The addition of different types of resistance valves to the high-flow exhalation end may be a feasible solution to improve the clinical efficacy of tracheotomized high-flow oxygen therapy.


Related Concept Videos
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:15
Respiratory Volumes
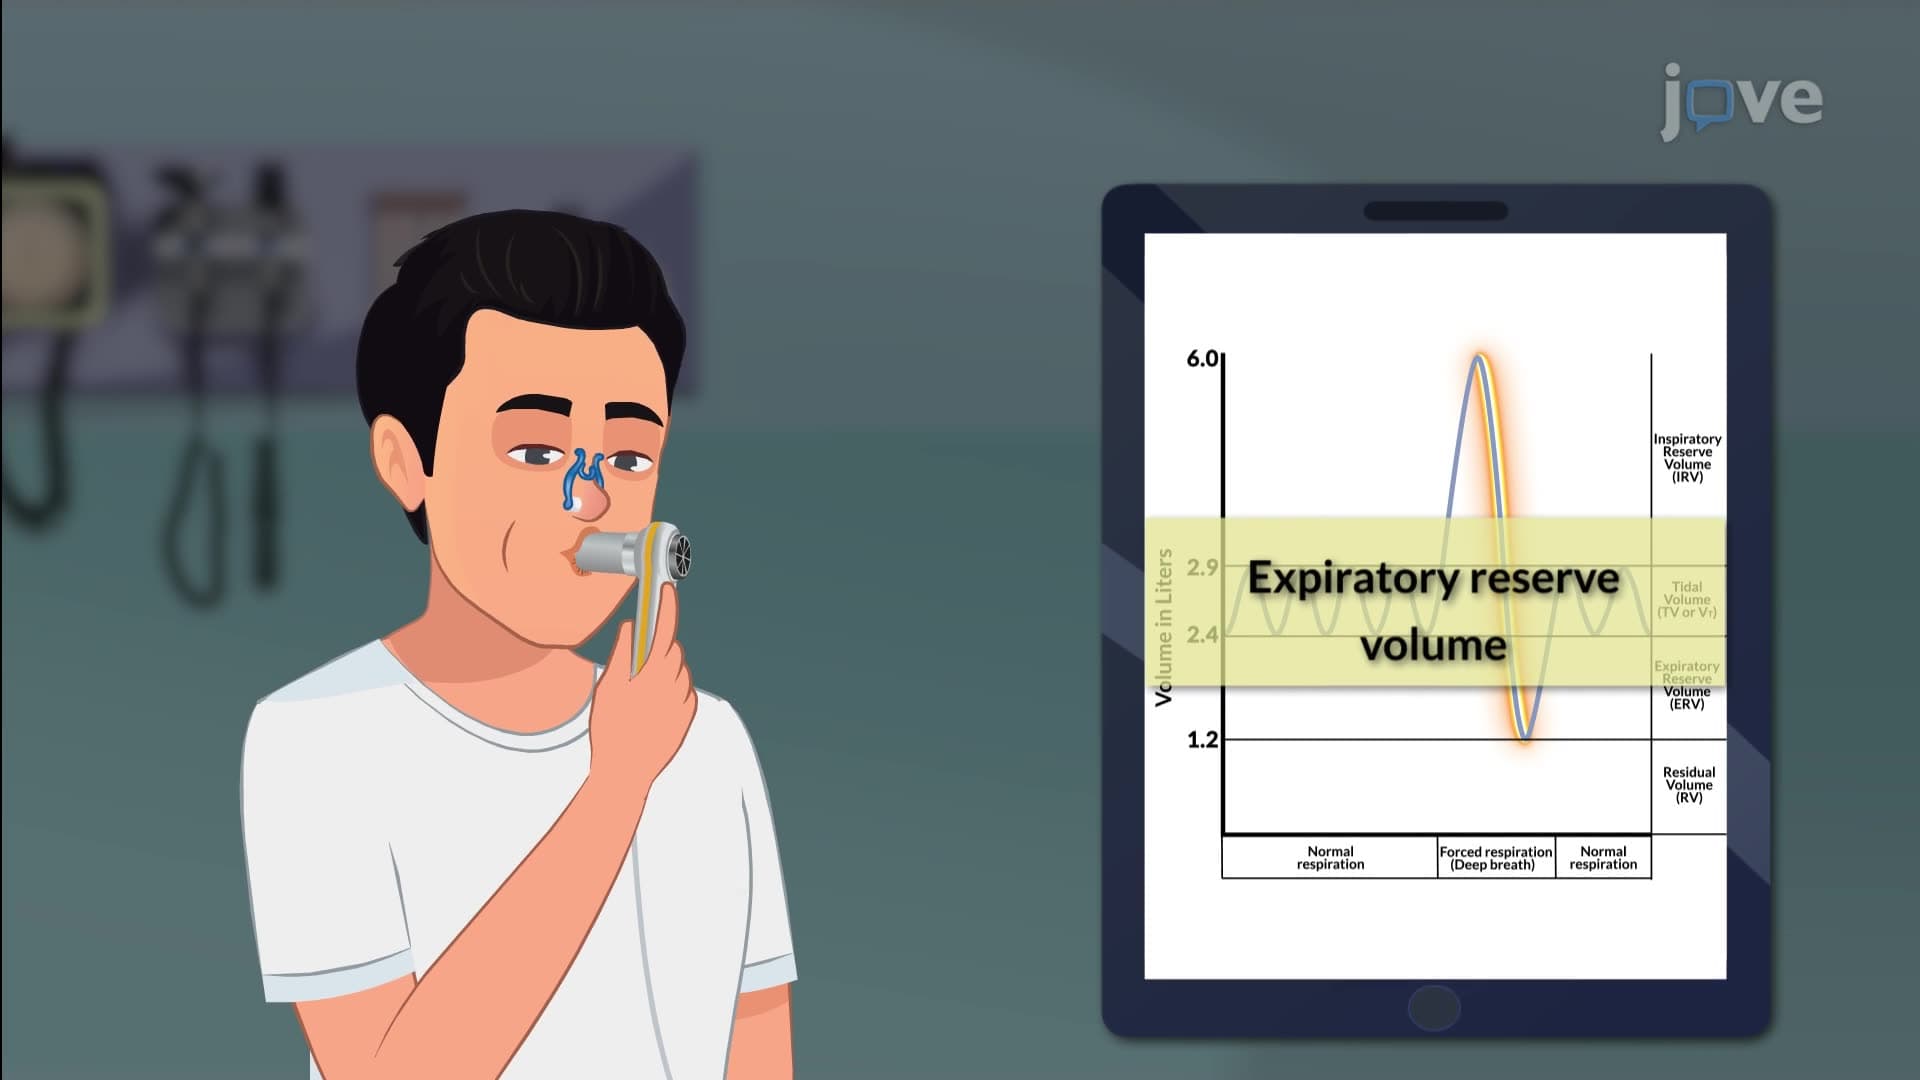
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:29
Mechanical Ventilation I: Indication and Settings