Related Experiment Video
Updated: Jul 17, 2025


Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Systemic Determinants of Exercise Intolerance in Patients With Fibrotic Interstitial Lung Disease and Severely
Reginald M Smyth1, Matthew D James1, Sandra G Vincent1
1Respiratory Investigation Unit, Division of Respirology, Department of Medicine, Queen's University and Kingston Health Sciences Centre, Kingston General Hospital, Kingston, Ontario, Canada.

Background:
The precise mechanisms driving poor exercise tolerance in patients with fibrotic interstitial lung diseases (fibrotic ILDs) showing a severe impairment in single-breath lung diffusing capacity for carbon monoxide (DLCO < 40% predicted) are not fully understood. Rather than only reflecting impaired O2 transfer, a severely impaired DLCO may signal deranged integrative physiologic adjustments to exercise that jointly increase the burden of exertional symptoms in fibrotic ILD.
Methods:
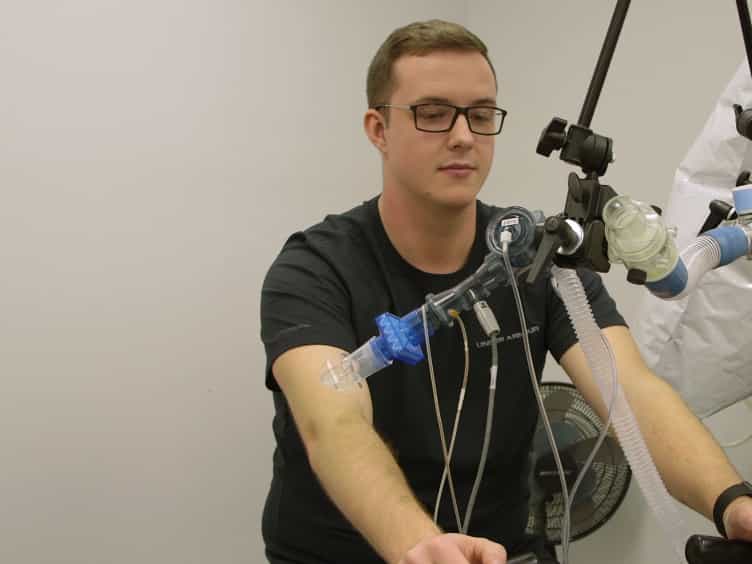
Sixty-seven subjects (46 with idiopathic pulmonary fibrosis, 24 showing DLCO < 40%) and 22 controls underwent pulmonary function tests and an incremental cardiopulmonary exercise test with serial measurements of operating lung volumes and 0-10 Borg dyspnea and leg discomfort scores.
Results:
Subjects from the DLCO < 40% group showed lower spirometric values, more severe restriction, and lower alveolar volume and transfer coefficient compared to controls and participants with less impaired DLCO (P < .05). Peak work rate was ∼45% (vs controls) and ∼20% (vs DLCO > 40%) lower in the former group, being associated with lower (and flatter) O2 pulse, an earlier lactate (anaerobic) threshold, heightened submaximal ventilation, and lower SpO . Moreover, critically high inspiratory constrains were reached at lower exercise intensities in the DLCO < 40% group (P < .05). In association with the greatest leg discomfort scores, they reported the highest dyspnea scores at a given work rate. Between-group differences lessened or disappeared when dyspnea intensity was related to indexes of increased demand-capacity imbalance, that is, decreasing submaximal, dynamic ventilatory reserve, and inspiratory reserve volume/total lung capacity (P > .05).
Conclusions:
A severely reduced DLCO in fibrotic ILD signals multiple interconnected derangements (cardiovascular impairment, an early shift to anaerobic metabolism, excess ventilation, inspiratory constraints, and hypoxemia) that ultimately lead to limiting respiratory (dyspnea) and peripheral (leg discomfort) symptoms. DLCO < 40%, therefore, might help in clinical decision-making to indicate the patient with fibrotic ILD who might derive particular benefit from pharmacologic and non-pharmacologic interventions aimed at lessening these systemic abnormalities.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 00:07
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...