Related Experiment Video
Updated: Jul 17, 2025


Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Contemporary Relationship Between Hospital Volume and Outcomes in Congenital Heart Surgery
Karl F Welke1, Tara Karamlou2, Sean M O'Brien3
1Division of Pediatric Cardiothoracic Surgery, Atrium Health Levine Children's Hospital, Charlotte, North Carolina.

Insights
Higher hospital volume in congenital heart surgery (CHS) is linked to better outcomes, particularly for complex procedures. Lower-volume centers show increased mortality and failure to rescue rates.
Area of Science:
- Cardiovascular Surgery
- Pediatric Surgery
- Health Services Research
Background:
- The relationship between hospital volume and outcomes in congenital heart surgery (CHS) requires updated analysis due to advancements in care.
- Recent decades have seen significant declines in mortality and evolution in case-mix adjustment methodologies for CHS.
Purpose of the Study:
- To investigate the current association between hospital volume and patient outcomes in congenital heart surgery.
- To identify specific thresholds or patterns in the volume-outcome relationship for CHS.
Main Methods:
- Analysis of The Society of Thoracic Surgeons-Congenital Heart Surgery Database (2017-2020) including patients aged ≤18 years.
- Bayesian hierarchical models were used to assess associations between annual hospital volume and adjusted operative mortality, major complications, failure to rescue (FTR), and postoperative length of stay (PLOS).
- Stratified analyses were performed by The Society of Thoracic Surgeons-European Association for Cardio-Thoracic Surgery (STAT) category and for the Norwood procedure.
Main Results:
- A total of 101 centers and 76,714 index operations were analyzed, with a median annual volume of 144 operations.
- Operative mortality was 2.7%, with higher rates observed at lower-volume hospitals, showing a notable increase below approximately 190 operations/year.
- The volume-outcome association was more pronounced for STAT 4-5 procedures and the Norwood procedure, impacting mortality and FTR, while PLOS and overall complications showed less volume dependency.
Conclusions:
- Hospital surgical volume is significantly associated with mortality and failure to rescue in congenital heart surgery.
- The volume-outcome relationship is particularly strong for high-risk congenital heart procedures.
- Findings provide evidence to support initiatives aimed at optimizing care quality and patient outcomes in CHS.
Background:
Studies examining the volume-outcome relationship in congenital heart surgery (CHS) are more than a decade old. Since then, mortality has declined, and case-mix adjustment has evolved. We determined the current relationship between hospital CHS volume and outcomes.
Methods:
Patients aged ≤18 years undergoing index operations in The Society of Thoracic Surgeons-Congenital Heart Surgery Database (2017-2020) were included. Associations between annual hospital volume and case-mix-adjusted operative mortality, major complications, failure to rescue (FTR), and postoperative length of stay (PLOS) were assessed using Bayesian hierarchical models, overall, by The Society of Thoracic Surgeons-European Association for Cardio-Thoracic Surgery (STAT) category, and for the Norwood procedure.
Results:
Across 101 centers (76,714 index operations), median annual volume was 144 operations/y. Operative mortality was 2.7%. Lower-volume hospitals had higher mortality, with an apparent transition zone at ∼190 operations/y (95% credible interval [CrI], 115-450 operations/y), below which a sustained uptick in the estimated odds of death occurred. Odds of death compared with a 450 operations/y reference were 50 operations/y (odds ratio [OR], 1.84; 95% CrI, 1.41-2.37), 100 operations/y (OR, 1.37; 95% CrI, 1.08-1.71), 200 operations/y (OR, 0.92; 95% CrI, 0.1-1.18), 300 operations/y (OR, 0.89; 95% CrI, 0.76-1.04). The volume-outcome effect was more apparent for STAT 4 to 5 than STAT 1 to 3 operations. In the overall cohort, PLOS and complications were similar across hospital volumes, whereas FTR rates were higher at lower-volume hospitals. Lower-volume hospitals had worse outcomes after the Norwood procedure, most notably mortality and FTR.
Conclusions:
Hospital volume is associated with mortality and FTR after CHS. The relationship is strongest for high-risk operations. These data can inform ongoing initiatives to improve CHS care.
More Related Videos
 09:15
Creation of Patient-Specific Silicone Cardiac Models with Applications in Pre-surgical Plans and Hands-on Training
Published on: February 10, 2022
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
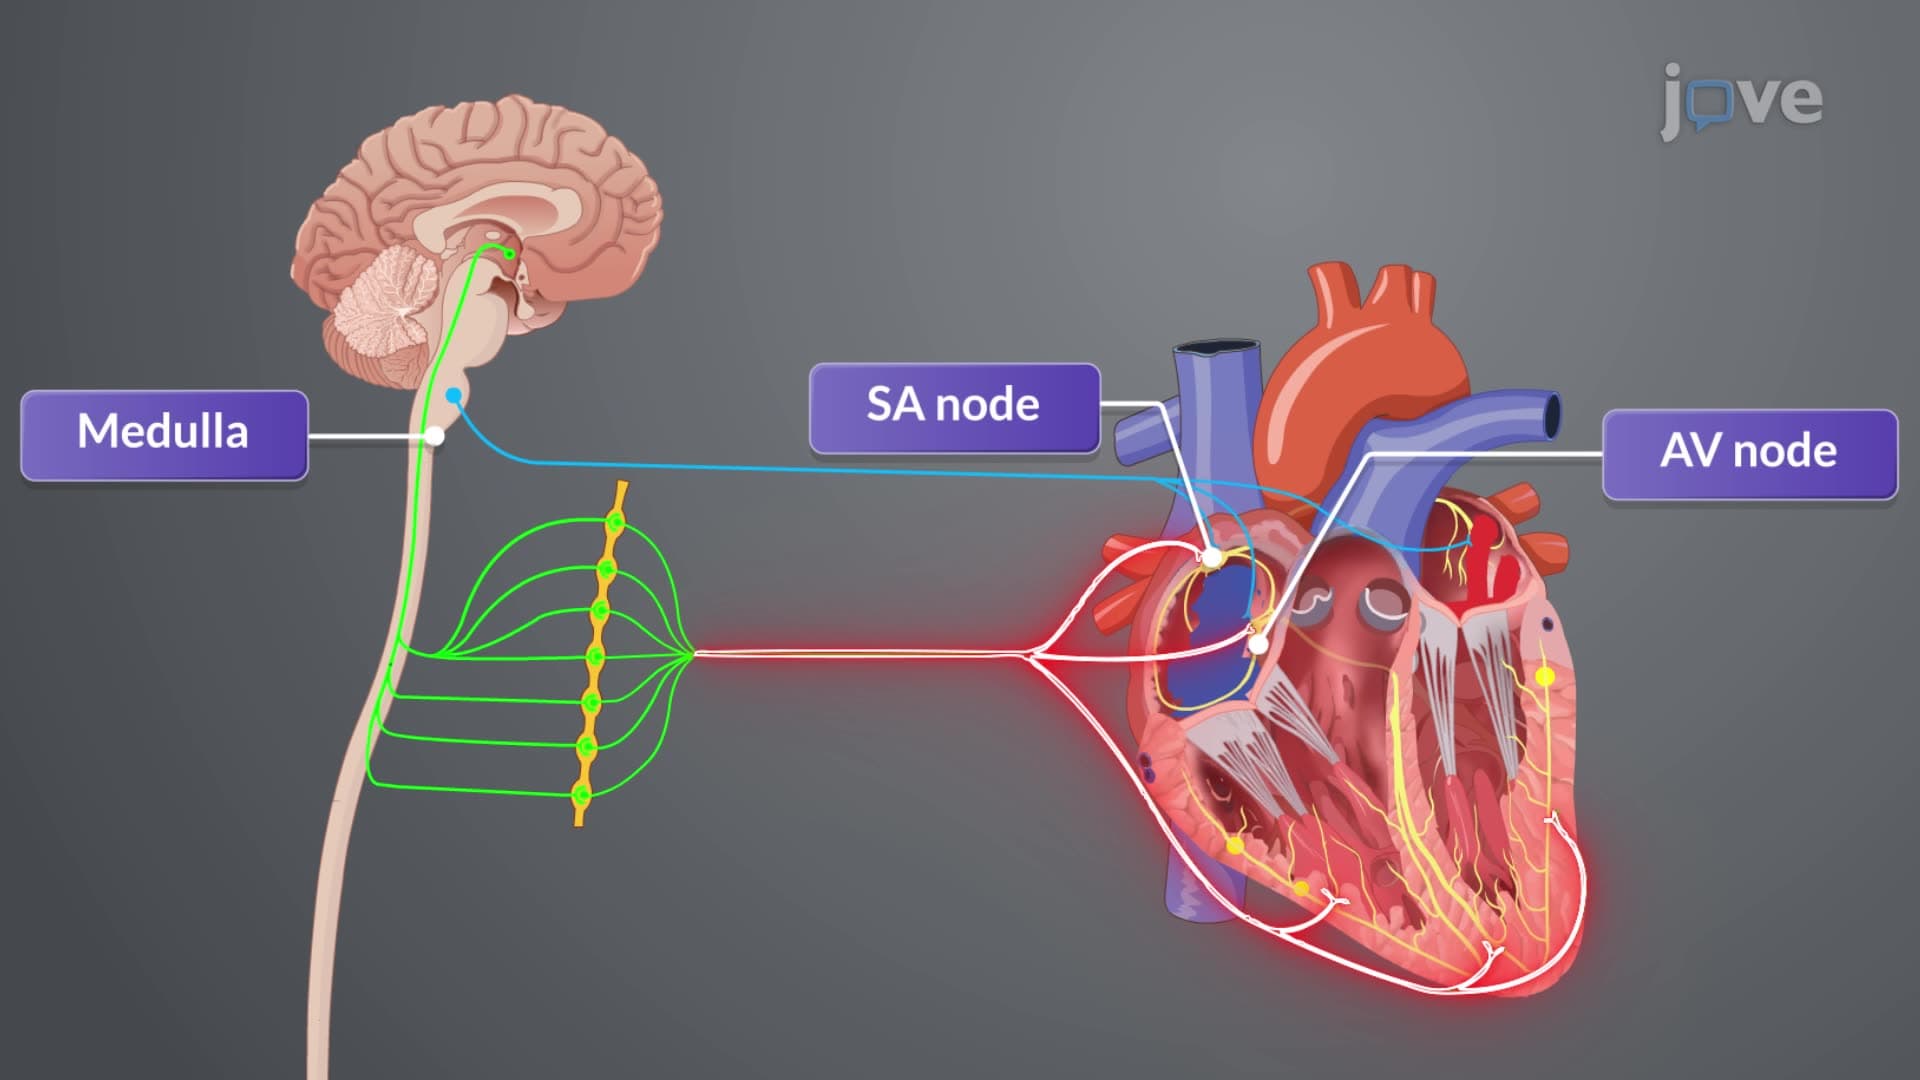
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:15
Respiratory Volumes
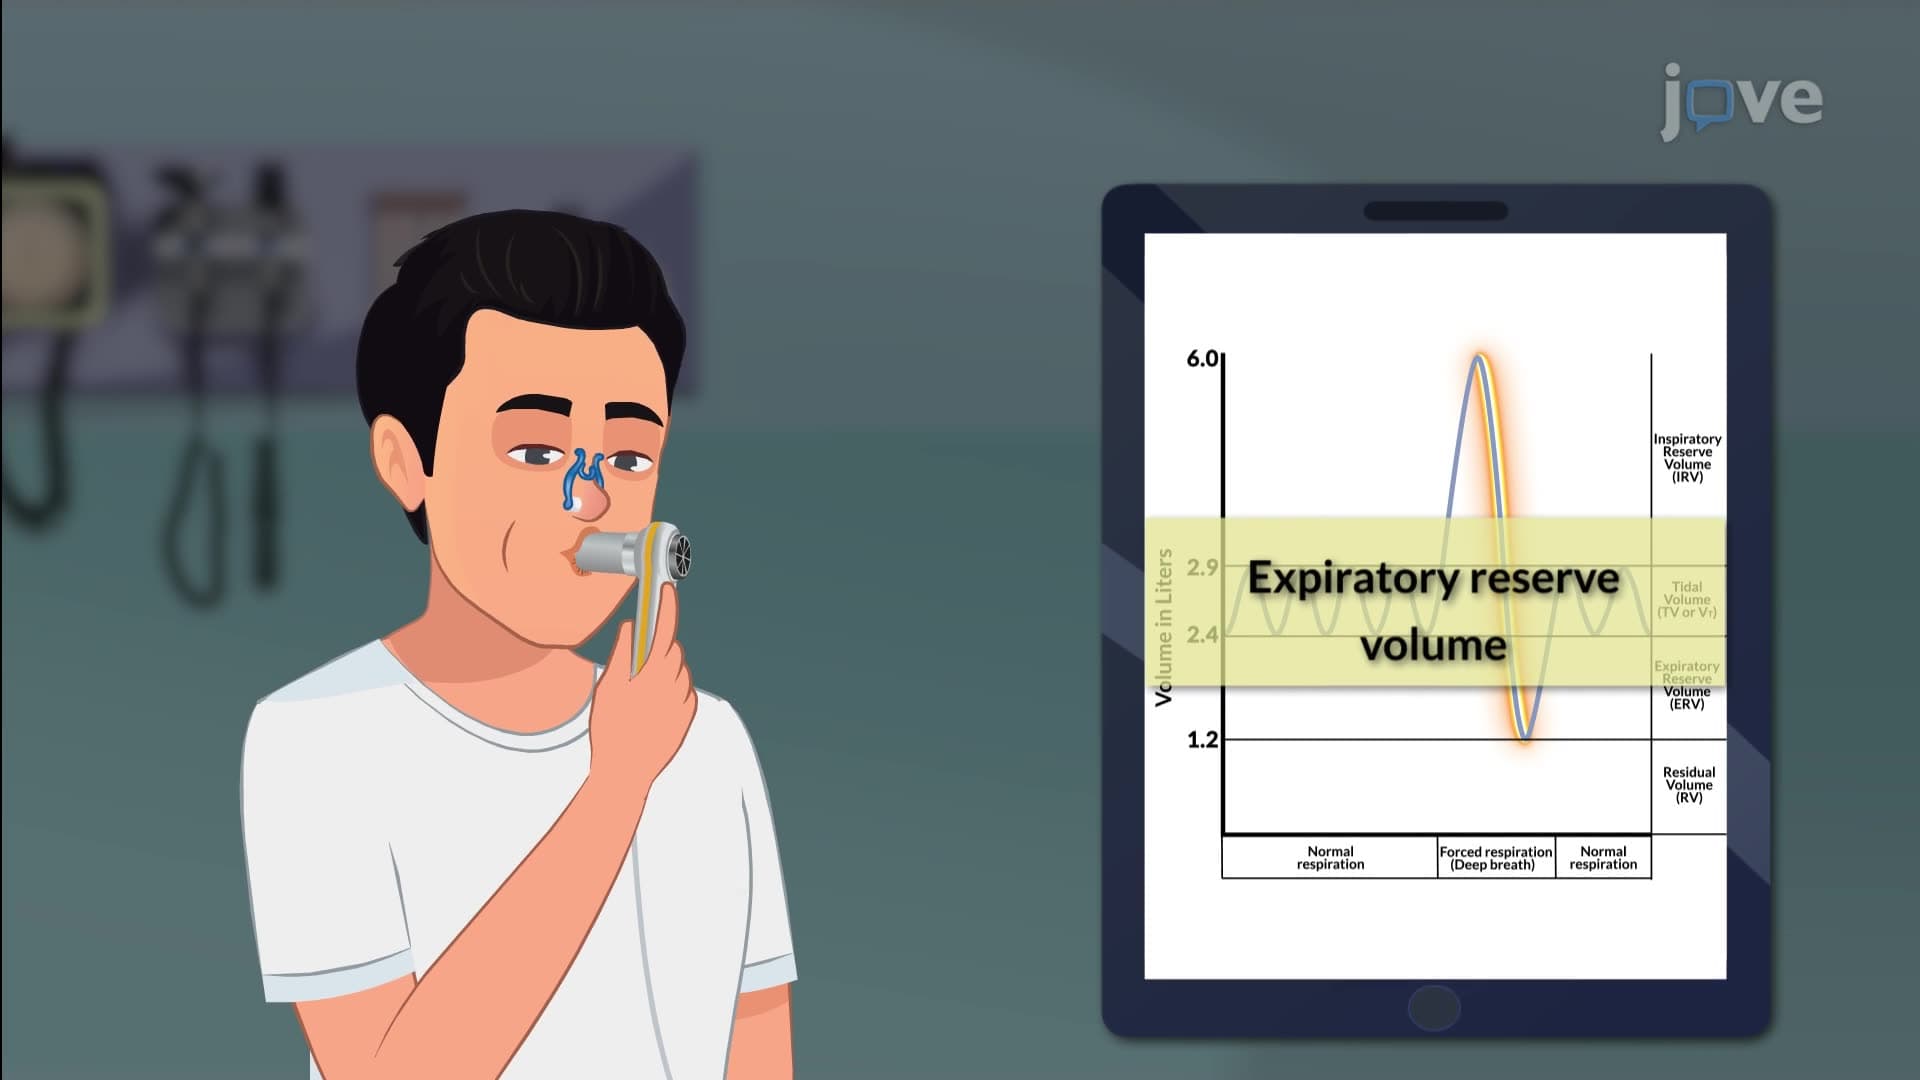
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...