Related Experiment Video
Updated: Jul 17, 2025
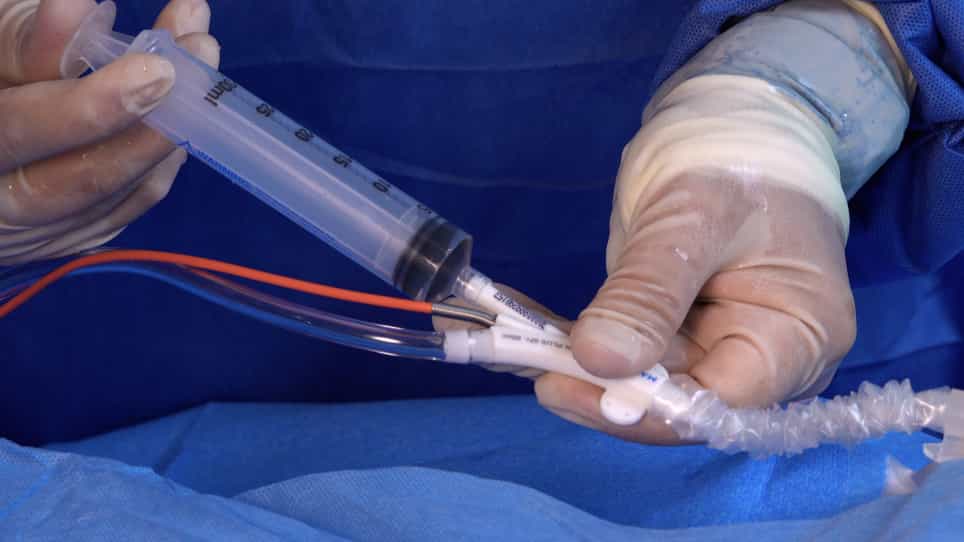

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Beta-blocker therapy in patients with acute myocardial infarction: not all patients need it
1Department of Internal Medicine, Jeju National University Hospital, Jeju National University College of Medicine, Jeju, Korea.

Insights
Beta-blockers show benefits for acute myocardial infarction (AMI) patients with reduced ejection fraction (EF). However, their benefit in patients with preserved EF remains unclear, necessitating further randomized trials.
Area of Science:
- Cardiology
- Clinical Research
- Pharmacology
Background:
- Evidence for beta-blocker benefits in acute myocardial infarction (AMI) largely predates modern treatments like statins and reperfusion therapy.
- In the reperfusion era, beta-blocker benefits are primarily established in patients with reduced ejection fraction (EF ≤40%).
- The increasing number of AMI survivors with mildly reduced (EF >40% to <50%) or preserved EF (≥50%) presents a clinical challenge regarding beta-blocker use.
Purpose of the Study:
- To investigate the efficacy of beta-blocker therapy in acute myocardial infarction (AMI) survivors with preserved or mildly reduced ejection fraction (EF).
- To evaluate the association between beta-blocker use at discharge and mortality in AMI survivors.
- To provide new insights into beta-blocker therapy for patients without reduced left ventricular systolic dysfunction post-AMI.
Main Methods:
- Analysis of registry data from the Korea Acute Myocardial Infarction Registry-National Institute of Health.
- Comparison of outcomes (including mortality) in in-hospital survivors of AMI based on ejection fraction (EF) and beta-blocker treatment at discharge.
- Stratification of patients into groups with reduced, mildly reduced, and preserved EF.
Main Results:
- Beta-blocker therapy at discharge was associated with improved outcomes in AMI patients with reduced or mildly reduced EF.
- No significant association between beta-blocker therapy at discharge and decreased mortality was observed in AMI survivors with preserved EF.
- Registry data suggest a lack of mortality benefit from oral beta-blockers in survivors without heart failure or left ventricular systolic dysfunction post-AMI.
Conclusions:
- Beta-blocker therapy may be beneficial for AMI patients with reduced or mildly reduced EF, but not for those with preserved EF.
- The optimal duration and benefit of oral beta-blockers in patients with mildly reduced or preserved EF remain questionable due to a lack of randomized clinical trials.
- Ongoing randomized clinical trials are crucial to definitively answer unresolved questions regarding beta-blocker therapy in all AMI patient populations.
Abstract:
Most of the evidences for beneficial effects of beta-blockers in patients with acute myocardial infarction (AMI) were from the clinical studies published in the pre-reperfusion era when anti-platelet drugs, statins or inhibitors of renin-angiotensin-aldosterone system which are known to reduce cardiovascular mortality of patients with AMI were not introduced. In the reperfusion era, beta-blockers' benefit has not been clearly shown except in patients with reduced ejection fraction (EF; ≤40%). In the era of the early reperfusion therapy for AMI, a number of patients with mildly reduced EF (>40%, <50%) or preserved EF (≥50%) become increasing. However, because no randomized clinical trials are available until now, the benefit and the optimal duration of oral treatment with beta-blockers in patients with mildly reduced or preserved EF are questionable. Registry data have not showed the association of oral beta-blocker therapy with decreased mortality in survivors without heart failure or left ventricular systolic dysfunction after AMI. In the Korea Acute Myocardial Infarction Registry-National Institute of Health of in-hospital survivors after AMI, the benefit of beta-blocker therapy at discharge was shown in patients with reduced or mildly reduced EF, but not in those with preserved EF, which provides new information about beta-blocker therapy in patients without reduced EF. However, clinical practice can be changed when the results of appropriate randomized clinical trials are available. Ongoing clinical trials may help to answer the unresolved issues of beta-blocker therapy in patients with AMI.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 07:40
Protection of H9c2 Myocardial Cells from Oxidative Stress by Crocetin via PINK1/Parkin Pathway-Mediated Mitophagy
Published on: May 26, 2023
Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow....
 01:14
Myocarditis III: Medical Management
 01:28
Antihypertensive Drugs: Types of β-Blockers