Related Experiment Video
Updated: Jul 17, 2025


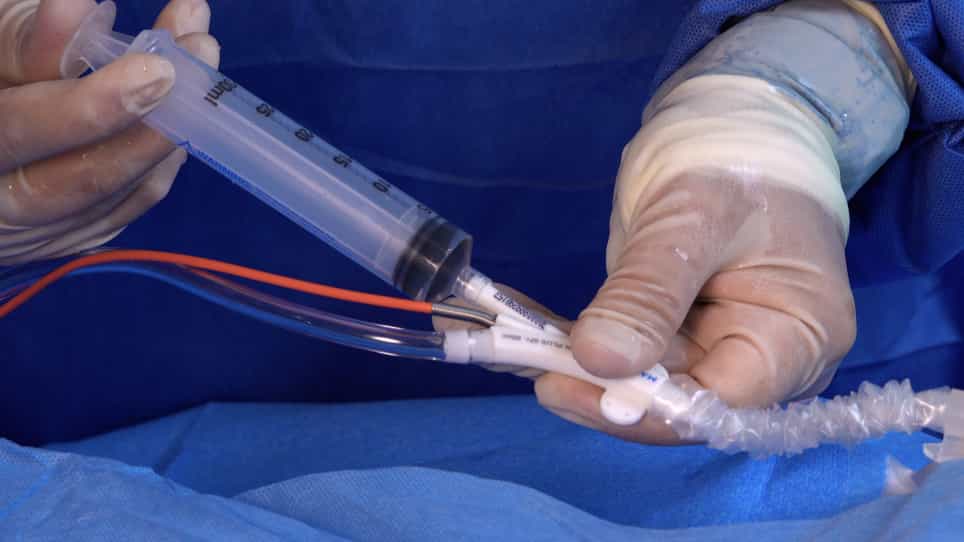
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Impact of Preprocedural Diastolic Blood Pressure on Outcomes in Patients Undergoing Percutaneous Coronary
Josephine Warren1, Diem Dinh2, Angela Brennan2
1Department of Cardiology, Alfred Hospital, Melbourne, Australia (J.W., C.T., M.D., J.S., D.S.).

Insights
Low diastolic blood pressure (DBP) below 50 mm Hg in patients undergoing percutaneous coronary intervention is linked to increased long-term mortality. This finding highlights the importance of monitoring DBP in cardiovascular care.
Area of Science:
- Cardiology
- Hypertension Management
- Interventional Cardiology
Background:
- Recent US hypertension guidelines advocate for lower blood pressure targets.
- Aggressive reduction of diastolic blood pressure (DBP) may compromise myocardial perfusion, especially in patients with coronary artery disease.
- The study addresses the potential risks of low DBP in patients with controlled systolic blood pressure.
Purpose of the Study:
- To investigate the long-term impact of low diastolic blood pressure (DBP) on mortality.
- To assess mortality risks in patients undergoing percutaneous coronary intervention (PCI) with well-controlled systolic blood pressure.
- To identify DBP thresholds associated with increased mortality post-PCI.
Main Methods:
- Analysis of 12,965 patients undergoing PCI between 2009 and 2018 from the Melbourne Interventional Group registry.
- Exclusion of patients with ST-elevation myocardial infarction, cardiogenic shock, or out-of-hospital arrest.
- Stratification of patients into five groups based on preprocedural DBP (<50, 50-59, 60-69, 70-79, ≥80 mm Hg) and analysis of long-term all-cause mortality using the Australian National Death Index.
Main Results:
- Patients with DBP <50 mm Hg were older and had higher rates of comorbidities including diabetes and renal impairment.
- A significantly higher 30-day mortality (2.5% vs. 0.7%) and long-term mortality (29% vs. 11%) was observed in the DBP <50 mm Hg group.
- Cox-regression analysis identified DBP <50 mm Hg as an independent predictor of long-term mortality (HR, 1.55; P=0.001).
Conclusions:
- Low diastolic blood pressure (<50 mm Hg) is an independent predictor of long-term mortality in patients undergoing percutaneous coronary intervention.
- These findings suggest that careful monitoring of DBP is crucial in patients with hypertension and coronary artery disease undergoing PCI.
- The study underscores the potential adverse effects of overly aggressive BP lowering on myocardial perfusion and patient outcomes.
Background:
Recent US guidelines recommend lower blood pressure (BP) targets in hypertension, but aggressive lowering of diastolic BP (DBP) can occur at the expense of myocardial perfusion, particularly in the presence of coronary artery disease. We sought to establish the long-term impact of low DBP on mortality among patients undergoing percutaneous coronary intervention with well-controlled systolic BP.
Methods:
We analyzed data from 12 965 patients undergoing percutaneous coronary intervention between 2009 and 2018 from the Melbourne Interventional Group registry who had a preprocedural systolic BP of ≤140 mm Hg. Patients with ST-elevation myocardial infarction, cardiogenic shock, and out-of-hospital arrest were excluded. Patients were stratified into 5 groups according to preprocedural DBP: <50, 50 to 59, 60 to 69, 70 to 79, and ≥80 mm Hg. The primary outcome was long-term, all-cause mortality. Mortality data were derived from the Australian National Death Index.
Results:
Patients with DBP<50 mm Hg were older with higher rates of diabetes, renal impairment, prior myocardial infarction, left ventricular dysfunction, peripheral and cerebrovascular disease (all P<0.001). Patients with DBP<50 mm Hg had higher 30-day (2.5% versus 0.7% for the other 4 quintiles; P<0.0001) and long-term mortality (median, 3.6 years; follow-up, 29% versus 11%; P<0.0001). Cox-regression analysis revealed that DBP<50 mm Hg was an independent predictor of long-term mortality (hazard ratio [HR], 1.55 [95% CI, 1.20-2.00]; P=0.001).
Conclusions:
In patients with well-controlled systolic BP undergoing percutaneous coronary intervention, low DBP (<50 mm Hg) is an independent predictor of long-term mortality.
Related Concept Videos
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:17
Measurement of Blood Pressure
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.