Related Experiment Video
Updated: Jul 17, 2025
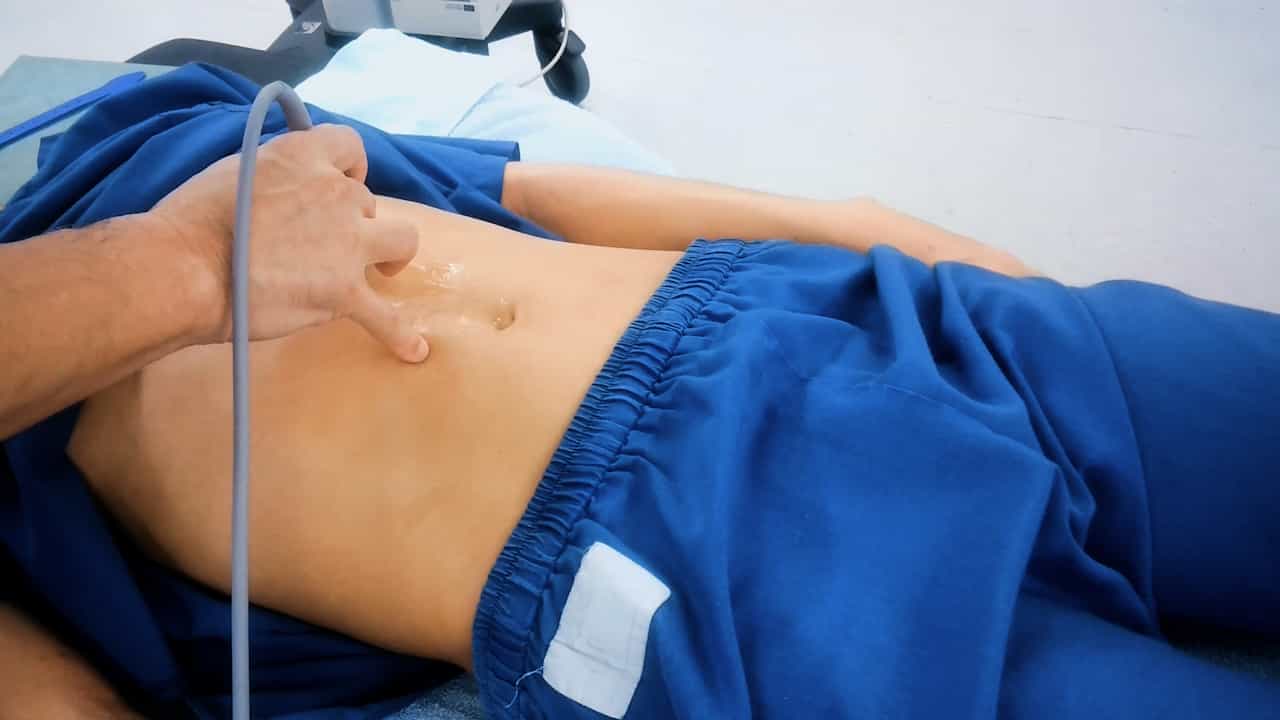

Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
Survival, Reintervention, and Value of Open and Endovascular Repair for Chronic Mesenteric Ischemia
Daniel J Lehane1, Joshua T Geiger1, Zachary R Zottola1
1Division of Vascular Surgery, University of Rochester Medical Center, Rochester, NY.

Insights
Long-term survival after chronic mesenteric ischemia (CMI) treatment is not affected by open repair (OR) or endovascular repair (ER). Patient comorbidities, not the procedure, dictate mortality risk, while ER offers superior long-term value.
Area of Science:
- Vascular Surgery
- Gastroenterology
- Health Services Research
Background:
- Limited large-scale cohort analyses exist for chronic mesenteric ischemia (CMI) survival and outcomes.
- Current guidelines suggest open repair (OR) for younger, healthier patients or poor endovascular repair (ER) candidates.
- This study compares long-term survival, reintervention rates, and value between OR and ER for CMI.
Purpose of the Study:
- To investigate long-term survival differences between open repair (OR) and endovascular repair (ER) for chronic mesenteric ischemia (CMI).
- To compare reintervention rates and procedural value between OR and ER in CMI patients.
- To identify factors influencing mortality in CMI patients undergoing surgical intervention.
Main Methods:
- Retrospective cohort analysis of the New York statewide all-payer database (2000-2014).
- Propensity-matched analysis comparing 1-year and 5-year survival and reintervention rates for OR versus ER.
- Cox proportional hazards and linear regression models used to assess mortality factors and procedural value.
Main Results:
- No significant difference in 1-year or 5-year survival between OR and ER groups.
- Congestive heart failure, cancer, and dysrhythmia were associated with 1-year mortality.
- Cancer, congestive heart failure, chronic pulmonary disease, and age correlated with 5-year mortality.
- Endovascular repair (ER) showed increased reintervention at 5 years but superior 5-year procedural value.
Conclusions:
- Long-term mortality after CMI intervention is independent of treatment modality (OR vs. ER).
- Patient comorbidities, not the surgical approach, are the primary drivers of mortality.
- Treatment selection for CMI should prioritize anatomic suitability and long-term value, favoring ER when feasible.
Background:
There are limited analyses of survival and postoperative outcomes in chronic mesenteric ischemia (CMI) using data from large cohorts. Current guidelines recommend open repair (OR) for younger, healthier patients when long-term benefits outweigh increased perioperative risks or for poor endovascular repair (ER) candidates. This study investigates whether long-term survival, reintervention, and value differ between these treatment modalities.
Methods:
A retrospective cohort analysis was performed on data extracted from the Statewide Planning and Research Cooperative System, the New York statewide all-payer database containing demographics, diagnoses, treatments, and charges. Patients were selected for CMI and subsequent ER or OR using International Classification of Diseases, Ninth Revision codes. Patients with peripheral arterial disease were excluded to account for ambiguity in the International Classification of Diseases, Ninth Revision procedure code for angioplasty of noncoronary vessels, which includes angioplasty of upper and lower extremity vessels. Kaplan-Meier analysis was used to compare 1-year and 5-year survival and reintervention between treatment modalities using a propensity-matched cohort. Cox proportional hazards testing was performed to find factors associated with 1-year and 5-year survival and reintervention. Analysis of procedural value was performed using linear regression.
Results:
From 2000 to 2014, 744 patients met inclusion criteria. Of these, 209 (28.1%) underwent OR and 535 (71.9%) ER. No difference between propensity-matched groups was found in 1-year (P = 0.46) or 5-year (P = 0.91) survival. Congestive heart failure (hazard ratio [HR]: 2.8, 95% confidence interval [CI]: 1.7-4.4; P < 0.01), cancer (HR: 2.8, 95% CI: 1.3-5.8; P < 0.01), and dysrhythmia (HR: 1.8, 95% CI: 1.1-2.8; P = 0.02) correlated with 1-year mortality. Cancer (HR: 2.9, 95% CI: 1.6-5.5; P < 0.01), congestive heart failure (HR: 2.2, 95% CI: 1.5-3.2; P < 0.01), chronic pulmonary disease (HR: 1.4, 95% CI: 1.0-2.0; P = 0.04), and age (HR: 1.03, 95% CI: 1.01-1.05; P < 0.01) correlated with 5-year mortality. Treatment modality was not associated with reintervention at 1 year on Kaplan-Meier analysis (P = 0.29). However, ER showed increased instances of reintervention at 5 years (P < 0.01). Additionally, ER was associated with an increased 5-year value (0.7 ± 0.9 vs. 0.5 ± 0.5 life years/charges at index admission [$10k], P < 0.01; b coefficient: 0.2, 95% CI: 0.1-0.4, P < 0.01).
Conclusions:
This is the largest retrospective propensity-matched single-study cohort to analyze long-term survival outcomes after intervention for CMI. Long-term mortality was independent of treatment modality and rather was associated with patient comorbidities. Therefore, treatment selection should depend on anatomic considerations and long-term value. ER should be considered over OR in patients with amenable anatomy based on the superior procedural value.
More Related Videos
 07:05
Visualization of Neutrophil Extracellular Traps in Mesenteric Venules After Mesenteric Ischemia-Reperfusion Injury via Intravital Microscopy
Published on: September 27, 2024
 04:57
Author Spotlight: Advancing Spectral Characterization of Physiological and Malperfused Tissues
Published on: July 5, 2024
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:27
Peripheral Artery Disease III: Interprofessional Care