Related Experiment Video
Updated: Jul 17, 2025
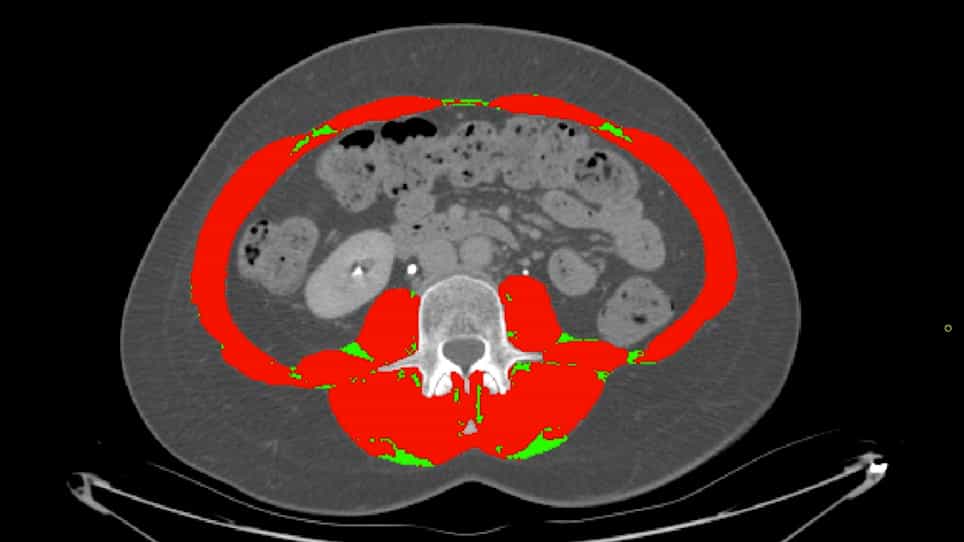

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Sarcopenic Obesity Phenotypes in Patients With HIV: Implications for Cardiovascular Prevention and Rehabilitation
Jovana Milic1, Stefano Calza2, Samuele Cantergiani3
1Department of Surgical, Medical, Dental and Morphological Sciences, University of Modena and Reggio Emilia, Modena, Italy.

Background:
We aimed to describe prevalence, incidence, and risk factors for sarcopenic obesity (SO) phenotypes in people living with HIV (PWH) and their association with subclinical cardiovascular disease (CVD).
Methods:
Observational, longitudinal study of PWH. A minimum of 1 criterion was necessary to diagnose sarcopenia: weak hand grip (HG), low appendicular skeletal muscle index (ASMI), short physical performance battery (SPPB < 11). Obesity was defined as body mass index (BMI) ≥ 30 kg/m2 or visceral adipose tissue (VAT) ≥ 160 cm2. These variables combined generated 5 SO phenotypes: severe SO: low HG + low ASMI + low SPPB + high BMI; SO1: weak HG + high VAT; SO2: weak HG + high BMI; SO3: low ASMI + high VAT; SO4: low ASMI + high BMI. Subclinical CVD was defined as carotid intima-media thickness (IMT) ≥ 1 mm, presence of carotid plaque, or coronary artery calcification (CAC) score > 10.
Results:
Among 2379 male PWH 72%, median age was 52 years, median HIV vintage 21 years, and median BMI 24 kg/m2. Two PWH had severe SO. The prevalence of SO1-SO4 was 19.7%, 3.6%, 20.8% and 0.8%, respectively. Incidence of SO1-SO4 was 6.90, 1.2, 5.6, and 0.29 × 100 person-years, respectively. SO1 was associated with risk of IMT ≥ 1, and SO3 with risk of CAC score > 10.
Conclusions:
There was a large variability in incidence and prevalence of SO phenotypes. The presence of SO may have important implications for cardiovascular prevention and cardiac rehabilitation of PWH who suffered events.

Related Concept Videos
 01:24
Obesity
 01:30
Coronary Artery Disease I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
Coronary Artery Disease IV: Preventive Measures