Related Experiment Video
Updated: Jul 17, 2025
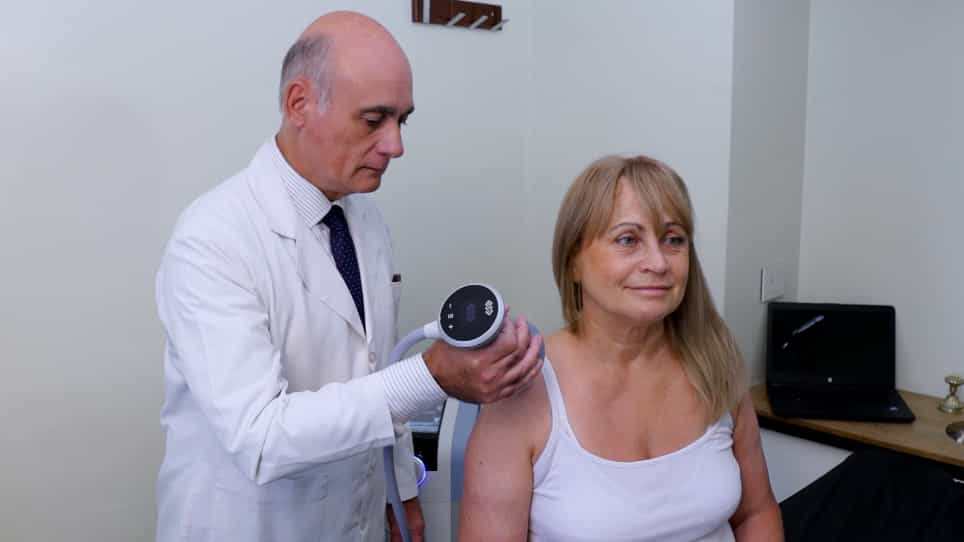

Treatment Protocol for Rotator Cuff Calcific Tendinitis Using a Single-Crystal Piezoelectric Focused Shock Wave Source
Published on: December 23, 2022
Coronary intravascular lithotripsy and rotational atherectomy for severely calcified stenosis: Results from the
F Blachutzik1, S Meier1, M Weissner2
1Medizinische Klinik 1, Justus Liebig Universität Giessen, Giessen, Germany.

Insights
Coronary intravascular lithotripsy (IVL) is non-inferior to rotational atherectomy (RA) for achieving minimal stent area in severely calcified lesions. Both procedures showed similar stent expansion and procedural outcomes.
Area of Science:
- Interventional Cardiology
- Cardiovascular Devices
- Medical Imaging
Background:
- Severely calcified coronary lesions pose significant challenges during percutaneous coronary intervention.
- Effective lesion preparation is crucial for optimal stent deployment and long-term outcomes.
Purpose of the Study:
- To compare the efficacy and safety of coronary intravascular lithotripsy (IVL) versus rotational atherectomy (RA) in treating severely calcified coronary lesions.
- To determine if IVL is non-inferior to RA in terms of minimal stent area (MSA).
Main Methods:
- A randomized, prospective non-inferiority trial (ROTA.shock) enrolled 70 patients.
- Patients were randomized (1:1) to undergo either IVL or RA prior to stenting.
- Optical coherence tomography (OCT) was used to assess the primary endpoint, MSA, post-procedure.
Main Results:
- The mean MSA was non-inferior after IVL (6.10 mm²) compared to RA (6.60 mm²), with a difference of -0.50 mm².
- Stent expansion was similar between the IVL and RA groups (0.82 vs. 0.83, p=0.79).
- No significant differences were observed in contrast media consumption, radiation dose, or procedure time between the two groups.
Conclusions:
- Coronary intravascular lithotripsy (IVL) is non-inferior to rotational atherectomy (RA) regarding minimal stent area in severely calcified coronary lesions.
- Both IVL and RA achieve similar stent expansion, with comparable procedural safety and efficiency profiles.
Background:
Severely calcified coronary lesions present a particular challenge for percutaneous coronary intervention.
Aims:
The aim of this randomized study was to determine whether coronary intravascular lithotripsy (IVL) is non-inferior to rotational atherectomy (RA) regarding minimal stent area (MSA).
Methods:
The randomized, prospective non-inferiority ROTA.shock trial enrolled 70 patients between July 2019 and November 2021. Patients were randomly (1:1) assigned to undergo either IVL or RA before percutaneous coronary intervention of severely calcified coronary lesions. Optical coherence tomography was performed at the end of the procedure for primary endpoint analysis.
Results:
The primary endpoint MSA was lower but non-inferior after IVL (mean: 6.10 mm2 , 95% confidence interval [95% CI]: 5.32-6.87 mm2 ) versus RA (6.60 mm2 , 95% CI: 5.66-7.54 mm2 ; difference in MSA: -0.50 mm2 , 95% CI: -1.52-0.52 mm2 ; non-inferiority margin: -1.60 mm2 ). Stent expansion was similar (RA: 0.83 ± 0.10 vs. IVL: 0.82 ± 0.11; p = 0.79). There were no significant differences regarding contrast media consumption (RA: 183.1 ± 68.8 vs. IVL: 163.3 ± 55.0 mL; p = 0.47), radiation dose (RA: 7269 ± 11288 vs. IVL: 5010 ± 4140 cGy cm2 ; p = 0.68), and procedure time (RA: 79.5 ± 34.5 vs. IVL: 66.0 ± 19.4 min; p = 0.18).
Conclusion:
IVL is non-inferior regarding MSA and results in a similar stent expansion in a random comparison with RA. Procedure time, contrast volume, and dose-area product do not differ significantly.


