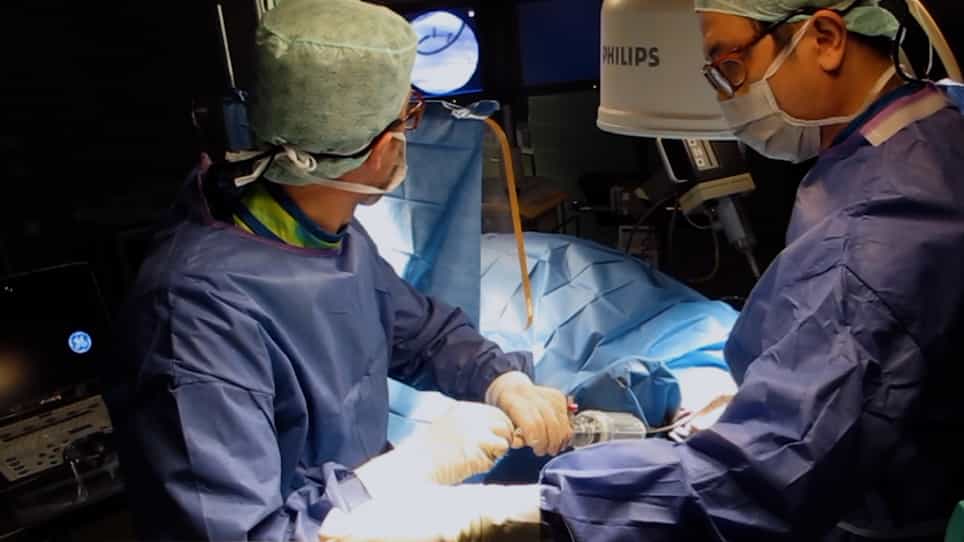
Transthoracic device closure of perimembranous ventricular septal defect via a small left intercostal incision in children
Related Experiment Video
Updated: Jul 17, 2025

Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
Linfeng Xie1,2, Guican Zhang1,3, Jian He1,2
1Department of Cardiovascular Surgery, Fujian Medical University Union Hospital, Fuzhou, China.

Insights
Transthoracic device closure using a small incision offers a safe and effective alternative for pediatric perimembranous ventricular septal defects, reducing recovery time and improving cosmetic outcomes compared to traditional surgery.
Area of Science:
- Pediatric Cardiac Surgery
- Interventional Cardiology
- Minimally Invasive Procedures
Background:
- Surgical repair of perimembranous ventricular septal defects (VSD) in children necessitates sternotomy, leading to significant scarring and potential long-term distress.
- Current transcatheter device closure methods for VSD are constrained by limitations such as vascular diameter, radiation exposure, and specialized equipment costs.
- An ultra-small left intercostal incision approach for transthoracic device closure was developed to mitigate the drawbacks of existing VSD treatment modalities.
Purpose of the Study:
- To investigate the safety and feasibility of transthoracic device closure for perimembranous VSD in children using an ultra-small left intercostal incision.
- To compare the outcomes of this novel approach with traditional surgical repair in a pediatric cohort.
Main Methods:
- A retrospective analysis was conducted on 358 children diagnosed with perimembranous VSD.
- The study cohort was divided into two groups: 152 patients underwent surgical closure, and 206 patients received transthoracic device closure via an ultra-small left intercostal incision.
- Perioperative data and postoperative follow-up results were collected and compared between the two treatment groups.
Main Results:
- Both treatment groups demonstrated similar success rates (203/206 vs. 152/152).
- The device closure group exhibited significantly shorter operative times, ICU stays, mechanical ventilation durations, and hospital stays compared to the surgical group.
- The ultra-small incision (1.1 cm) resulted in no thoracic deformities, unlike the surgical group (11 cases), with comparable hospitalization costs and a slightly higher incidence of small residual shunts in the device group, which resolved during follow-up.
Conclusions:
- Transthoracic device closure through an ultra-small left intercostal incision, guided by transesophageal echocardiography, is a safe and feasible procedure for pediatric perimembranous VSD.
- This minimally invasive technique offers a viable alternative to surgical repair, particularly when specific indications are met, providing improved cosmetic results and faster recovery.
Background:
In children with perimembranous ventricular septal defect, surgical repair requires sternotomy and leaves unsightly scars, which can trigger long-term physical and psychological distress. However, transcatheter device closure is limited by vascular diameter, radiographic exposure, and expensive DSA equipment. We used an ultra-small left intercostal incision for transthoracic device closure to avoid the above problems and investigated its safety and feasibility by comparing it with surgical repair.
Methods:
This study enrolled 358 children with perimembranous ventricular septal defect. Among them, 152 patients were treated by surgical closure and 206 by transthoracic device closure via an ultra-small left intercostal incision. Perioperative clinical data and postoperative follow-up results were collected and analyzed retrospectively.
Results:
The success rate was similar (P = 0.265) in the two groups: 203/206 patients in the device group vs. 152/152 patients in the surgical group. The operative time, intensive care unit time, mechanical ventilation time, and postoperative hospital stay were significantly shorter in the device group than in the surgical group. Although the incision length of the device group (1.1 ± 0.2 cm) was significant shorter (P < 0.001) than that of the surgical group (6.7 ± 1.5 cm), there was no difference in hospitalization costs between the two groups (P = 0.099). Except for small residual shunt (16/206 vs. 3/152, P = 0.017), the incidence of complications in the device group was lower or equal to that in the surgical group, and all small residual shunt disappeared during follow-up. There was no thoracic deformity in the device group, compared with 11 cases in the surgery group during follow-up (P < 0.001).
Conclusions:
Transthoracic device closure via an ultra-small left intercostal incision under transesophageal echocardiography guidance is safe and feasible. With appropriate indications, it can be a suitable alternative to surgical closure for treating perimembranous ventricular septal defect in children.