Effects of inflammation, childhood adversity, and psychiatric symptoms on brain morphometrical phenotypes in bipolar II depression
Related Experiment Video
Updated: Jul 17, 2025

Rapid Fractionation and Isolation of Whole Blood Components in Samples Obtained from a Community-based Setting
Published on: November 30, 2015
Yuan Cao1,2,3, Huan Sun4, Paulo Lizano5,6
1Department of Nuclear Medicine, West China Hospital of Sichuan University, Chengdu 610041, P.R. China.

Background:
The neuroanatomical alteration in bipolar II depression (BDII-D) and its associations with inflammation, childhood adversity, and psychiatric symptoms are currently unclear. We hypothesize that neuroanatomical deficits will be related to higher inflammation, greater childhood adversity, and worse psychiatric symptoms in BDII-D.
Methods:
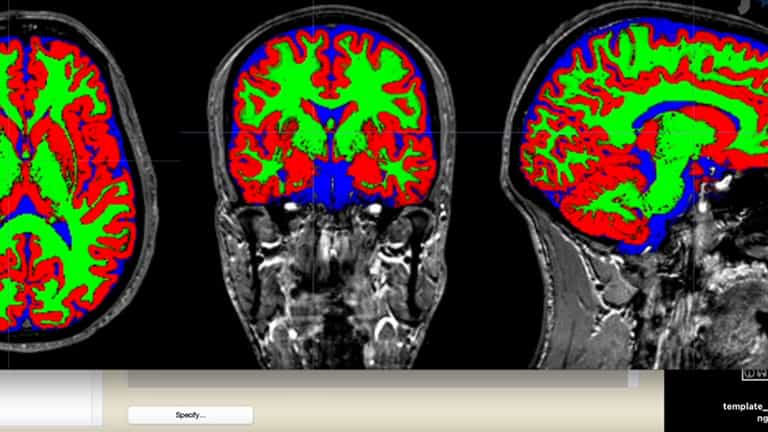
Voxel- and surface-based morphometry was performed using the CAT toolbox in 150 BDII-D patients and 155 healthy controls (HCs). Partial Pearson correlations followed by multiple comparison correction was used to indicate significant relationships between neuroanatomy and inflammation, childhood adversity, and psychiatric symptoms.
Results:
Compared with HCs, the BDII-D group demonstrated significantly smaller gray matter volumes (GMVs) in frontostriatal and fronto-cerebellar area, insula, rectus, and temporal gyrus, while significantly thinner cortices were found in frontal and temporal areas. In BDII-D, smaller GMV in the right middle frontal gyrus (MFG) was correlated with greater sexual abuse (r = -0.348, q < 0.001) while larger GMV in the right orbital MFG was correlated with greater physical neglect (r = 0.254, q = 0.03). Higher WBC count (r = -0.227, q = 0.015) and IL-6 levels (r = -0.266, q = 0.015) was associated with smaller GMVs in fronto-cerebellar area in BDII-D. Greater positive symptoms was correlated with larger GMVs of the left middle temporal pole (r = 0.245, q = 0.03).
Conclusions:
Neuroanatomical alterations in frontostriatal and fronto-cerebellar area, insula, rectus, temporal gyrus volumes, and frontal-temporal thickness may reflect a core pathophysiological mechanism of BDII-D, which are related to inflammation, trauma, and psychiatric symptoms in BDII-D.

Related Concept Videos
 01:30
Bipolar Disorder
 01:29
Biological Causes of Schizophrenia
Genetic Factors in Schizophrenia
The genetic basis of schizophrenia is strongly supported by family and twin...
 01:30
Attention-Deficit/Hyperactivity Disorder
Diagnostic Criteria and Symptoms
To diagnose ADHD, symptoms must manifest before age 12 and be evident across multiple settings....
 01:29
Psychological and Sociocultural Causes of Schizophrenia
 01:30
Stress and Mental Health
Individuals with depression often experience challenges in both their personal and professional...
 01:28
Human Genetics
The complex relationship between genetics and psychology is observable through common biological components such...