Related Experiment Video
Updated: Jul 16, 2025
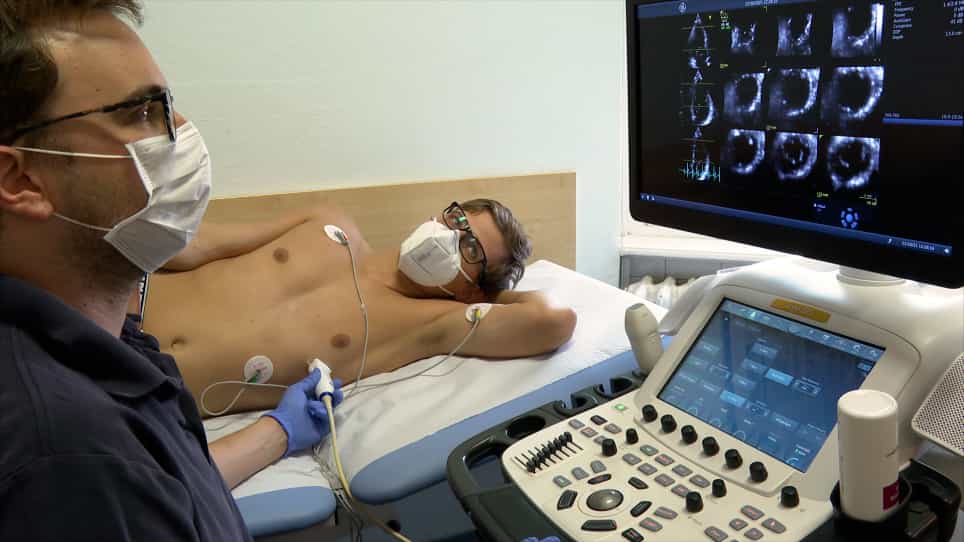

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Changes of left atrial morphology and function evaluated with four-dimensional automated left atrial quantification
Yumeng Xing1, Yinjia Zhang1, Rui Zhao2
1Department of Ultrasound, Huadong Hospital, Fudan University, 221 West Yanan Road, Shanghai 200040, China.

Background:
Coronary slow flow phenomenon (CSFP) can cause left ventricular diastolic dysfunction (LVDD). In multiple studies, the left atrial (LA) strain has been reported to be an excellent parameter for assessing LVDD. The 4-dimensional automated LA quantification (4D Auto LAQ) dedicated to the LA was recently available. Our study aimed to evaluate subclinical changes in LA morphology and function with 4D Auto LAQ in patients with CSFP and preserved left ventricular ejection fraction (LVEF).
Methods:
Forty-eight patients with CSFP confirmed with coronary angiography and 46 age and gender-matched controls with normal coronary flow were enrolled. The thrombolysis in myocardial infarction frame count (TFC) method was used to record coronary blood flow velocities for each major coronary artery. LA volume, LA longitudinal and circumferential strains during each of the three LA phases (reservoir, conduit, and contraction), LA total emptying fraction (LATEF), LA active emptying fraction (LAAEF), and LA passive emptying fraction (LAPEF) were quantified with 4D Auto LAQ analysis.
Results:
Compared with controls, LA longitudinal reservoir strain (LASr), LA longitudinal strain during the conduit phase (LAScd), LA contraction strain (LASct), LA conduit circumferential strain (LAScd-c), LATEF, LAPEF decreased significantly in individuals with CSFP. Of the 4D- LAQ parameters, only LASr [odds ratio (OR): 0.773, P < 0.001] and LATEF [OR: 0.762, P < 0.001] were associated with CSFP in multivariate analysis. A LASr ≤23.00% can differentiate CSFP from controls [sensitivity, 66.7%; specificity, 93.5%; area under the curve (AUC), 0.823; P < 0.001]. A LASr of ≤19.00% could predict the elevation of LV filling pressure in the CSFP cohort [sensitivity, 76.9%; specificity, 74.3%; area under the curve (AUC), 0.792; P < 0.001]. LASr was the only index to demonstrate significant changes compared to controls in single-vessel CSFP. Compared to the right coronary artery (RCA) and left circumflex (LCX), TFC of the left anterior descending (LAD) artery was the only independent variable of LASr (Standardized Coefficients: -0.386, P = 0.037).
Conclusions:
Impairment of LA reservoir function reflected by changes in LASr and LATEF can be seen in patients with CSFP. LASr could predict the elevation of LV filling pressure in CSFP individuals. LASr is more sensitive than LATEF in detecting LA reservoir dysfunction in single-vessel CSFP. CSFP in LAD exerts a more prominent influence on LASr than RCA or LCX.
More Related Videos

Related Concept Videos
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy