Related Experiment Video
Updated: Jul 16, 2025
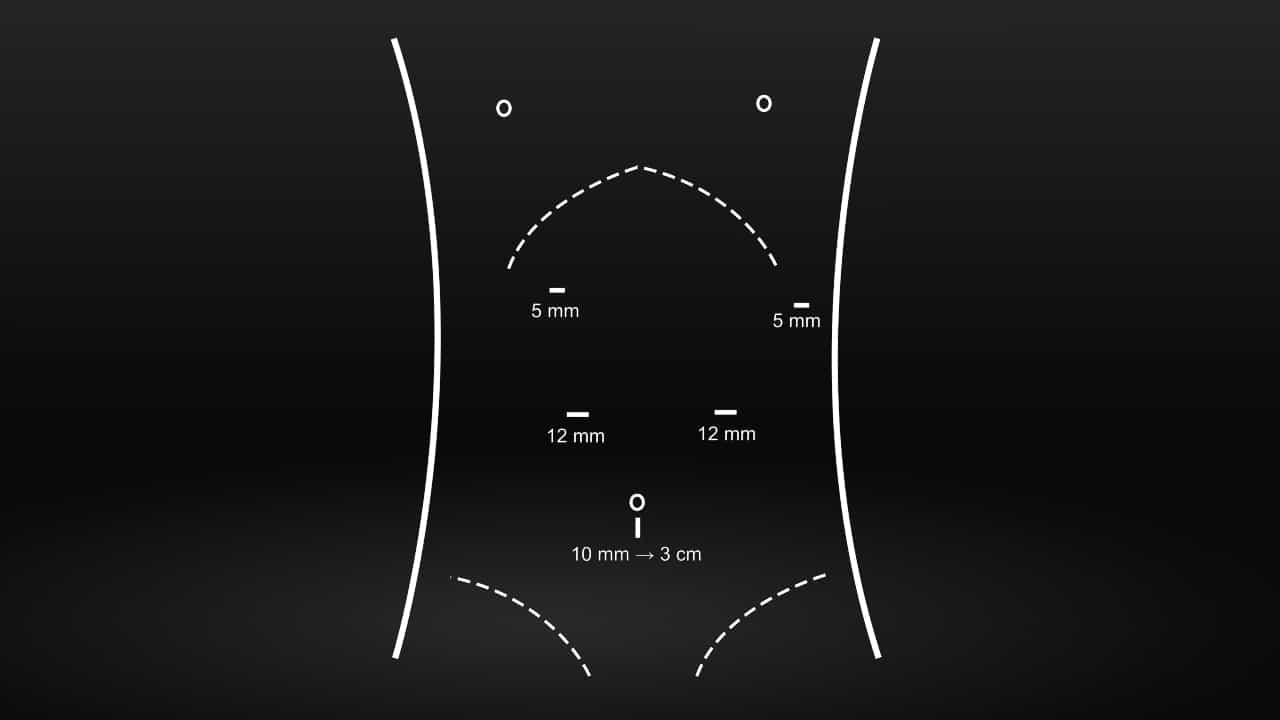
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Prognosis after splenectomy plus pericardial devascularization vs transjugular intrahepatic portosystemic shunt for
Wei-Li Qi1, Jun Wen1,2, Tian-Fu Wen1
1Department of Liver Surgery, West China Hospital, Sichuan University, Chengdu 610041, Sichuan Province, China.

Insights
Splenectomy plus pericardial devascularization (SPD) offers better survival and lower risks of liver dysfunction and liver cancer compared to transjugular intrahepatic portosystemic shunt (TIPS) for treating esophagogastric variceal bleeding in hepatitis B cirrhosis patients. Variceal rebleeding rates were similar between the two treatments.
Area of Science:
- Hepatology
- Gastroenterology
- Surgical Oncology
Background:
- Esophagogastric variceal bleeding (EGVB) is a severe complication in patients with hepatitis B virus (HBV)-related cirrhosis and portal hypertension.
- Splenectomy plus pericardial devascularization (SPD) and transjugular intrahepatic portosystemic shunt (TIPS) are established treatments for EGVB.
- Comparative data on the efficacy and safety of SPD versus TIPS for EGVB in HBV-related cirrhosis is limited.
Purpose of the Study:
- To compare the long-term prognosis of SPD versus TIPS in patients with HBV-related cirrhosis and acute EGVB.
- To evaluate overall survival, variceal rebleeding (VRB) rates, liver function, and hepatocellular carcinoma (HCC) incidence after SPD and TIPS.
- To assess treatment outcomes following endoscopic therapy failure or as secondary prophylaxis for VRB.
Main Methods:
- Retrospective cohort study of 318 patients with HBV-related cirrhosis and EGVB.
- Propensity score-matched analysis (PSM) to control for confounding factors.
- Kaplan-Meier and Cox regression analyses to compare survival, VRB, liver function, and HCC incidence.
Main Results:
- After PSM, SPD was associated with significantly better overall survival (P=0.01).
- SPD demonstrated lower rates of abnormal liver function (P<0.001) and HCC incidence (P=0.02) compared to TIPS.
- No significant difference in variceal rebleeding (VRB) rates was observed between the SPD and TIPS groups (P=0.09).
Conclusions:
- SPD is associated with superior postoperative survival and reduced risks of liver dysfunction and HCC compared to TIPS for EGVB management in HBV-related cirrhosis.
- Both SPD and TIPS are effective in preventing recurrent variceal bleeding, with no significant difference between the two procedures.
- SPD may offer a better quality of survival for patients undergoing treatment for acute EGVB or secondary prophylaxis of VRB.
Background:
Portal hypertension combined with esophagogastric variceal bleeding (EGVB) is a serious complication in patients with hepatitis B virus (HBV)-related cirrhosis in China. Splenectomy plus pericardial devascularization (SPD) and transjugular intrahepatic portosystemic shunt (TIPS) are effective treatments for EGVB. However, a comparison of the effectiveness and safety of those methods is lacking.
Aim:
To compare the prognosis after SPD vs TIPS for acute EGVB after failure of endoscopic therapy or secondary prophylaxis of variceal rebleeding (VRB) in patients with HBV-related cirrhosis combined with portal hypertension.
Methods:
This retrospective cohort study included 318 patients with HBV-related cirrhosis and EGVB who underwent SPD or TIPS at West China Hospital of Sichuan University during 2009-2013. Propensity score-matched analysis (PSM), the Kaplan-Meier method, and multivariate Cox regression analysis were used to compare overall survival, VRB rate, liver function abnormality rate, and hepatocellular carcinoma (HCC) incidence between the two patient groups.
Results:
The median age was 45.0 years (n = 318; 226 (71.1%) males). During a median follow-up duration of 43.0 mo, 18 (11.1%) and 33 (21.2%) patients died in the SPD and TIPS groups, respectively. After PSM, SPD was significantly associated with better overall survival (OS) (P = 0.01), lower rates of abnormal liver function (P < 0.001), and a lower incidence of HCC (P = 0.02) than TIPS. The VRB rate did not differ significantly between the two groups (P = 0.09).
Conclusion:
Compared with TIPS, SPD is associated with higher postoperative OS rates, lower rates of abnormal liver function and HCC, and better quality of survival as acute EGVB treatment after failed endoscopic therapy or as secondary prophylaxis of VRB in patients with HBV-related cirrhosis combined with portal hypertension. There is no significant between-group difference in VRB rates.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....