Related Experiment Video
Updated: Jul 16, 2025
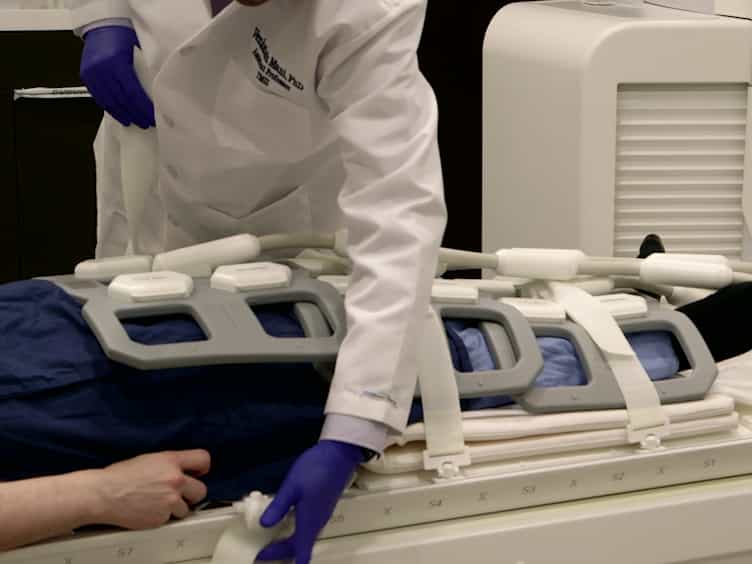
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Assessing outcomes after thrombectomy with or without iliac vein stenting for young provoked DVT patients with iliac
Hongji Pu1,2, Jumin Song3, Zhijun He4
1Department of Vascular Surgery, Shanghai Ninth People's Hospital, Shanghai Jiao Tong University School of Medicine, No. 639 Zhizaoju Rd, Shanghai, 200011, P. R. China.

Insights
Thrombectomy with iliac vein stenting showed better short-term outcomes for young deep vein thrombosis (DVT) patients with iliac vein stenosis. However, long-term efficacy and quality of life were similar to thrombectomy alone.
Area of Science:
- Vascular Surgery
- Interventional Radiology
- Cardiovascular Medicine
Background:
- Iliac vein stenosis is a significant cause of deep vein thrombosis (DVT) in young adults.
- Transiently provoked DVT in young patients presents unique management challenges.
- Assessing the role of thrombectomy with or without stenting is crucial for optimizing outcomes.
Purpose of the Study:
- To evaluate the effectiveness of thrombectomy with iliac vein stenting versus thrombectomy alone.
- To compare clinical outcomes, including symptom severity and quality of life, in young DVT patients.
- To identify the optimal interventional strategy for iliac vein stenosis in this demographic.
Main Methods:
- Retrospective analysis of a prospectively collected multicenter database.
- Inclusion of acute, transiently provoked DVT patients aged 18-45 with iliac vein stenosis.
- Comparison of outcomes between thrombectomy alone (nonstenting) and thrombectomy with stenting groups.
Main Results:
- The stenting group demonstrated significantly lower Villalta scores at 6 months (0.73 vs. 1.41, p=0.0004).
- The stenting group showed a trend towards higher VEINES-QOL scores at 6 months (89.00 vs. 87.47, p=0.2141).
- No significant differences in Villalta or VEINES-QOL scores were observed between groups at 12 months or beyond.
Conclusions:
- Thrombectomy with iliac vein stenting offers superior short-term efficacy in reducing DVT symptoms and improving quality of life.
- Long-term outcomes, including symptom burden and quality of life, are comparable between stenting and non-stenting groups up to 2 years.
- The findings suggest that while stenting provides initial benefit, its long-term advantage may diminish over time.
Background:
This study aimed to assess the outcomes of thrombectomy with/without iliac vein stenting for young and transiently provoked DVT patients with iliac vein stenosis.
Methods:
This is a retrospective analysis of a prospectively collected multicenter database. Acute, transiently provoked DVT patients between 18 and 45 years old with iliac vein stenosis were included. All patients underwent thrombectomy. Outcomes including the Villalta score, the VEINES-QOL score, and adverse events were evaluated.
Results:
The data of 522 patients were collected of whom 75 were included, 58 underwent thrombectomy alone (nonstenting group) and 17 underwent thrombectomy and stenting (stenting group). Within 6 months, the Villalta score of patients in stenting group is lower than that of patients in nonstenting group (6 mo: 0.73 ± 0.77 vs. 1.41 ± 0.56, p = .0004), and the VEINES-QOL score of stenting group is higher than that of nonstenting group (6 mo: 89.00 ± 2.94 vs. 87.47 ± 3.72, p = .2141). At the following follow-ups, the Villalta score (12 mo: 0.56 ± 0.49 vs. 0.60 ± 0.58, p = .8266) and VEINES-QOL score (12 mo: 88.36 ± 2.29 vs. 88.31 ± 3.36, p = .9604) between the two groups are similar.
Conclusion:
The stenting group had better efficacy within 6 months after intervention, while there was no significant difference in the symptom, signs, and quality of life between two groups after 6 months within a 2-year follow-up.
Trial Registration:
This study was registered in the Chinese Clinical Trial Registry (Registration Number: ChiCTR2200056073).


Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Venous Thrombosis I: Introduction