Related Experiment Video
Updated: Jul 15, 2025
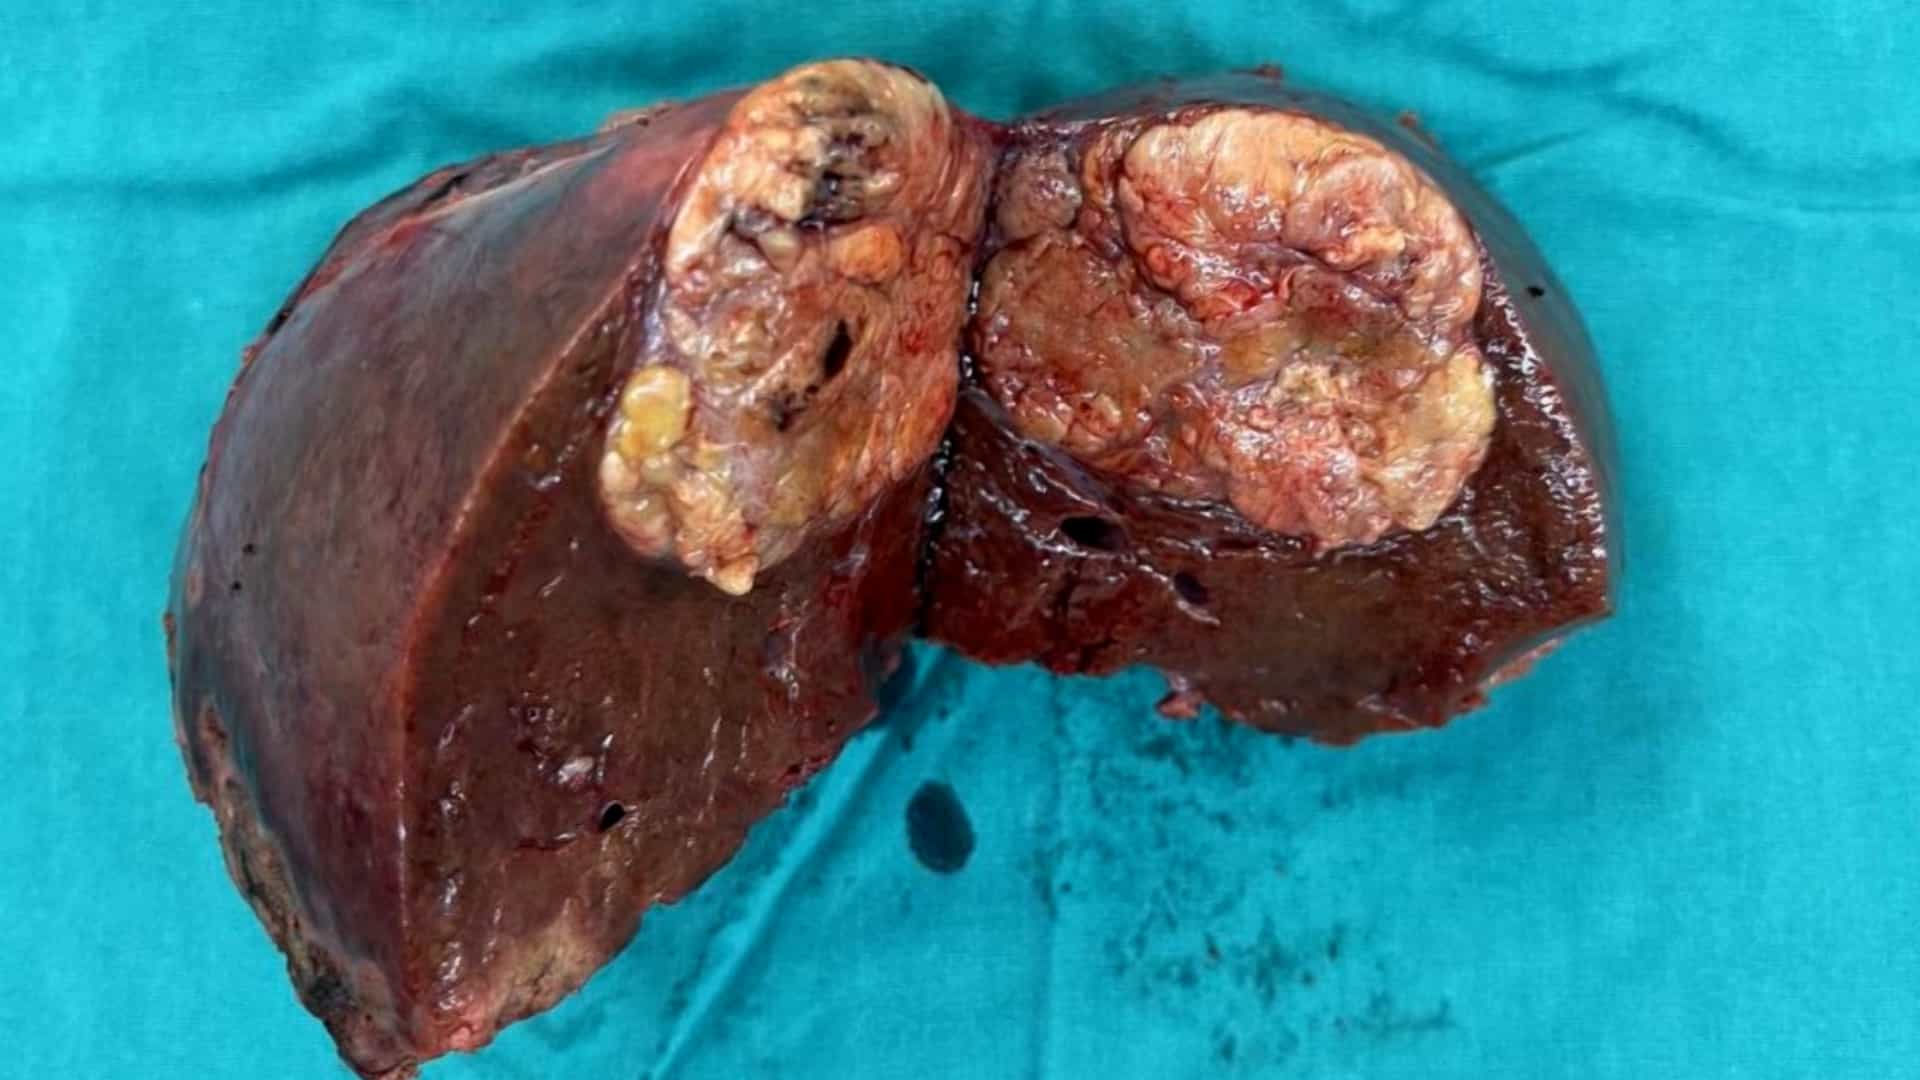
Laparoscopic Anatomical Liver Segment VII Resection with Liver Parenchymal Transection Following a Priority Approach
Published on: May 23, 2025
Liver transplantation access and outcomes: Impact of variations in liver-specific specialty care
Yutaka Endo1, Kazunari Sasaki2, Zorays Moazzam1
1Department of Surgery, The Ohio State University Wexner Medical Center and James Comprehensive Cancer Center, Columbus, OH.

Background:
We sought to characterize the impact access to gastroenterologists/hepatologists has on liver transplantation listing, as well as time on the liver transplantation waitlist and post-transplant outcomes.
Methods:
Liver transplantation registrants aged >18 years between January 1, 2004 and December 31, 2019 were identified from the Scientific Registry of Transplant Recipients Standard Analytic Files. The liver transplantation registration ratio was defined as the ratio of liver transplant waitlist registrations in a given county per 1,000 liver-related deaths.
Results:
A total of 150,679 liver transplantation registrants were included. Access to liver transplantation centers and liver-specific specialty physicians varied markedly throughout the United States. Of note, the liver transplantation registration ratio was lower in counties with poor access to liver-specific care versus counties with adequate access (poor access 137.2, interquartile range 117.8-163.2 vs adequate access 157.6, interquartile range 127.3-192.2, P < .001). Among patients referred for liver transplantation, the cumulative incidence of waitlist mortality and post-transplant graft survival was comparable among patients with poor versus adequate access to liver-specific care (both P > .05). Among liver transplantation recipients living in areas with poor access, after controlling for recipient and donor characteristics, cold ischemic time, and model for end-stage liver disease score, the area deprivation index predicted graft survival (referent, low area deprivation index; medium area deprivation index, hazard ratio 1.52, 95% confidence interval 1.03-12.23; high area deprivation index, 1.45, 95% confidence interval 1.01-12.09, both P < .05).
Conclusion:
Poor access to liver-specific care was associated with a reduction in liver transplantation registration, and individuals residing in counties with high social deprivation had worse graft survival among patients living in counties with poor access to liver-specific care.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...