Related Experiment Video
Updated: Jul 15, 2025
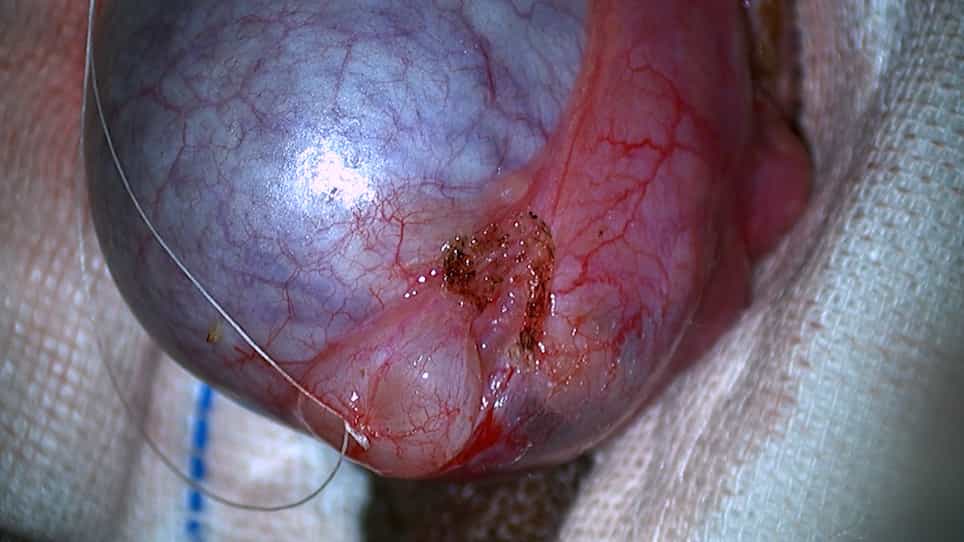

Microscopic Cyst Resection for the Treatment of Patients Diagnosed with Epididymal Cyst
Published on: March 31, 2023
A Case Report of Pseudotumor Cerebri Syndrome with a Huge Retroperitoneal Cyst
Jae-Myung Kim1, Hyunsoo Kim1, Kyung Wook Kang1
1Department of Neurology, Chonnam National University Hospital, Chonnam National University Medical School, Gwangju 61469, Republic of Korea.

Abstract:
Background: Aside from primary pseudotumor cerebri syndrome (PTCS) with an unknown etiology (i.e., idiopathic intracranial hypertension), which typically occurs in association with obesity, several conditions including cerebral venous abnormalities, drug use, and hormonal imbalance may be a secondary cause of PTCS. However, a focal space-occupying lesion outside of the brain as a cause of PTCS has rarely been reported. Case Presentation: A previously healthy 34-year-old man presented with blurred vision for three weeks. The patient had a three-month preceding history of worsening headache. On admission, he was hypertensive (160/90 mmHg) and underweight with a body mass index of 18.4 kg/m2. Fundus examination documented papilledema in both eyes. Neurological examination was unremarkable except for mild nuchal rigidity, and results of routine serologic testing were normal. Gadolinium-enhanced brain magnetic resonance imaging revealed bilateral posterior scleral flattening, suggesting intracranial hypertension. There was no other abnormal brain parenchymal lesion or meningeal enhancement. Cerebrospinal fluid (CSF) assay showed a markedly increased opening pressure (30.0 cmH2O) with normal CSF composition. A tentative diagnosis of PTCS was made based on ophthalmological, neuroradiological, and laboratory findings. During differential diagnosis, abdomen computed tomography demonstrated a huge benign cystic lesion (14.7 × 10.6 × 16.4 cm) in the right retroperitoneal space, which originated from the mesentery and resulted in hydronephrosis and renovascular hypertension due to external compression of the right kidney. Other evaluations were unremarkable. After successful surgical removal of the cyst, clinical symptoms such as headache, blurred vision, and papilledema on fundus examination were markedly improved, and blood pressure was normalized during the three-month follow-up period. Conclusions: A large retroperitoneal cyst that can increase intra-abdominal pressure could be a rare cause of PTCS. Therefore, meticulous evaluation is warranted for patients with PTCS, especially those without known risk factors.

