Related Experiment Video
Updated: Jul 15, 2025
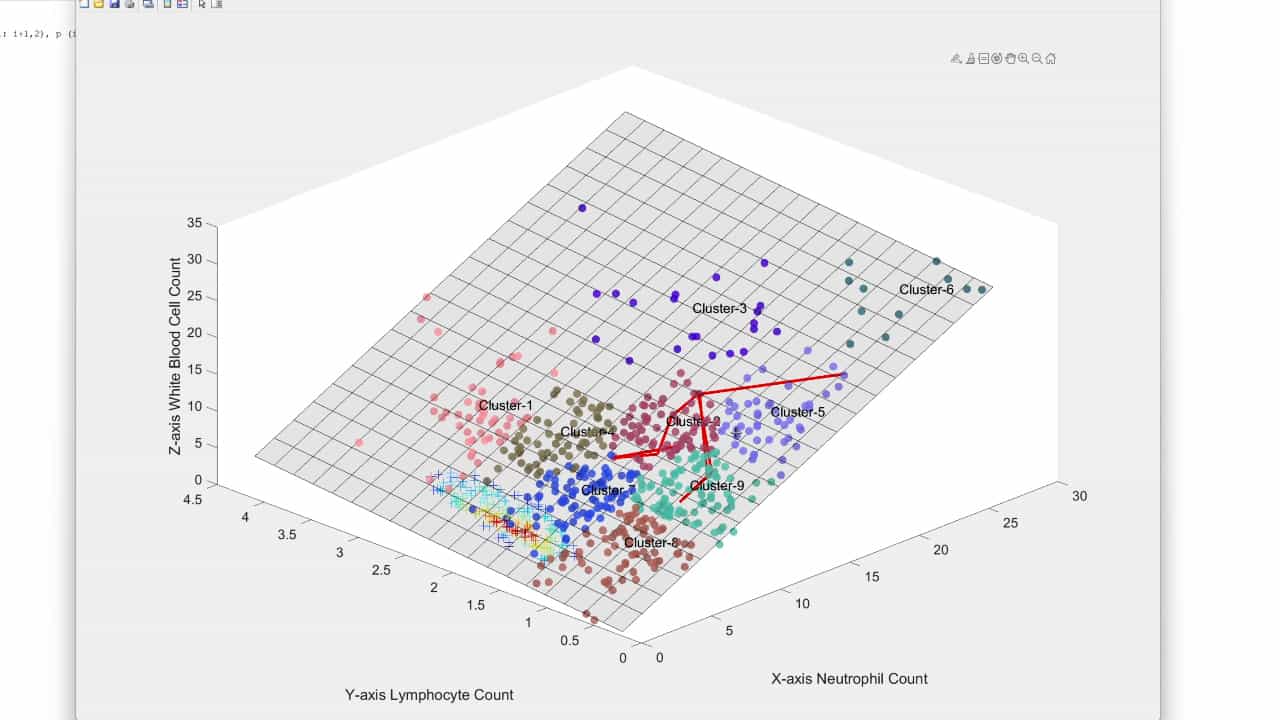
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Use of Electronic Clinical Data to Track Incidence and Mortality for SARS-CoV-2-Associated Sepsis
Claire N Shappell1,2, Michael Klompas1,3, Christina Chan1
1Department of Population Medicine, Harvard Medical School/Harvard Pilgrim Health Care Institute, Boston, Massachusetts.

Importance:
Efforts to quantify the burden of SARS-CoV-2-associated sepsis have been limited by inconsistent definitions and underrecognition of viral sepsis.
Objective:
To describe the incidence and outcomes of SARS-CoV-2-associated sepsis vs presumed bacterial sepsis using objective electronic clinical criteria.
Design, Setting, And Participants:
This retrospective cohort study included adults hospitalized at 5 Massachusetts hospitals between March 2020 and November 2022.
Exposures:
SARS-CoV-2-associated sepsis was defined as a positive SARS-CoV-2 polymerase chain reaction test and concurrent organ dysfunction (ie, oxygen support above simple nasal cannula, vasopressors, elevated lactate level, rise in creatine or bilirubin level, and/or decline in platelets). Presumed bacterial sepsis was defined by modified US Centers for Disease Control and Prevention adult sepsis event criteria (ie, blood culture order, sustained treatment with antibiotics, and organ dysfunction using identical thresholds as for SARS-CoV-2-associated sepsis).
Main Outcomes And Measures:
Trends in the quarterly incidence (ie, proportion of hospitalizations) and in-hospital mortality for SARS-CoV-2-associated and presumed bacterial sepsis were assessed using negative binomial and logistic regression models.
Results:
This study included 431 017 hospital encounters from 261 595 individuals (mean [SD] age 57.9 [19.8] years, 241 131 (55.9%) females, 286 397 [66.5%] from academic hospital site). Of these encounters, 23 276 (5.4%) were from SARS-CoV-2, 6558 (1.5%) had SARS-CoV-2-associated sepsis, and 30 604 patients (7.1%) had presumed bacterial sepsis without SARS-CoV-2 infection. Crude in-hospital mortality for SARS-CoV-2-associated sepsis declined from 490 of 1469 (33.4%) in the first quarter to 67 of 450 (14.9%) in the last (adjusted odds ratio [aOR], 0.88 [95% CI, 0.85-0.90] per quarter). Crude mortality for presumed bacterial sepsis was 4451 of 30 604 patients (14.5%) and stable across quarters (aOR, 1.00 [95% CI, 0.99-1.01]). Medical record reviews of 200 SARS-CoV-2-positive hospitalizations confirmed electronic health record (EHR)-based SARS-CoV-2-associated sepsis criteria performed well relative to sepsis-3 criteria (90.6% [95% CI, 80.7%-96.5%] sensitivity; 91.2% [95% CI, 85.1%-95.4%] specificity).
Conclusions And Relevance:
In this retrospective cohort study of hospitalized adults, SARS-CoV-2 accounted for approximately 1 in 6 cases of sepsis during the first 33 months of the COVID-19 pandemic. In-hospital mortality rates for SARS-CoV-2-associated sepsis were high but declined over time and ultimately were similar to presumed bacterial sepsis. These findings highlight the high burden of SARS-CoV-2-associated sepsis and demonstrate the utility of EHR-based algorithms to conduct surveillance for viral and bacterial sepsis.
More Related Videos
 08:48
Dynamic Monitoring of Seroconversion using a Multianalyte Immunobead Assay for Covid-19
Published on: February 16, 2022
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Related Concept Videos
 01:26
Principles of Disease Surveillance
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:27
Nursing Clinical Information System
A Nursing Clinical Information System (NCIS) is a specialized type of healthcare information system tailored to meet the unique needs of nursing practice. It incorporates the principles of nursing informatics to streamline information management and improve the quality of care delivery.
Critical attributes of NCIS include:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Methods of Documentation VII: EMR