Related Experiment Video
Updated: Jul 15, 2025
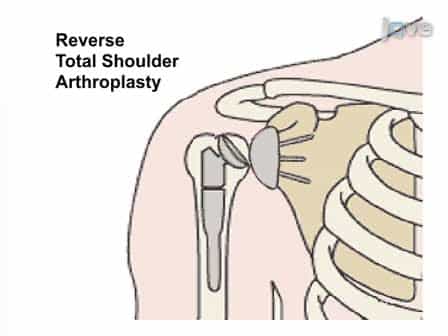

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Muscle activation patterns during active external rotation after reverse total shoulder arthroplasty: an
William P Polio1, Blake Hajek2, Tyler J Brolin1
1Department of Orthopaedic Surgery and Biomedical Engineering, University of Tennessee Health Science Center-Campbell Clinic, Memphis, TN, USA.

Background:
Preoperative teres minor insufficiency has been identified as a risk factor for poor restoration of external rotation (ER) after reverse total shoulder arthroplasty (RTSA). However, there has been little investigation regarding muscle activation patterns generating ER. This prospective study sought to determine the timing and activation levels of the shoulder girdle musculature during ER in well-functioning RTSAs with an intact teres minor using a lateralized design.
Methods:
Patients who underwent RTSA ≥1 year previously with functional ER, an American Shoulder and Elbow Surgeons (ASES) score >70, superior rotator cuff deficiency, and an intact teres minor were identified. Electrophysiological and kinematic analyses were performed during ER in the modified neutral position (arm at side with 90° of elbow flexion) and in abduction (AB) (shoulder abducted 90° with 90° of elbow flexion). Dynamometer-recorded torque and position were pattern matched to electromyography during ER. The root-mean-square and integrated electromyography (in microvolts × milliseconds with standard deviation [SD]), as well as median frequency (MF) (in hertz with SD), were calculated to determine muscle recruitment. Pair-wise t test analysis compared muscle activation (P < .05 indicated significance).
Results:
After an a priori power analysis, 16 patients were recruited. The average ASES score, visual analog scale pain score, and ASES subscore for ER in AB ("comb hair") were 87.7, 0.5, and 2.75 of 3, respectively. In AB, muscle activation began with the upper trapezius, middle trapezius, and latissimus dorsi, followed by the anterior deltoid activating to neutral. With ER beyond neutral, the teres major (9.6 μV × ms; SD, 9.2 μV × ms) initiated ER, followed by the teres minor (14.1 μV × ms; SD, 18.2 μV × ms) and posterior deltoid (11.1 μV × ms; SD, 9.3 μV × ms). MF analysis indicated equal contributions of the teres major (1.1 Hz; SD, 0.5 Hz), teres minor (1.2 Hz; SD, 0.4 Hz), and posterior deltoid (1.1 Hz; SD, 0.4 Hz) in ER beyond neutral. In the modified neutral position, the upper trapezius and middle trapezius were not recruited to the same level as in AB. For ER beyond neutral, the teres major (9.5 μV × ms [SD, 9 μV × ms]; MF, 1.1 Hz [SD, 0.5 Hz]), teres minor (11.4 μV × ms [SD, 15.1 μV × ms]; MF, 1.1 Hz [SD, 0.5 Hz]), and posterior deltoid (8.5 μV × ms [SD, 8 μV × ms]; MF, 1.2 Hz [SD, 0.3 Hz]) were activated in similar sequence and intensity as AB. No differences in muscle activation duration or intensity were noted among the teres major, teres minor, and posterior deltoid (P > .05).
Conclusion:
Active ER after RTSA is complex and is not governed by a single muscle-tendon unit. This study establishes a sequence, duration, and intensity of muscle activation for ER in well-functioning RTSAs. In both tested positions, the teres major, teres minor, and posterior deltoid function equally and sequentially to power ER.

Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:24
Muscle Coordination and Action
Agonists
Agonist muscles, often called prime movers, are the primary muscles responsible for producing a specific movement....