Related Experiment Video
Updated: Jul 15, 2025
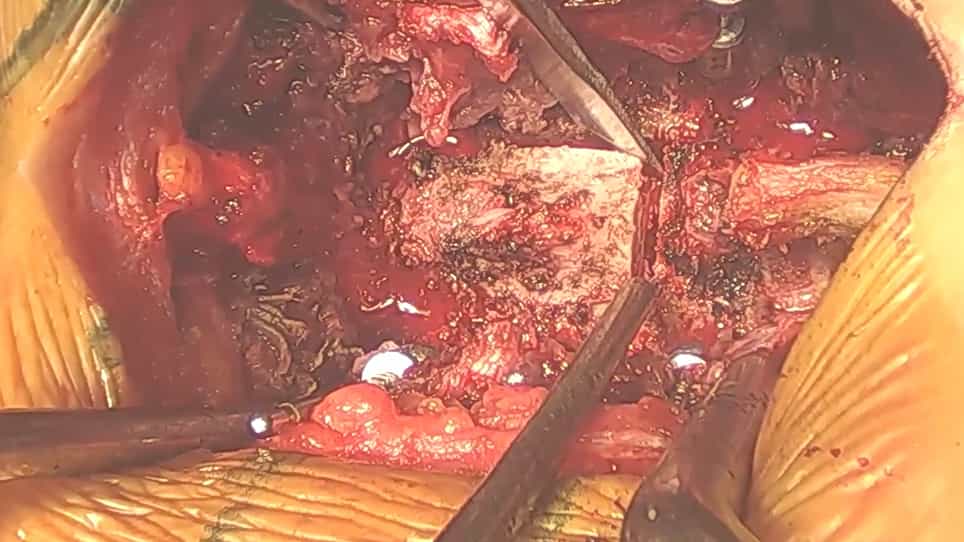

Laminectomy for the Removal of Thoracic Ossification of the Ligamentum Flavum TOLF Using Ultrasonic and Conventional Osteotomes
Published on: April 21, 2023
Channel-assisted cervical key hole technology combined with ultrasonic bone osteotome versus posterior percutaneous
Xiao Sun1,2, Chuanen Wang3, Qingquan Kong4
1Department of Orthopedics, West China Hospital, Sichuan University, Chengdu, Sichuan, China.

Purpose:
The search for more effective and safe treatment methods for cervical spondylotic radiculopathy (CSR) has led to the rapid development and increasing popularity of minimally invasive posterior cervical foraminotomy (MI-PCF). This study aims to compare two important approaches for MI-PCF surgery: the channel-assisted cervical key hole technology combined with ultrasonic bone osteotome (CKH-UBO) and posterior percutaneous endoscopic cervical foraminotomy (PPECF).
Methods:
Data from patients treated with single-level CKH-UBO (n = 35) or PPECF (n = 40) were analyzed. Clinical outcomes, including visual analogue scale (VAS) scores for neck and arm pain, Neck Disability Index (NDI), and modified Macnab criteria, were assessed preoperatively, as well as at three days, three months, and one year postoperatively.
Results:
The percentages of patients with excellent and good outcomes were 97.14% and 92.5%, respectively. The average surgical time in the CKH-UBO group was significantly shorter than in the PPECF group (p < 0.001), while the average incision length in the PPECF group was significantly smaller than in the CKH-UBO group. There were no significant differences between the two groups in terms of blood loss, hospital stay, and clinical outcomes at three days, three months, and 12 months postoperatively.
Conclusion:
CKH-UBO can achieve the same surgical outcomes as PPECF for the treatment of CSR. However, CKH-UBO saves more time but requires patients to undergo larger incisions.