Related Experiment Video
Updated: Jul 15, 2025


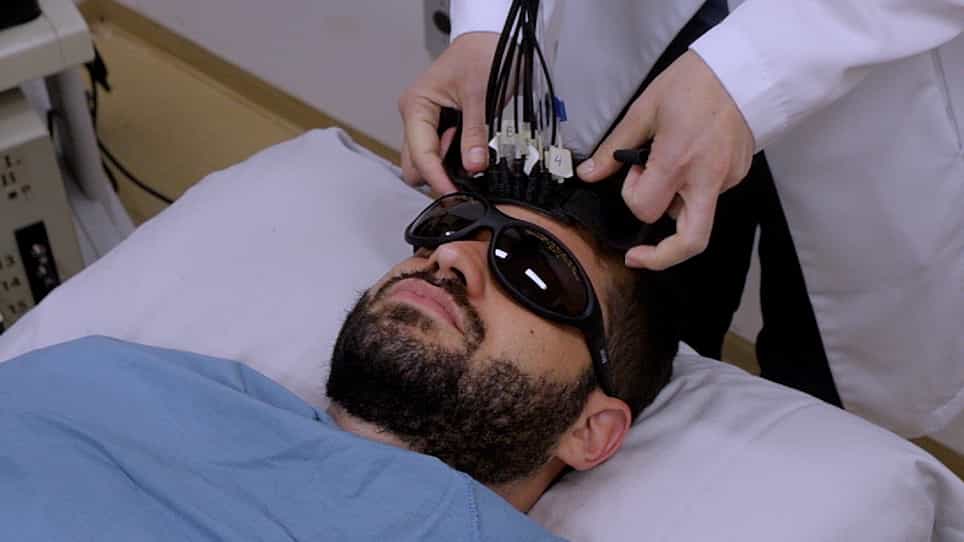
Assessing Cerebral Autoregulation via Oscillatory Lower Body Negative Pressure and Projection Pursuit Regression
Published on: December 10, 2014
Continuous Monitoring of Cerebral Autoregulation in Adults Supported by Extracorporeal Membrane Oxygenation
Lucy Q Zhang1, Henry Chang1, Andrew Kalra1
1Johns Hopkins School of Medicine: The Johns Hopkins University School of Medicine.

Background:
Impaired cerebral autoregulation (CA) is one of several proposed mechanisms of acute brain injury in patients supported by extracorporeal membrane oxygenation (ECMO). The primary aim of this study was to determine the feasibility of continuous CA monitoring in adult ECMO patients. Our secondary aims were to describe changes in cerebral oximetry index (COx) and other metrics of CA over time and in relation to functional neurologic outcomes.
Methods:
This is a single-center prospective observational study. We measured Cox, a surrogate measurement of cerebral blood flow, measured by near-infrared spectroscopy, which is an index of CA derived from the moving correlation between mean arterial pressure and slow waves of regional cerebral oxygen saturation. A COx value that approaches 1 indicates impaired CA. Using COx, we determined the optimal MAP (MAPOPT), lower and upper limits of autoregulation for individual patients. These measurements were examined in relation to modified Rankin Scale (mRS) scores.
Results:
Fifteen patients (median age=57 years [IQR=47-69]) with 150 autoregulation measurements were included for analysis. Eleven were on veno-arterial ECMO and 4 on veno-venous. Mean COx was higher on post-cannulation day 1 than on day 2 (0.2 vs 0.09, p<0.01), indicating improved CA over time. COx was higher in VA-ECMO patients than in VV-ECMO (0.12 vs 0.06, p=0.04). Median MAPOPT for entire cohort was highly variable, ranging 55-110 mmHg. Patients with mRS 0-3 (good outcome) at 3 and 6 months spent less time outside of MAPOPT compared to patients with mRS 4-6 (poor outcome) (74% vs 82%, p=0.01). The percentage of time when observed MAP was outside the limits of autoregulation was higher on post-cannulation day 1 than on day 2 (18.2% vs 3.3%, p<0.01).
Conclusions:
In ECMO patients, it is feasible to monitor CA continuously at the bedside. CA improved over time, most significantly between post-cannulation days 1 and 2. CA was more impaired in VA-ECMO than VV-ECMO. Spending less time outside of MAPOPT may be associated with achieving a good neurologic outcome.

Related Concept Videos
 01:17
Autoregulation of Blood Flow
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation....
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...