Related Experiment Video
Updated: Jul 15, 2025
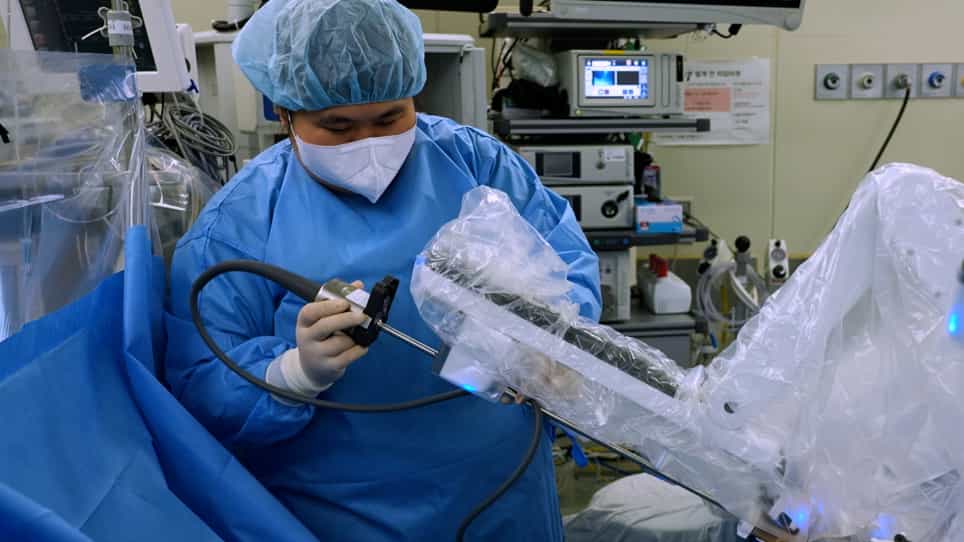
Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Waiting time for kidney transplantation based on calculated panel reactive antibodies: experience of a southern
Lisianara Acosta Ramos1, Tiago Schiavo2, Juliana Montagner2
1Universidade de Ciências da Saúde de Porto Alegre, Porto Alegre, RS, Brazil.

Insights
Patients with lower antibody levels (below 85% panel reactive antibodies) receive kidney transplants faster. Graft survival is similar, but death risk is lower in non-sensitized recipients after kidney transplant.
Area of Science:
- Nephrology
- Transplant Immunology
- Clinical Outcomes Research
Background:
- Kidney transplantation is a vital treatment for end-stage renal disease.
- Candidate's panel reactive antibodies (cPRA) significantly influence transplant eligibility and outcomes.
- Understanding cPRA impact on waiting lists is crucial for optimizing patient management.
Purpose of the Study:
- To analyze kidney transplant waiting list dynamics based on cPRA.
- To evaluate transplant outcomes in relation to cPRA levels.
- To identify factors affecting graft survival and patient mortality post-transplantation.
Main Methods:
- Retrospective analysis of 1640 patients on the kidney transplant waiting list (2015-2019).
- Fine and Gray's regression model used to estimate hazard ratios (HR) for transplant, graft loss, and death.
- Patients categorized by cPRA levels: 0%, 1%-49%, 50%-84%, and ≥85%.
Main Results:
- Transplantation achieved in 85.5% of patients within a median of 8 months.
- Patients with cPRA <85% had significantly higher HRs for transplantation compared to cPRA ≥85% (HRs ranging from 2.41 to 2.84).
- Graft loss HRs were similar across cPRA groups; however, the adjusted HR for death was lower in the 0% cPRA group (0.46).
Conclusions:
- Lower cPRA (<85%) is associated with a more than twofold increased likelihood of receiving a kidney transplant and shorter waiting times.
- Post-transplant graft loss rates are comparable across different cPRA strata.
- Nonsensitized recipients (0% cPRA) exhibit a reduced adjusted risk of mortality after kidney transplantation.
Introduction:
The aim of this study was to analyze the waiting list for kidney transplantation in our hospital according to candidate's panel reactive antibodies (cPRA) and its outcomes.
Methods:
One thousand six hundred forty patients who were on the waiting list between 2015 and 2019 were included. For the analysis, hazard ratios (HR) for transplant were estimated by Fine and Gray's regression model according to panel reactivity and HR for graft loss and death after transplantation.
Results:
The mean age was 45.39 ± 18.22 years. Male gender was predominant (61.2%), but the proportion decreased linearly with the increase in cPRA (p < 0.001). The distribution of patients according to panels were: 0% (n = 390), 1% - 49% (n = 517), 50% - 84% (n = 269), and ≥ 85% (n = 226). Transplantation was achieved in 85.5% of the sample within a median time of 8 months (CI 95%: 6.9 - 9.1). The estimated HRs for transplantation during the follow-up were 2.84 (95% CI: 2.51 - 3.34), 2.41(95%CI: 2.07 - 2.80), and 2.45(95%CI: 2.08 - 2.90) in the cPRA range of 0%, 1%-49%, and 50%-84%, respectively, compared to cPRA ≥ 85 (p < 0.001). After transplantation, the HR for graft loss was similar in the different cPRA groups, but the HR for death (0.46 95% CI 0.24-0.89 p = 0.022) was lower in the 0% cPRA group when adjusted for age, gender, and presence of donor specific antibodies (DSA).
Conclusion:
Patients with cPRA below 85% are more than twice as likely to receive a kidney transplantation with a shorter waiting time. The risk of graft loss after transplantation was similar in the different cPRA groups, and the adjusted risk of death was lower in nonsensitized recipients.


Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention