Bilateral gluteal reconstruction with deep inferior epigastric perforator flaps and saphenofemoral arteriovenous loops
Related Experiment Video
Updated: Aug 14, 2026
Engineered Vascularized Muscle Flap
Published on: January 11, 2016
J Reed McGraw1, Ivan A Jaimez1, Elizabeth Card1
1Division of Plastic Surgery, Department of Surgery, University of Pennsylvania, Philadelphia, Pennsylvania, USA.

The use of liquid silicone injections for soft tissue augmentation harbors numerous risks and is not approved by the FDA. Still, such injections are frequently performed by unlicensed providers, often in the gluteal region, and can lead to infection, soft-tissue breakdown, scarring, and disfigurement. The purpose of this case report was to demonstrate the use of immediate, abdominally based free flaps for reconstruction in a patient with bilateral total gluteal defects and limited inflow options in the setting of remote silicone injections. The patient is a 45-year-old female who developed chronically infected injected silicone in the bilateral buttocks leading to draining abscesses and soft tissue breakdown. The patient required radical debridement and excision of the bilateral buttocks to remove all foreign material. After intermediate skin grafting of the residual wounds, the patient then was deemed a candidate for bilateral free flap reconstruction of the buttocks. On exploration of the bilateral defects, both 20 cm × 10 cm in size, the gluteal vessels were non-usable, and preoperative CTA additionally had revealed no suitable posteriorly based perforators. Therefore, bilateral arteriovenous (AV) loops, measuring 30 cm in length, were then constructed utilizing the greater saphenous veins anastomosed to the femoral arteries which were then tunneled to the defect. The soft tissue defects were concurrently reconstructed with bilateral deep inferior epigastric perforator (DIEP) flaps measuring 16 cm × 12 cm. The postoperative course was complicated by small seromas in each groin requiring drain placement by interventional radiology on postoperative day 16. Otherwise, the patient's buttocks healed well, and functionally, the patient had regained the ability to sit and was satisfied with the aesthetic appearance of the reconstruction as of last follow-up at 10 months. Abdominally based free flap reconstruction with AV loops, in this case, provided for successful reconstruction of otherwise challenging soft-tissue defects with limited inflow options.
The use of liquid silicone injections for soft tissue augmentation harbors numerous risks and is not approved by the FDA. Still, such injections are frequently performed by unlicensed providers, often in the gluteal region, and can lead to infection, soft-tissue breakdown, scarring, and disfigurement. The purpose of this case report was to demonstrate the use of immediate, abdominally based free flaps for reconstruction in a patient with bilateral total gluteal defects and limited inflow options in the setting of remote silicone injections. The patient is a 45-year-old female who developed chronically infected injected silicone in the bilateral buttocks leading to draining abscesses and soft tissue breakdown. The patient required radical debridement and excision of the bilateral buttocks to remove all foreign material. After intermediate skin grafting of the residual wounds, the patient then was deemed a candidate for bilateral free flap reconstruction of the buttocks. On exploration of the bilateral defects, both 20 cm × 10 cm in size, the gluteal vessels were non-usable, and preoperative CTA additionally had revealed no suitable posteriorly based perforators. Therefore, bilateral arteriovenous (AV) loops, measuring 30 cm in length, were then constructed utilizing the greater saphenous veins anastomosed to the femoral arteries which were then tunneled to the defect. The soft tissue defects were concurrently reconstructed with bilateral deep inferior epigastric perforator (DIEP) flaps measuring 16 cm × 12 cm. The postoperative course was complicated by small seromas in each groin requiring drain placement by interventional radiology on postoperative day 16. Otherwise, the patient's buttocks healed well, and functionally, the patient had regained the ability to sit and was satisfied with the aesthetic appearance of the reconstruction as of last follow-up at 10 months. Abdominally based free flap reconstruction with AV loops, in this case, provided for successful reconstruction of otherwise challenging soft-tissue defects with limited inflow options.
More Related Videos
 00:09
Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
 05:34
A Reliable Porcine Fascio-Cutaneous Flap Model for Vascularized Composite Allografts Bioengineering Studies
Published on: March 31, 2022
Related Concept Videos
 01:23
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...
 01:15
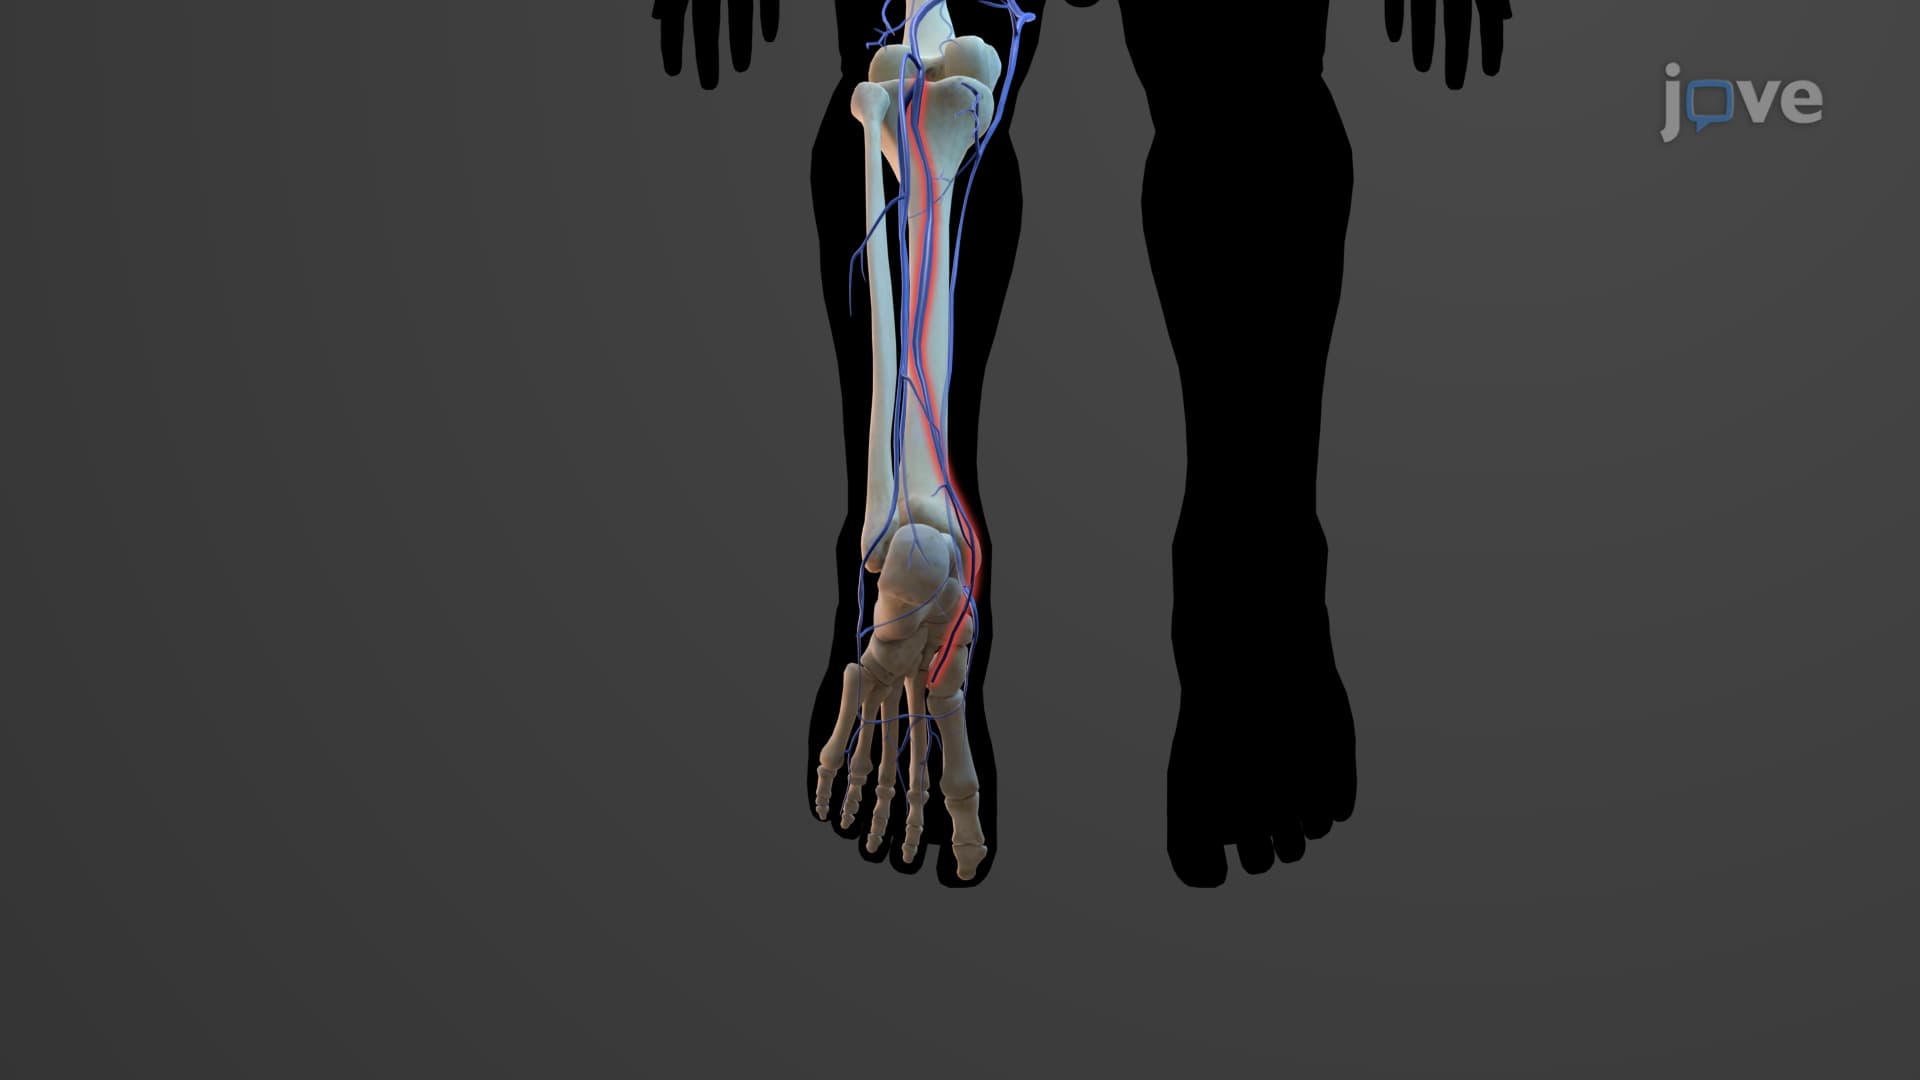
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...