Related Experiment Video
Updated: Jul 14, 2025
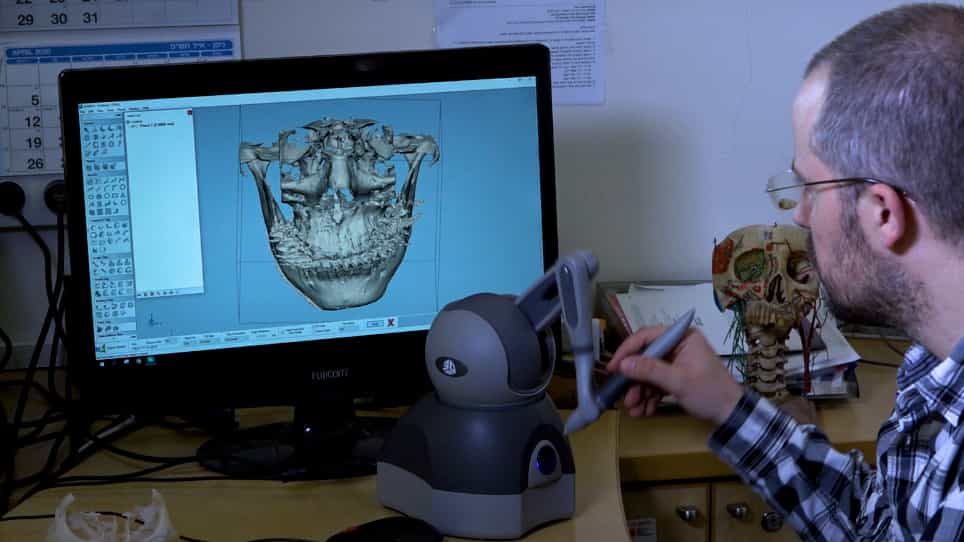

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Changes of Temporomandibular Joint Morphology and Symptoms in Class II Malocclusion Patients With Bilateral Sagittal
Yang-Xin Luo1, Zheng-Hao Chen, Jian-Ning Wang
1Guangdong Provincial Key Laboratory of Stomatology, Department of Oral and Maxillofacial Surgery, Hospital of Stomatology, Guanghua School of Stomatology, Sun Yat-sen University, Guangzhou, Guangdong Province, P.R. China.

Abstract:
This study included 46 patients with class II malocclusion ranging in age from 19 to 39 years old treated with bilateral sagittal split ramous osteotomy (BSSRO). Left and right temporomandibular joints (TMJs) of each subject were evaluated independently with cone-beam computed tomography (CBCT) before operation (T1), 1 week after operation (T2), and 1 year after operation (T3) and assessed the effects of orthognathic surgery (OGS) on the temporomandibular joint disease (TMD) symptoms. Temporomandibular joint morphology evaluation included condylar volume, condylar area, cortical bone thickness, depth of the mandibular fossa, fossa thickness, joint nodule angle, joint space, and condyle-fossa relationship, which were calculated by using the Mimics software and 3-matic software. Data were statistically analyzed with SPSS software (P <0.05 means statistically significant). In our study, bilateral TMJs have no difference in T3. Bilateral sagittal split ramous osteotomy had no significant effect on the articular fossa. The condyle volume and surface area decreased from T1 to T3, but the cortical thickness of the bone did not change significantly. More anterior condyle positions in T1 and more posterior in T3.21 patients had at least 1 sign or symptom of TMD in T1 and 27 patients in T3. Four patients who were asymptomatic in T1 developed pain after surgery, 10 developed noises, 12 showed limited mouth opening, and 8 had abnormal opening patterns. It is concluded that more condylar posterior position after BSSRO and the reduction of condyle may be related to the enlargement of anterior space. The number of patients with joint symptoms increased postoperative, and the impact of BSSRO on TMD may be negative.


