Related Experiment Video
Updated: Jul 14, 2025
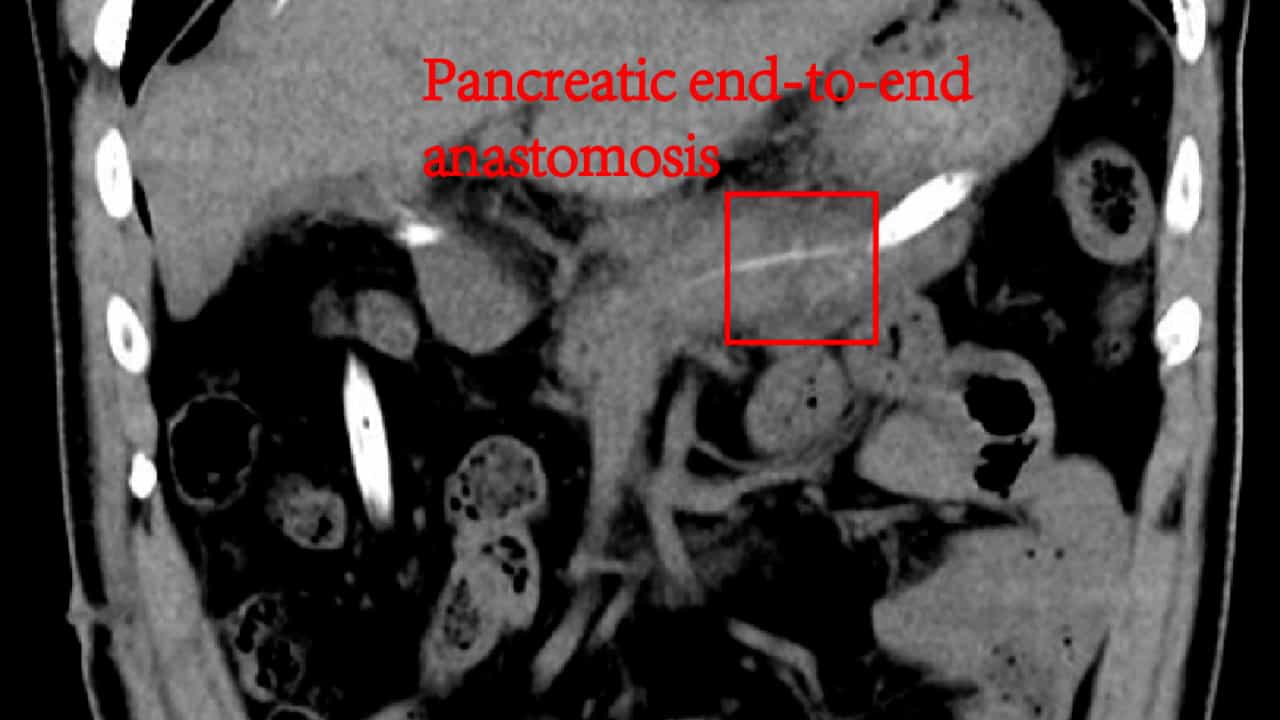

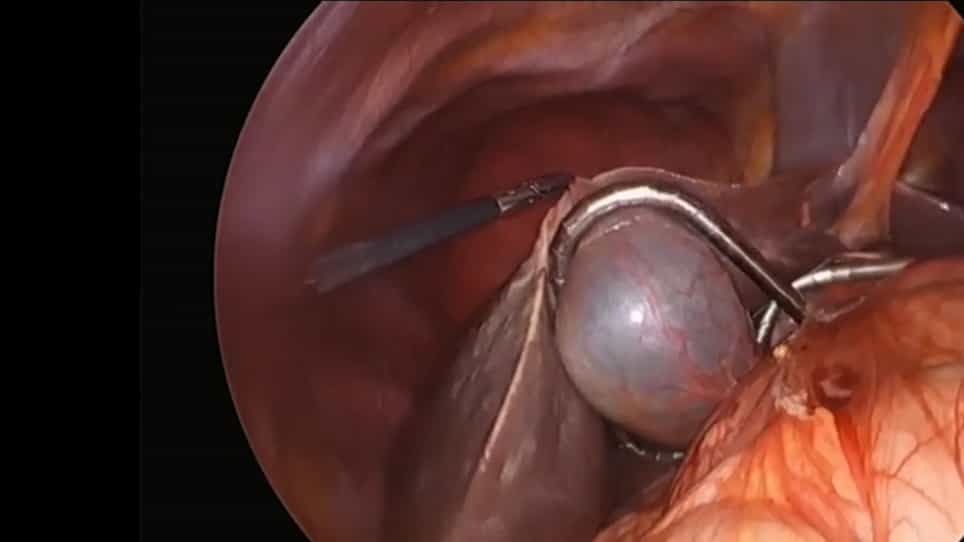
Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Pancreatectomy for intraductal papillary mucinous neoplasm: has anything changed in North America?
Catherine H Davis1, Ankur P Choubey2, Russell C Langan3
1Division of Surgical Oncology, Rutgers Cancer Institute of New Jersey, New Brunswick, NJ, USA; Rutgers Robert Wood Johnson Medical School, New Brunswick, NJ, USA.

Background:
Multiple guidelines on the management of intraductal papillary mucinous neoplasm (IPMN) have been published over the past decade. However, practice data are lacking. This study aims to determine whether pancreatectomy procedures, IPMN pathology, or outcomes have changed.
Methods:
ACS-NSQIP Procedure Targeted Pancreatectomy database was queried for patients with IPMN from 2014 to 2019. Cases were stratified by pathology, tumor stage/cyst size and procedure. Pancreatectomies for IPMN by year, 30-day morbidity, and clinically relevant postoperative pancreatic fistula (CR-POPF) were quantified. Mann-Kendall trend tests were performed to assess surgical trends and associated outcomes over time.
Results:
3912 patients underwent pancreatectomy for IPMN. 21% demonstrated malignancy and 79% were benign. Morbidity and mortality occurred in 29.7% and 1.5% of cases, respectively. Over time, no change was observed in use of pancreatectomy for IPMN (10%) or in benign/malignant pathology, or cyst size. Robotic approach increased from 9.1% to 16.5% with decreases in laparoscopic (19.5%-15.0%) and open interventions (71.5%-68.1%, p = 0.016). No change was observed over time in morbidity or mortality; however, rates of CR-POPF decreased (18.8%-13.8%, p < 0.001).
Conclusions:
Practice patterns in treatment of IPMN have not changed significantly in North America. More patients are undergoing robotic pancreatectomy, and postoperative pancreatic fistula rates are improving.