Related Experiment Video
Updated: Jul 14, 2025
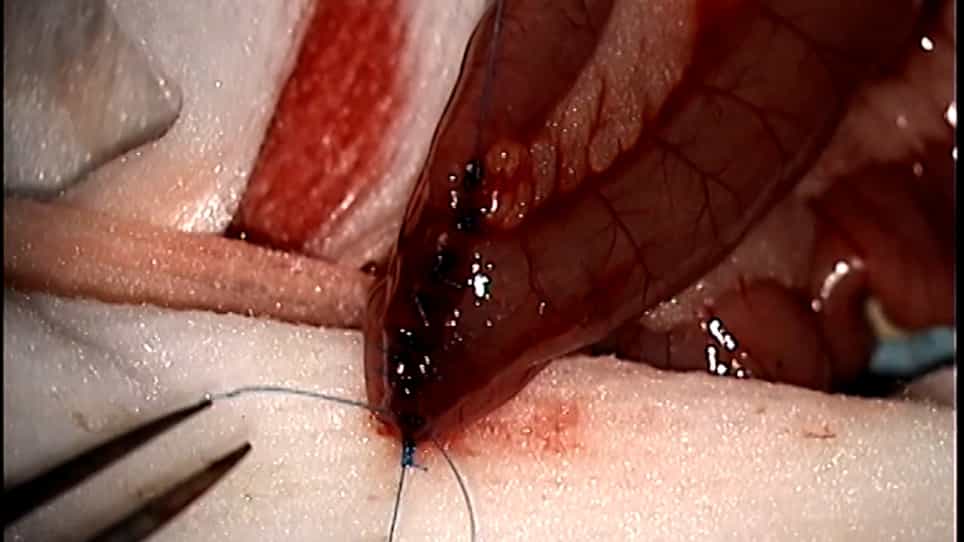

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Perforated pre-pyloric ulcer in the gastric remnant over a decade after Roux-en-Y gastric bypass: A case report
Bianca Marquez1, Emmanuel Luciano1, Ryan Cohen2
1Department of Surgery, Central Michigan University College of Medicine, United States of America.

Introduction And Importance:
Roux-en-Y gastric bypass (RYGB) is one of the two most common weight loss surgeries. Surgical emergencies after gastric bypass can be complicated by devastating events that are often difficult to diagnose and manage. Perforated ulcers are a very rare complication after a RYGB.
Case Presentation:
In this report, the diagnosis and surgical management of a 59-year-old immunosuppressed male patient who presented with late perforation of a pre-pyloric ulcer in the gastric remnant after RYGB is presented. The perforation was repaired transversely in a running horizontal mattress fashion and patched with a piece of well-vascularized omentum.
Clinical Discussion:
This case illustrates the potential for gastric remnant ulceration, even a decade after RYGB. A high degree of suspicion for the diagnosis of perforated remnant stomach is required, especially in the absence of pneumoperitoneum and free fluid. Patient-specific factors, such as immunosuppression in this case, may blunt normal physiologic response.
Conclusion:
Considering the location of the ulcer in the pre-pyloric area, we caution that the typical paradigm of marginal ulceration of the gastro-jejunal anastomosis does not always apply when evaluating gastric complications after RYGB.


Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...