Related Experiment Video
Updated: Jul 14, 2025


Lumped-Parameter and Finite Element Modeling of Heart Failure with Preserved Ejection Fraction
Published on: February 13, 2021
Isovolumic Contraction Velocity in Heart Failure With Reduced Ejection Fraction and Effect of Sacubitril/Valsartan:
Alaa Mabrouk Salem Omar1, Sean Murphy2, G Michael Felker3
1Department of Cardiovascular Medicine, Mount Sinai Morningside, New York, NY.

Insights
Mitral annular isovolumic contraction velocity (ICV) improved after sacubitril/valsartan treatment in heart failure with reduced ejection fraction (HFrEF). This enhanced systolic function assessment predicts cardiac remodeling and treatment response.
Area of Science:
- Cardiology
- Echocardiography
- Heart Failure Management
Background:
- Isovolumic contraction velocity (ICV) may reflect load-independent systolic function.
- Combining ICV with ejection fraction (EF) can enhance the assessment of left ventricular (LV) contractility.
Purpose of the Study:
- To evaluate the change in tissue Doppler-derived mitral annular ICV after initiating sacubitril/valsartan therapy.
- To assess the predictive value of ICV for cardiac remodeling and treatment response in patients with HFrEF.
Main Methods:
- Echocardiograms were performed at baseline, 6, and 12 months in 651 HFrEF participants treated with sacubitril/valsartan.
- Baseline ICV and LV ejection fraction (LVEF) were used to classify patients and predict outcomes.
Main Results:
- Median ICV significantly increased after sacubitril/valsartan therapy (P=0.005).
- Baseline ICV/EF classification identified distinct groups with varying remodeling, health status, and biomarker profiles.
- Treatment led to significant shifts towards better ICV/EF profiles, with a doubling of high ICV/high EF and a substantial reduction in low ICV/low EF.
Conclusions:
- In HFrEF, ICV provides valuable insights into systolic function and independently predicts reverse cardiac remodeling post-sacubitril/valsartan treatment.
- Changes in ICV can be utilized to monitor and assess patient responses to therapy.
Objectives:
To assess tissue Doppler-derived mitral annular isovolumic contraction velocity (ICV) after starting sacubitril/valsartan (sac/val) for the treatment of heart failure with reduced ejection fraction (HFrEF) and left ventricular [LV] EF < 40%).
Background:
ICV may inform load-independent systolic function; combining ICV and LVEF may improve assessment of LV contractility.
Methods:
Among 651 participants with HFrEF treated with sac/val, echocardiograms were performed at baseline, 6 and 12 months. Pretreatment median ICVs and LVEFs were used for classification to predict LV reverse remodeling, health status using the Kansas City Cardiomyopathy Questionnaire, and biomarker concentrations.
Results:
The mean age was 64.6 ± 12.4 years, and 28% were women, baseline LVEF: 28.9% ± 6.9%. Compared to baseline, median ICV increased post sac/val therapy (4.6 [3.5, 6.1] vs 4.9 [3.6, 6.4]; P = 0.005). ICV added value to separate and combined models of biomarkers and clinical and echocardiographic variables for prediction of post-therapy EF recovery. Classification using baseline ICV/EF yielded relatively equal numbers in 4 groups based on low/high ICV or LVEF. Most deleterious results for remodeling, health status and biomarkers were found in patients with low ICV/low EF, whereas patients with high ICV/high EF had the best profiles; other groups were intermediate. Significant shifts toward better ICV/EF profiles were noted post sac/val treatment compared to baseline, with doubling of high ICV/high EF (241 [60%] vs 123 [31%]) and 78% reduction of low ICV/low EF (28 [7%] vs 125 [32%]).
Conclusions:
In HFrEF, ICV adds to the profiling of systolic function and represents an independent predictor of reverse cardiac remodeling after treatment with sac/val. ICV changes may be used for assessment of treatment responses.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Related Concept Videos
 01:30
Heart Failure V: Medical Management
 01:29
Heart Failure II: Pathophysiology
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
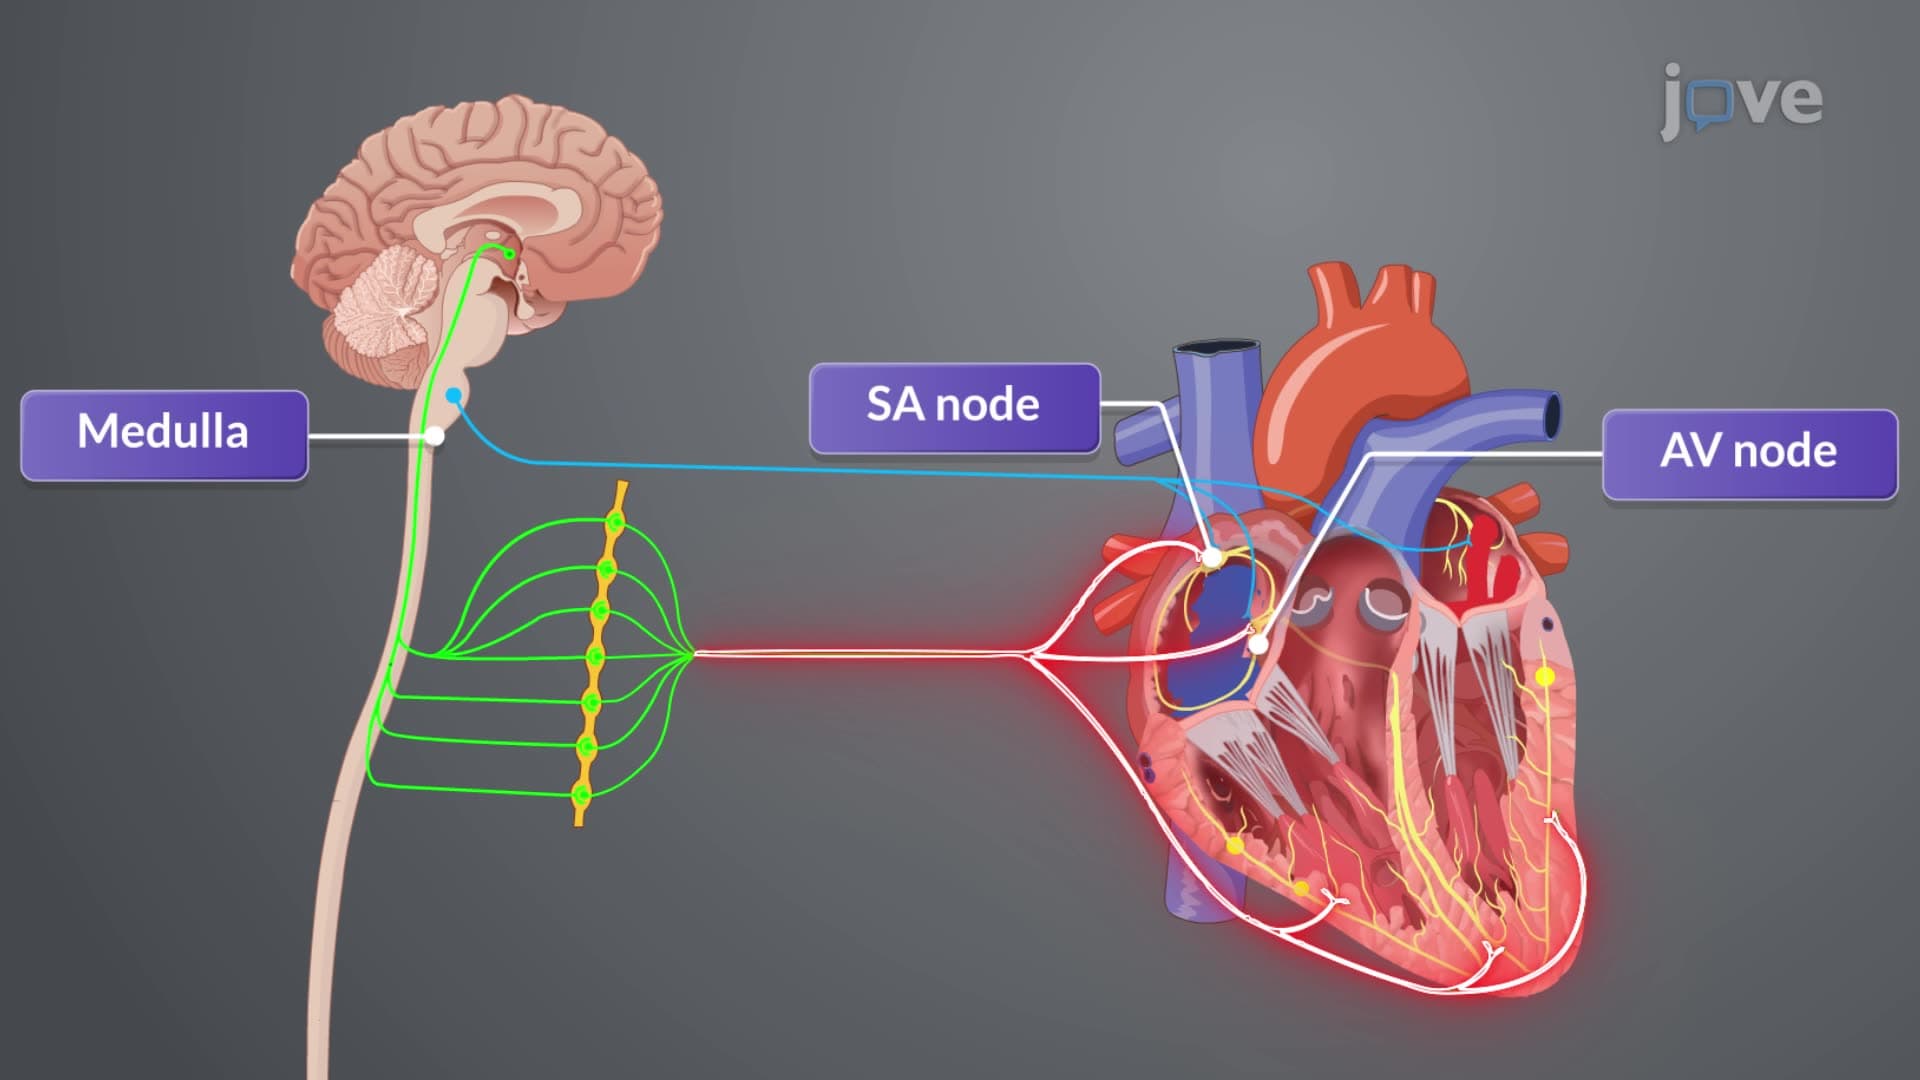
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:22
Heart Failure Drugs: β-Blockers