Related Experiment Video
Updated: Jul 13, 2025
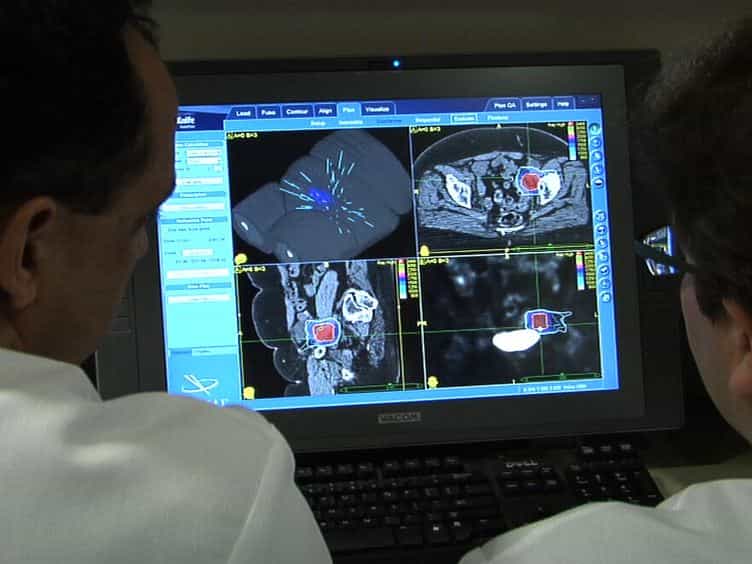
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Risk of thrombosis and bleeding in gynecologic cancer surgery: systematic review and meta-analysis
Lauri I Lavikainen1, Gordon H Guyatt2, Anna L Luomaranta3
1Faculty of Medicine, University of Helsinki, Helsinki, Finland.

Objective:
This study aimed to provide procedure-specific estimates of the risk of symptomatic venous thromboembolism and major bleeding in the absence of thromboprophylaxis, following gynecologic cancer surgery.
Data Sources:
We conducted comprehensive searches on Embase, MEDLINE, Web of Science, and Google Scholar for observational studies. We also reviewed reference lists of eligible studies and review articles. We performed separate searches for randomized trials addressing effects of thromboprophylaxis and conducted a web-based survey on thromboprophylaxis practice.
Study Eligibility Criteria:
Observational studies enrolling ≥50 adult patients undergoing gynecologic cancer surgery procedures reporting absolute incidence for at least 1 of the following were included: symptomatic pulmonary embolism, symptomatic deep vein thrombosis, symptomatic venous thromboembolism, bleeding requiring reintervention (including reexploration and angioembolization), bleeding leading to transfusion, or postoperative hemoglobin <70 g/L.
Methods:
Two reviewers independently assessed eligibility, performed data extraction, and evaluated risk of bias of eligible articles. We adjusted the reported estimates for thromboprophylaxis and length of follow-up and used the median value from studies to determine cumulative incidence at 4 weeks postsurgery stratified by patient venous thromboembolism risk factors. The GRADE approach was applied to rate evidence certainty.
Results:
We included 188 studies (398,167 patients) reporting on 37 gynecologic cancer surgery procedures. The evidence certainty was generally low to very low. Median symptomatic venous thromboembolism risk (in the absence of prophylaxis) was <1% in 13 of 37 (35%) procedures, 1% to 2% in 11 of 37 (30%), and >2.0% in 13 of 37 (35%). The risks of venous thromboembolism varied from 0.1% in low venous thromboembolism risk patients undergoing cervical conization to 33.5% in high venous thromboembolism risk patients undergoing pelvic exenteration. Estimates of bleeding requiring reintervention varied from <0.1% to 1.3%. Median risks of bleeding requiring reintervention were <1% in 22 of 29 (76%) and 1% to 2% in 7 of 29 (24%) procedures.
Conclusion:
Venous thromboembolism reduction with thromboprophylaxis likely outweighs the increase in bleeding requiring reintervention in many gynecologic cancer procedures (eg, open surgery for ovarian cancer and pelvic exenteration). In some procedures (eg, laparoscopic total hysterectomy without lymphadenectomy), thromboembolism and bleeding risks are similar, and decisions depend on individual risk prediction and values and preferences regarding venous thromboembolism and bleeding.
More Related Videos
 09:48
An Orthotopic Endometrial Cancer Model with Retroperitoneal Lymphadenopathy Made From In Vivo Propagated and Cultured VX2 Cells
Published on: September 12, 2019
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:24
Disorders of the Female Reproductive System
 01:30
Venous Thrombosis IV: Nursing Management
 01:30
Venous Thrombosis I: Introduction
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...