Related Experiment Video
Updated: Jul 13, 2025

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Diaphragmatic muscle function in term and preterm infants
Sotirios Fouzas1, Aggeliki Vervenioti1, Asimina Tsintoni1
1Neonatal Intensive Care Unit, Department of Paediatrics, University of Patras School of Medicine, Rio, Patras, 26500, Greece.

Insights
Preterm infants exhibit reduced diaphragmatic strength and endurance, increasing fatigue risk. Bronchopulmonary dysplasia (BPD) can further impair diaphragmatic function in very preterm infants.
Area of Science:
- Neonatal Physiology
- Respiratory Medicine
- Pediatric Pulmonology
Background:
- The diaphragm's capacity to manage the work of breathing is limited in preterm infants.
- Key measures of diaphragmatic function, maximum transdiaphragmatic pressure (Pdimax) and pressure-time index (PTIdi), are not well-studied in infants.
Purpose of the Study:
- To determine factors influencing diaphragmatic function in term and preterm infants.
- To compare diaphragmatic strength and endurance between term and preterm infants, with and without bronchopulmonary dysplasia (BPD).
Main Methods:
- Assessed diaphragmatic function using Pdimax (strength) and PTIdi (load-to-capacity ratio) in 149 infants (56 term, 93 preterm).
- Compared measurements between term and preterm infants, and between preterm infants with and without BPD.
- Analyzed gestational age (GA) and duration of ventilation/oxygen support as predictors.
Main Results:
- Term infants had higher Pdimax and lower PTIdi than preterm infants without BPD.
- In infants without BPD, GA was the primary predictor of Pdimax and PTIdi.
- In very preterm infants (GA < 32 weeks), those with BPD showed significantly lower Pdimax and higher PTIdi compared to those without BPD.
Conclusions:
- Preterm infants have diminished diaphragmatic strength and endurance, predisposing them to fatigue.
- Bronchopulmonary dysplasia (BPD) may exacerbate impaired diaphragmatic function in very preterm infants.
Abstract:
We aimed to assess the determinants of diaphragmatic function in term and preterm infants. 149 infants (56 term; 93 preterm, of whom 14 were diagnosed with bronchopulmonary dysplasia-BPD) were studied before discharge. Diaphragmatic function was assessed by measurement of the maximum transdiaphragmatic pressure (Pdimax)-a measure of diaphragmatic strength, and the pressure-time index of the diaphragm (PTIdi)-a measure of the load-to-capacity ratio of the diaphragm. The Pdimax was higher in term than preterm infants without BPD (90.1 ± 16.3 vs 81.1 ± 11.8 cmH2O; P = 0.001). Term-born infants also had lower PTIdi compared to preterms without BPD (0.052 ± 0.014 vs 0.060 ± 0.017; P = 0.006). In term and preterm infants without BPD, GA was the most significant predictor of Pdimax and PTIdi, independently of the duration of mechanical ventilation and oxygen support. In infants with GA < 32 weeks (n = 30), the Pdimax was higher in infants without BPD compared to those with BPD (76.1 ± 11.1 vs 65.2 ± 11.9 cmH2O; P = 0.015). Preterms without BPD also had lower PTIdi compared to those with BPD (0.069 ± 0.016 vs 0.109 ± 0.017; P < 0.001). In this subgroup, GA was the only significant independent determinant of Pdimax, while BPD and the GA were significant determinants of the PTIdi. Conclusions: Preterm infants present lower diaphragmatic strength and impaired ability to sustain the generated force over time, which renders them prone to diaphragmatic fatigue. In very preterm infants, BPD may further aggravate diaphragmatic function. What is Known: • The diaphragm of preterm infants has limited capacity to undertake the work of breathing effectively. • The maximum transdiaphragmatic pressure (a measure of diaphragmatic strength) and the pressure-time index of the diaphragm (a measure of the load-to-capacity ratio of the muscle) have not been extensively assessed in small infants. What is New: • Preterm infants have lower diaphragmatic strength and impaired ability to sustain the generated force over time, which renders them prone to diaphragmatic fatigue. • In very preterm infants, bronchopulmonary dysplasia may further impair diaphragmatic function.

Related Concept Videos
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It...
 01:17
Pulmonary Cycle: Exhalation
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:05
Breathing
 01:26
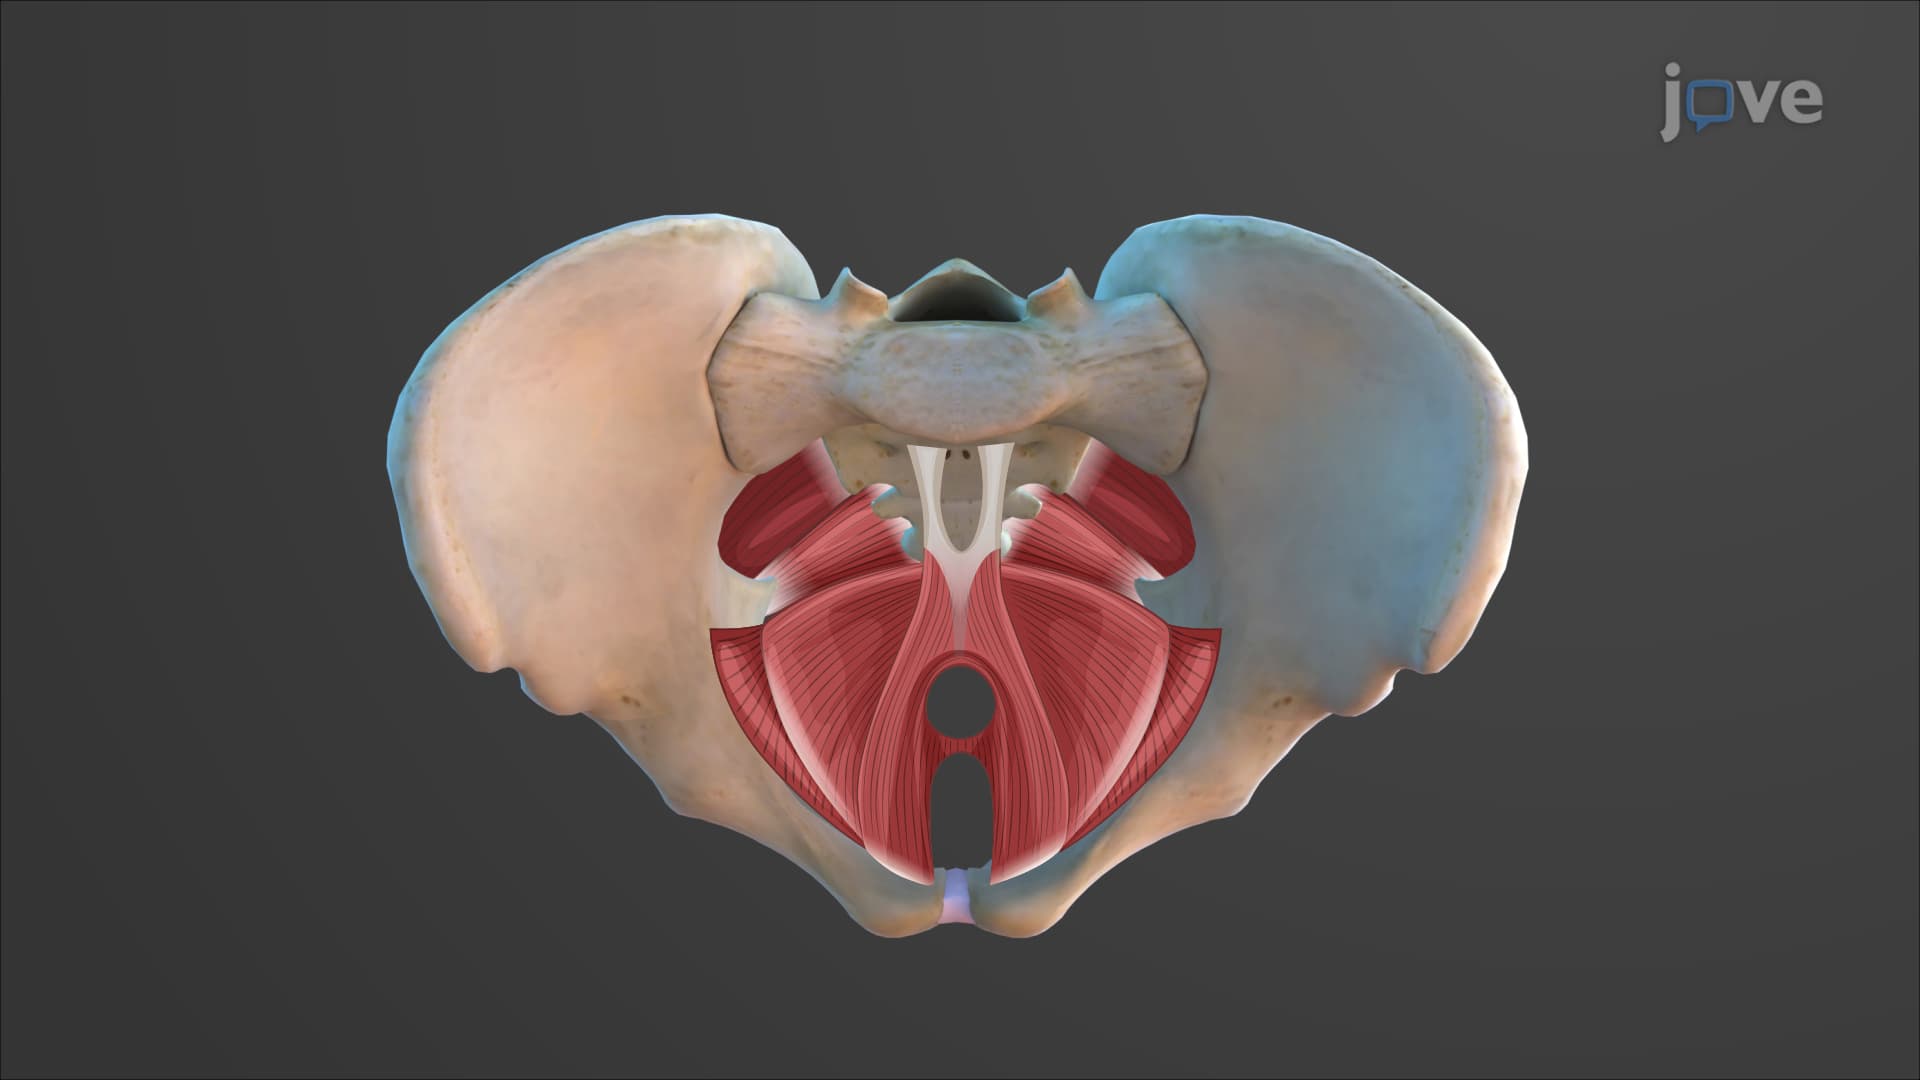
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...