Related Experiment Video
Updated: Jul 13, 2025
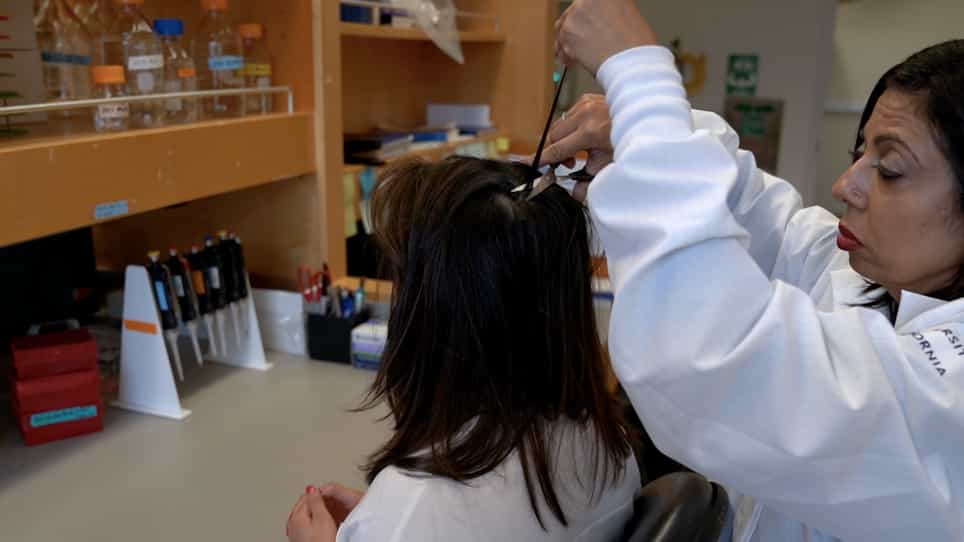

Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Risk factors for poor engagement with a smart pillbox adherence intervention among persons on tuberculosis treatment
Amare Worku Tadesse1, Martina Cusinato2,3, Gedion Teferra Weldemichael4
1TB Centre, Department of Infectious Disease Epidemiology, London, School of Hygiene & Tropical Medicine (LSHTM) , London, UK. amare.tadesse@lshtm.ac.uk.

Background:
Non-adherence to tuberculosis treatment increases the risk of poor treatment outcomes. Digital adherence technologies (DATs), including the smart pillbox (EvriMED), aim to improve treatment adherence and are being widely evaluated. As part of the Adherence Support Coalition to End TB (ASCENT) project we analysed data from a cluster-randomised trial of DATs and differentiated care in Ethiopia to examine individual-factors for poor engagement with the smart pillbox.
Methods:
Data were obtained from a cohort of trial participants with drug-sensitive tuberculosis (DS-TB) whose treatment started between 1 December 2020 and 1 May 2022, and who were using the smart pillbox. Poor engagement with the pillbox was defined as (i) > 20% days with no digital confirmation and (ii) the count of days with no digital confirmation, and calculated over a two evaluation periods (56-days and 168-days). Logistic random effects regression was used to model > 20% days with no digital confirmation and negative binomial random effects regression to model counts of days with no digital confirmation, both accounting for clustering of individuals at the facility-level.
Results:
Among 1262 participants, 10.8% (133/1262) over 56-days and 15.8% (200/1262) over 168-days had > 20% days with no digital confirmation. The odds of poor engagement was less among participants in the higher stratum of socio-economic position (SEP) over 56-days. Overall, 4,689/67,315 expected doses over 56-days and 18,042/199,133 expected doses over 168-days were not digitally confirmed. Compared to participants in the poorest SEP stratum, participants in the wealthiest stratum had lower rates of days not digitally confirmed over 168-days (adjusted rate ratio [RRa]:0.79; 95% confidence interval [CI]: 0.65, 0.96). In both evaluation periods (56-days and 168-days), HIV-positive status (RRa:1.29; 95%CI: 1.02, 1.63 and RRa:1.28; 95%CI: 1.07, 1.53), single/living independent (RRa:1.31; 95%CI: 1.03, 1.67 and RRa:1.38; 95%CI: 1.16, 1.64) and separated/widowed (RRa:1.40; 95%CI: 1.04, 1.90 and RRa:1.26; 95%CI: 1.00, 1.58) had higher rates of counts of days with no digital confirmation.
Conclusion:
Poorest SEP stratum, HIV-positive status, single/living independent and separated/ widowed were associated with poor engagement with smart pillbox among people with DS-TB in Ethiopia. Differentiated care for these sub-groups may reduce risk of non-adherence to TB treatment.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Drug Therapy
Antianxiety Medications
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: