Related Experiment Video
Updated: Jul 13, 2025

Retzius-Sparing Robot-Assisted Radical Prostatectomy
Published on: May 19, 2022
Resection rectopexy as part of the multidisciplinary approach in the management of complex pelvic floor disorders
Georgi Kalev1, Christoph Marquardt1, Marten Schmerer1
1Department of General, Visceral, Thoracic and Pediatric Surgery, Ludwigsburg Hospital, Ludwigsburg, Germany.

Objectives:
Pelvic floor disorders are frequently caused by an organ prolapse involving multiple pelvic floor compartments. In such cases, a multidisciplinary strategy for diagnostic work-up and therapy is required.
Methods:
All patients who underwent transabdominal rectopexy/resection rectopexy alone or in combination with simultaneous gynecological pelvic floor reconstruction at our institution between 01/2006 and 12/2021 were included in this retrospective study. The study aimed to evaluate the functional outcome and postoperative complications.
Results:
Two hundred and eighty seven patients were assigned to one of the following groups: PG1 - patient group one: after resection rectopexy (n=141); PG2 - after ventral rectopexy (n=8); PG3 - after combined resection rectopexy and sacro (cervico)colpopexy (n=62); PG4 - after combined resection rectopexy and trans-vaginal pelvic floor repair (n=76). The duration of follow-up was 14 months for PG1 (median, IQR 37 months), 11 months for PG2 (mean, SD 9 months), 7 months for PG 3 (median, IQR 33 months), and 12 months for PG 4 (median, IQR 51 Months). The surgical procedure resulted in improvement of symptoms related to obstructed defecation in 56.4 % (22/39) of the patients in PG1, 25 % in PG2 (1/4), 62.5 % (20/32) in PG3, and 71.8 % (28/39) in PG4. "De novo" constipation was reported by 2.4 % (2/141) of patients from PG1. Improvement in fecal incontinence symptoms was reported by 69 % (40/58) of patients in PG1, 100 % in PG2 (2/2), 93.1 % (27/29) in PG3, and 87.2 % (34/39) in PG4. The recurrence rate for external rectal prolapse was 7.1 % in PG1, 50 % in PG2 (1/2), 2.7 % in PG3, and 6.3 % in PG4. A significant difference in terms of severe morbidity (grade ≥ IIIb) and mortality could not be determined between the non-interdisciplinary (PG1 with PG2) and interdisciplinary surgery (PG3 with PG4) (p=0.88, p=0.499).
Conclusions:
Based on our results, we can assume that combined surgery is as feasible as rectal surgery alone. In our study, combined interventions were effective and not associated with an increased risk of postoperative complications.
More Related Videos
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
 03:30
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
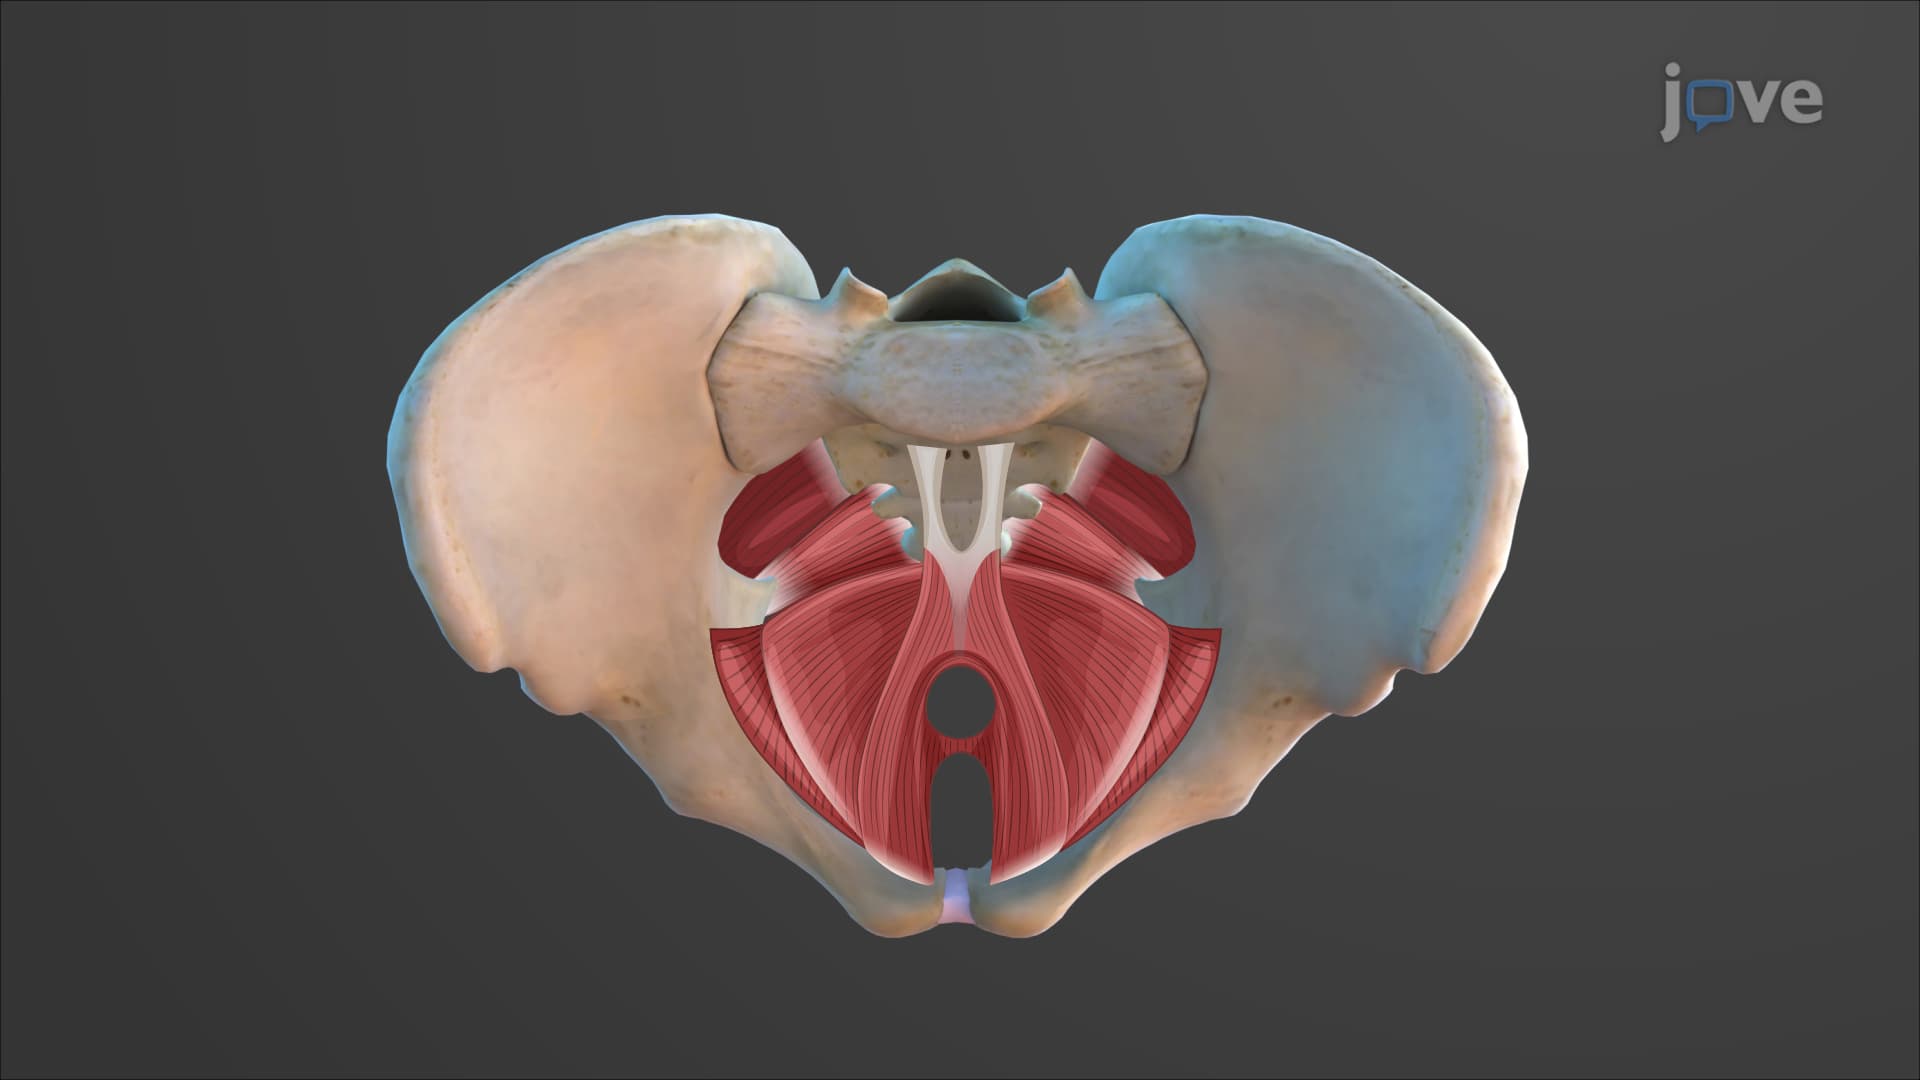
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:25
Urinary Tract Calculi VI: Surgical Management