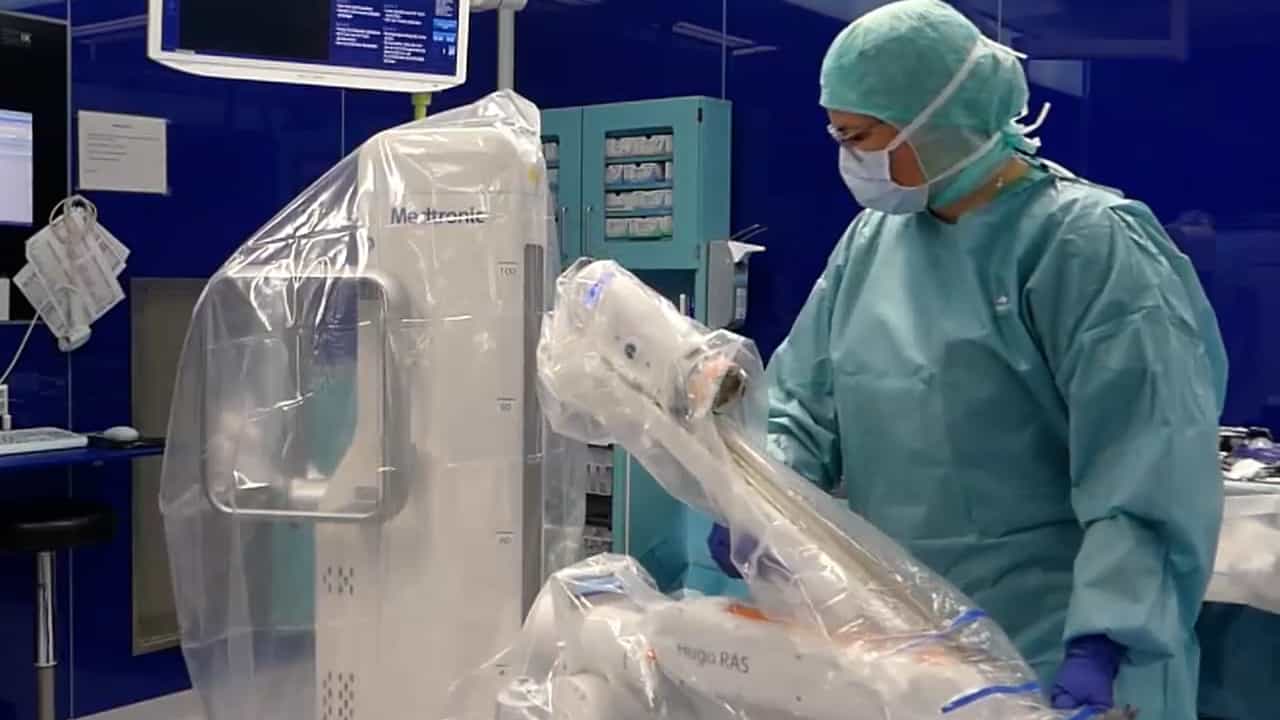
Related Experiment Video
Updated: Jul 9, 2026


Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Robotic Heller's cardiomyotomy for achalasia: early outcomes for a high-volume UK centre
E J Nevins1, K Greene1, S Bawa1
1Northumbria Healthcare NHS Foundation Trust, UK.

Insights
Robotic Heller
Area of Science:
- Gastroenterology
- Surgical Innovation
- Minimally Invasive Surgery
Background:
- Heller's cardiomyotomy (HCM) is the standard treatment for achalasia.
- Laparoscopic HCM has high rates of oesophageal mucosal perforation.
- Robotic-assisted surgery offers potential advantages in precision.
Purpose of the Study:
- To evaluate short-term complications and outcomes of robotic-assisted HCM.
- To assess the initial experience in a UK high-volume centre.
Main Methods:
- Prospective case series of 13 patients undergoing robotic HCM.
- Outcomes measured by the Eckhard score post-operation.
Main Results:
- No intraoperative oesophageal perforations occurred.
- All patients showed symptom improvement with Eckhard scores < 3.
- Low complication rate, with one instance of urinary retention.
Conclusions:
- Robotic HCM demonstrates an excellent safety profile.
- High symptom resolution rates achieved early in the learning curve.
- Potential for reduced mucosal damage and improved myotomy precision compared to laparoscopy.
Introduction:
Heller's cardiomyotomy (HCM) is the gold standard treatment for achalasia. Laparoscopic HCM has been shown to be effective with low rates of symptom recurrence, though oesophageal mucosal perforation rates remain high. The aim of this prospective case series is to assess the short-term complication rates and perioperative outcomes for the first cohort of patients undergoing robotic-assisted HCM for achalasia in a single high-volume UK centre.
Methods:
Data were collected from a prospective cohort of patients who underwent robotic HCM at a single high-volume UK centre. Outcomes were assessed using the Eckhard score, which was calculated after their routine postoperative clinic appointments.
Results:
Thirteen patients underwent robotic HCM during the study period; this is the second largest reported case series in the European literature. There were no intraoperative oesophageal perforations. Six patients were discharged as day cases, six patients were discharged on the first postoperative day and one patient's hospital stay was two nights. There was a single perioperative complication of urinary retention. All patients reported improvement of symptoms following their operation, and all had a postoperative Eckhard score of less than 3, indicating their achalasia was in remission.
Conclusions:
This cohort has demonstrated that robotic HCM has an exceptional safety profile and results in high levels of symptom resolution, even early in the learning curve. The robotic approach may be superior to laparoscopy as it allows more precise identification and dissection of the oesophageal muscle fibres, which likely reduces the risk of inadvertent mucosal damage or incomplete myotomy.