Related Experiment Video
Updated: Jul 13, 2025
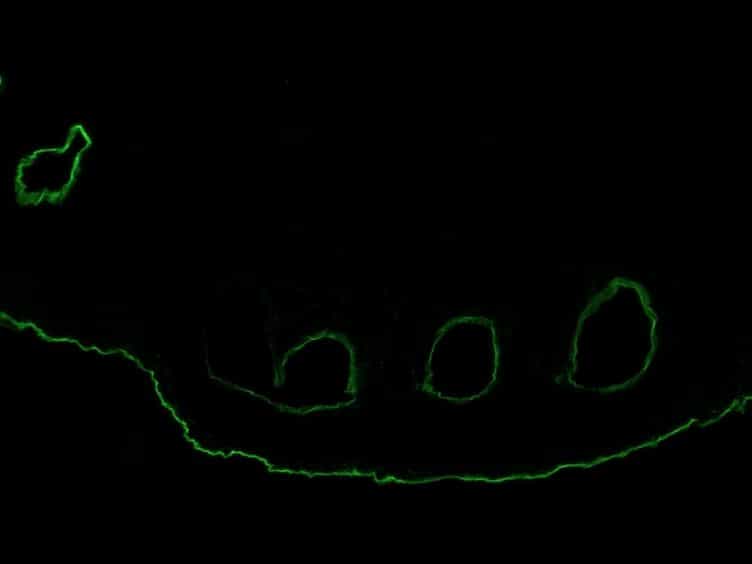

Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
[Management of bullous pemphigoid and mucous membrane pemphigoid]
Johannes S Kern1, Silke C Hofmann2
1Department of Dermatology, Alfred Hospital, Central Clinical School, Monash University, 55 Commercial Road, 3004, Melbourne Victoria, Australien. j.kern@alfred.org.au.

Background:
Bullous pemphigoid (BP) is the most common blistering autoimmune dermatosis and, as an age-associated disease, is also the bullous dermatosis with the highest increase in incidence in recent years due to demographic developments. Mucous membrane pemphigoid (MMP), which is less common, is a clinically and immunopathologically heterogeneous blistering autoimmune dermatosis characterized by blisters and erosions on mucous membranes.
Objective:
This work summarizes the manifold clinical characteristics of both diseases and provides an up-to-date overview of diagnostics and therapy of BP and SHP.
Materials And Methods:
A selective literature search was carried out.
Results:
While eczematous, urticarial, or bullous lesions on the integument are typical for BP, MMP is characterized by pronounced, erosive mucosal changes orally, ocularly, genitoanally, tracheally or esophageally and, at most, only minor skin involvement. For diagnosis, the combination of histology, direct immunofluorescence microscopy, and serological detection of autoantibodies against the hemidesmosomal proteins BP180 and BP230 and, in MMP, also against laminin 332 is important. New pathophysiological findings and therapeutics have recently significantly expanded the range of treatment options.
Conclusion:
Due to the comorbidities of the usually elderly BP patients and the often multiple affected mucous membranes in MMP, with the risk of developing irreversible complications such as strictures and synechiae, interdisciplinary diagnosis and therapy is often required.

Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:29
Inflammatory Bowel Disease IV: Pharmacological Management
Pharmacologic...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: