Related Experiment Video
Updated: Jul 12, 2025
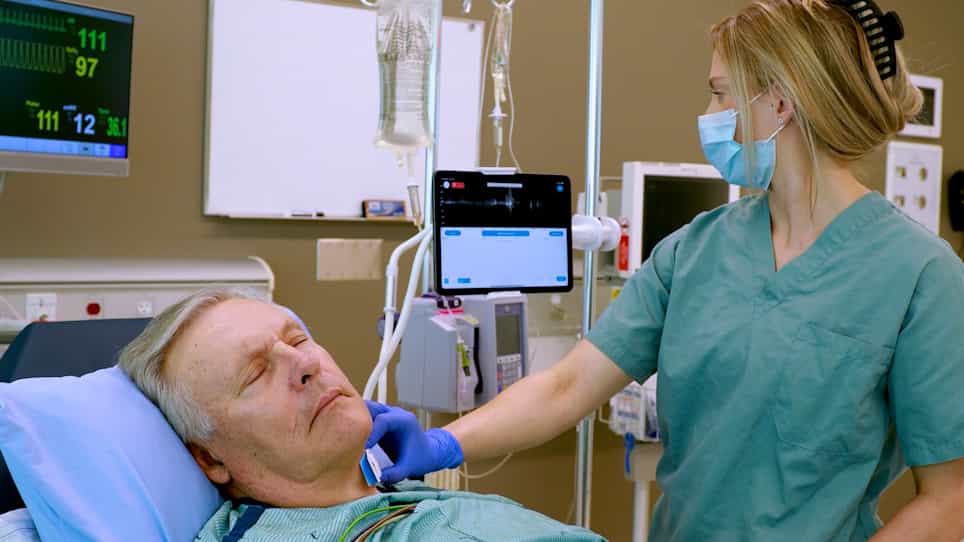
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Passive leg raising test induced changes in plethysmographic variability index to assess fluid responsiveness in
Jihad Mallat1, Malcolm Lemyze2, Marc-Olivier Fischer3
1Department of Critical Care Medicine, Arras Hospital, 6200 Arras, France; Critical Care Institute, Cleveland Clinic Abu Dhabi, Abu Dhabi, United Arab Emirates; Cleveland Clinic Lerner College of Medicine of Case Western Reserve University, Cleveland, OH, USA; Normandy University, UNICAEN, ED 497, Caen, France.

Background:
Passive leg raising (PLR) reliably predicts fluid responsiveness but requires a real-time cardiac index (CI) measurement or the presence of an invasive arterial line to achieve this effect. The plethysmographic variability index (PVI), an automatic measurement of the respiratory variation of the perfusion index, is non-invasive and continuously displayed on the pulse oximeter device. We tested whether PLR-induced changes in PVI (ΔPVIPLR) could accurately predict fluid responsiveness in mechanically ventilated patients with acute circulatory failure.
Methods:
This was a secondary analysis of an observational prospective study. We included 29 mechanically ventilated patients with acute circulatory failure in this study. We measured PVI (Radical-7 device; Masimo Corp., Irvine, CA) and CI (Echocardiography) before and during a PLR test and before and after volume expansion of 500 mL of crystalloid solution. A volume expansion-induced increase in CI of >15% defined fluid responsiveness. To investigate whether ΔPVIPLR can predict fluid responsiveness, we determined areas under the receiver operating characteristic curves (AUROCs) and gray zones for ΔPVIPLR.
Results:
Of the 29 patients, 27 (93.1%) received norepinephrine. The median tidal volume was 7.0 [IQR: 6.6-7.6] mL/kg ideal body weight. Nineteen patients (65.5%) were classified as fluid responders (increase in CI > 15% after volume expansion). Relative ΔPVIPLR accurately predicted fluid responsiveness with an AUROC of 0.89 (95%CI: 0.72-0.98, p < 0.001). A decrease in PVI ≤ -24.1% induced by PLR detected fluid responsiveness with a sensitivity of 95% (95%CI: 74-100%) and a specificity of 80% (95%CI: 44-97%). Gray zone was acceptable, including 13.8% of patients. The correlations between the relative ΔPVIPLR and changes in CI induced by PLR and by volume expansion were significant (r = -0.58, p < 0.001, and r = -0.65, p < 0.001; respectively).
Conclusions:
In sedated and mechanically ventilated ICU patients with acute circulatory failure, PLR-induced changes in PVI accurately predict fluid responsiveness with an acceptable gray zone.
Trial Registration:
ClinicalTrials.govNCT03225378.
More Related Videos
 14:28
Non-Invasive Monitoring of Microvascular Oxygenation and Reactive Hyperemia using Hybrid, Near-Infrared Diffuse Optical Spectroscopy for Critical Care
Published on: May 10, 2024
 05:56
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:30
Acute Respiratory Failure-III
 01:29
Mechanical Ventilation I: Indication and Settings