Related Experiment Video
Updated: Jul 12, 2025
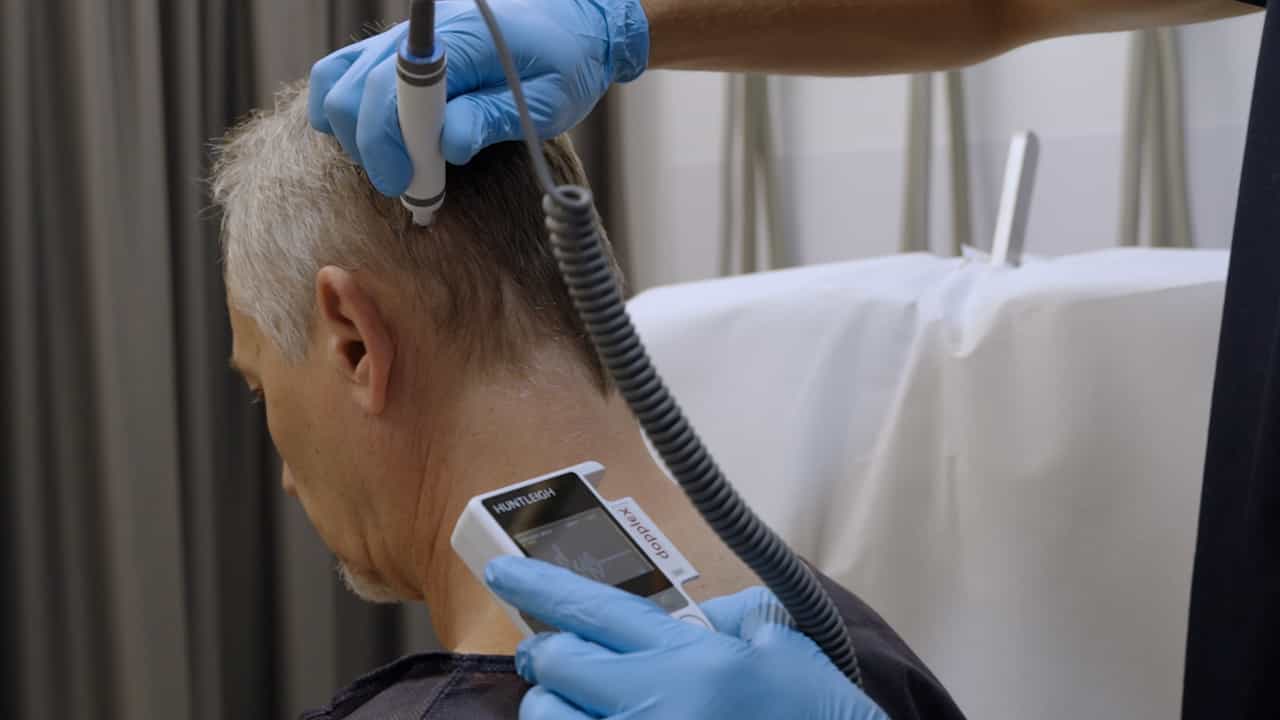

Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
Sphenopalatine ganglion blocks for post-dural puncture headache: A case report in a 3-year-old child
Anisa Bhettay1, Roxanne Burger2
1Red Cross War Memorial Children's Hospital, Division of Paediatric Anaesthesia, Department of Anaesthesia and Perioperative Medicine, University of Cape Town, Cape Town, South Africa.

Insights
Post-dural puncture headache (PDPH) can occur after lumbar punctures. Sphenopalatine ganglion blocks offer a minimally invasive alternative for managing severe PDPH, especially postoperatively.
Area of Science:
- Neurology
- Anesthesiology
- Pain Management
Background:
- Post-dural puncture headache (PDPH) is a significant complication following dural puncture procedures.
- The incidence and specific risk factors in pediatric populations remain unclear.
- Current management ranges from conservative measures to invasive procedures like epidural blood patch.
Observation:
- Greater occipital nerve blocks and sphenopalatine ganglion blocks (SPGBs) have emerged as successful interventions.
- SPGBs are minimally invasive and technically straightforward to perform.
- These blocks are particularly relevant in postoperative patients receiving epidural analgesia.
Findings:
- SPGBs provide a viable, less invasive alternative to epidural blood patches for refractory PDPH.
- The ease of performance and minimal invasiveness make SPGBs an attractive option.
Implications:
- SPGBs represent a promising therapeutic option for managing severe PDPH, especially in specific clinical settings.
- Further research may elucidate the full potential of nerve blocks in PDPH management.
- Consideration of SPGBs could improve patient outcomes and reduce the need for more invasive treatments.
Abstract:
Post-dural puncture headache is a distressing complication that may occur after lumbar puncture or unintentional dural puncture. Risk factors in the pediatric population have not been well elicited, and the true incidence is unknown. Conservative management includes conservative physical measures and medical therapies. Epidural blood patch remains the gold standard for managing severe refractory headache, but greater occipital nerve blocks and sphenopalatine ganglion blocks have been used with success. Sphenopalatine ganglion blocks are easy to perform, minimally invasive and, in the postoperative setting where epidural analgesia is utilized, provide an alternative that should be considered.


