Related Experiment Video
Updated: Jul 12, 2025
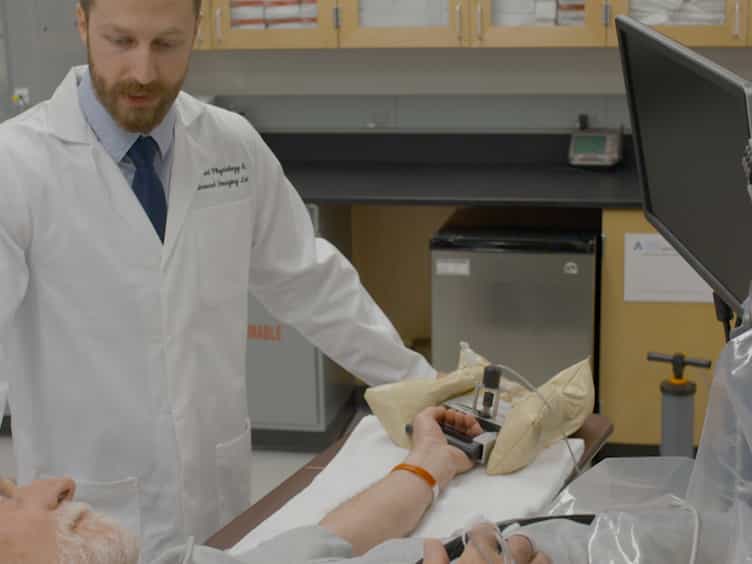

Skeletal Muscle Neurovascular Coupling, Oxidative Capacity, and Microvascular Function with 'One Stop Shop' Near-infrared Spectroscopy
Published on: February 20, 2018
Contribution of reduced skeletal muscle perfusion reserve to exercise intolerance in heart failure with preserved
Adam Serafin1, Ewelina Jasic-Szpak1, Thomas H Marwick2
1Institute of Heart Diseases, Wroclaw Medical University, Borowska 213, 50-556 Wroclaw, Poland.

Background:
Skeletal muscle (SM)-associated mechanisms of exercise intolerance in HFpEF are insufficiently defined, and inadequate augmentation of SM blood flow during physical effort may be one of the contributors. Therefore, we sought to investigate the association of SM perfusion response to exertion with exercise capacity in this clinical condition.
Methods:
Echocardiography and SM microvascular perfusion by contrast-enhanced ultrasound were performed at rest and immediately post-exercise test in 77 HFpEF patients in NYHA class II and III, and in 25 subjects with normal exercise tolerance (stage B). Exercise reserve of cardiac function and SM perfusion was calculated by subtracting resting value from exercise value.
Results:
In addition to decreased cardiac functional reserve, HFpEF patients demonstrated significantly reduced SM perfusion reserve as compared to HF stage B, with the degree of impairment being greater in the subgroup with more profound left ventricular (LV) diastolic abnormalities (E/e' > 15 and TRV > 2.8 m/s). SM perfusion reserve was significantly associated with exercise capacity (beta = 0.33; SE 0.11; p = 0.003), cardiac output reserve (beta = 0.24; SE 0.12; p = 0.039), resting E/e' (beta = -0.33; SE 0.11; p = 0.006), and patient frailty expressed by the PRISMA 7 score (beta = -0.30; SE 0.11; p = 0.008). In multivariable analysis including clinical, demographic and cardiac functional variables, SM perfusion reserve was in addition to patient frailty, sex and LV longitudinal strain reserve among the independent correlates of exercise capacity.
Conclusions:
SM perfusion reserve is impaired in HFpEF, and is associated with reduced exercise capacity independent of clinical, demographic and "central" cardiac factors. This supports the need to consider the SM domain in patient management strategies in HFpEF.
More Related Videos
 04:20
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:17
Pathophysiology of Heart Failure
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:29
Pathophysiology of Cardiac Performance
 01:29
Heart Failure II: Pathophysiology
 01:27
Heart Failure I: Introduction