Related Experiment Video
Updated: Jul 12, 2025

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Obstetric operating room staffing and operating efficiency using queueing theory
Grace Lim1,2, Annamarie J Lim3, Beth Quinn4
1Department of Anesthesiology & Perioperative Medicine, University of Pittsburgh, 300 Halket Street #3510, Pittsburgh, PA, 15215, USA. Limkg2@upmc.edu.

Introduction:
Strategies to achieve efficiency in non-operating room locations have been described, but emergencies and competing priorities in a birth unit can make setting optimal staffing and operation benchmarks challenging. This study used Queuing Theory Analysis (QTA) to identify optimal birth center operating room (OR) and staffing resources using real-world data.
Methods:
Data from a Level 4 Maternity Center (9,626 births/year, cesarean delivery (CD) rate 32%) were abstracted for all labor and delivery operating room activity from July 2019-June 2020. QTA has two variables: Mean Arrival Rate, λ and Mean Service Rate µ. QTA formulas computed probabilities: P0 = 1-(λ/ µ) and Pn = P0 (λ/µ)n where n = number of patients. P0…n is the probability there are zero patients in the queue at a given time. Multiphase multichannel analysis was used to gain insights on optimal staff and space utilization assuming a priori safety parameters (i.e., 30 min decision to incision in unscheduled CD; ≤ 5 min for emergent CD; no greater than 8 h for nil per os time). To achieve these safety targets, a < 0.5% probability that a patient would need to wait was assumed.
Results:
There were 4,017 total activities in the operating room and 3,092 CD in the study period. Arrival rate λ was 0.45 (patients per hour) at peak hours 07:00-19:00 while λ was 0.34 over all 24 h. The service rate per OR team (µ) was 0.87 (patients per hour) regardless of peak or overall hours. The number of server teams (s) dedicated to OR activity was varied between two and five. Over 24 h, the probability of no patients in the system was P0 = 0.61, while the probability of 1 patient in the system was P1 = 0.23, and the probability of 2 or more patients in the system was P≥2 = 0.05 (P3 = 0.006). However, between peak hours 07:00-19:00, λ was 0.45, µ was 0.87, s was 3, P0 was 0.48; P1 was 0.25; and P≥2 was 0.07 (P3 = 0.01, P4 = 0.002, P5 = 0.0003).
Conclusion:
QTA is a useful tool to inform birth center OR efficiency while upholding assumed safety standards and factoring peaks and troughs of daily activity. Our findings suggest QTA is feasible to guide staffing for maternity centers of all volumes through varying model parameters. QTA can inform individual hospital-level decisions in setting staffing and space requirements to achieve safe and efficient maternity perioperative care.
More Related Videos
 09:52
Setting Up a Stroke Team Algorithm and Conducting Simulation-based Training in the Emergency Department - A Practical Guide
Published on: January 15, 2017
 09:51
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant,...
 01:01
Production Efficiency
 01:30
Health Information Technology and Healthcare Information System
Health Information Technology, commonly called HIT, integrates advanced information systems and technology in healthcare settings. Its primary functions include:
 01:12
Column Efficiency: Rate Theory
During elution, a solute molecule experiences numerous transitions between stationary and mobile phases, exhibiting irregular residence times in...
 01:13
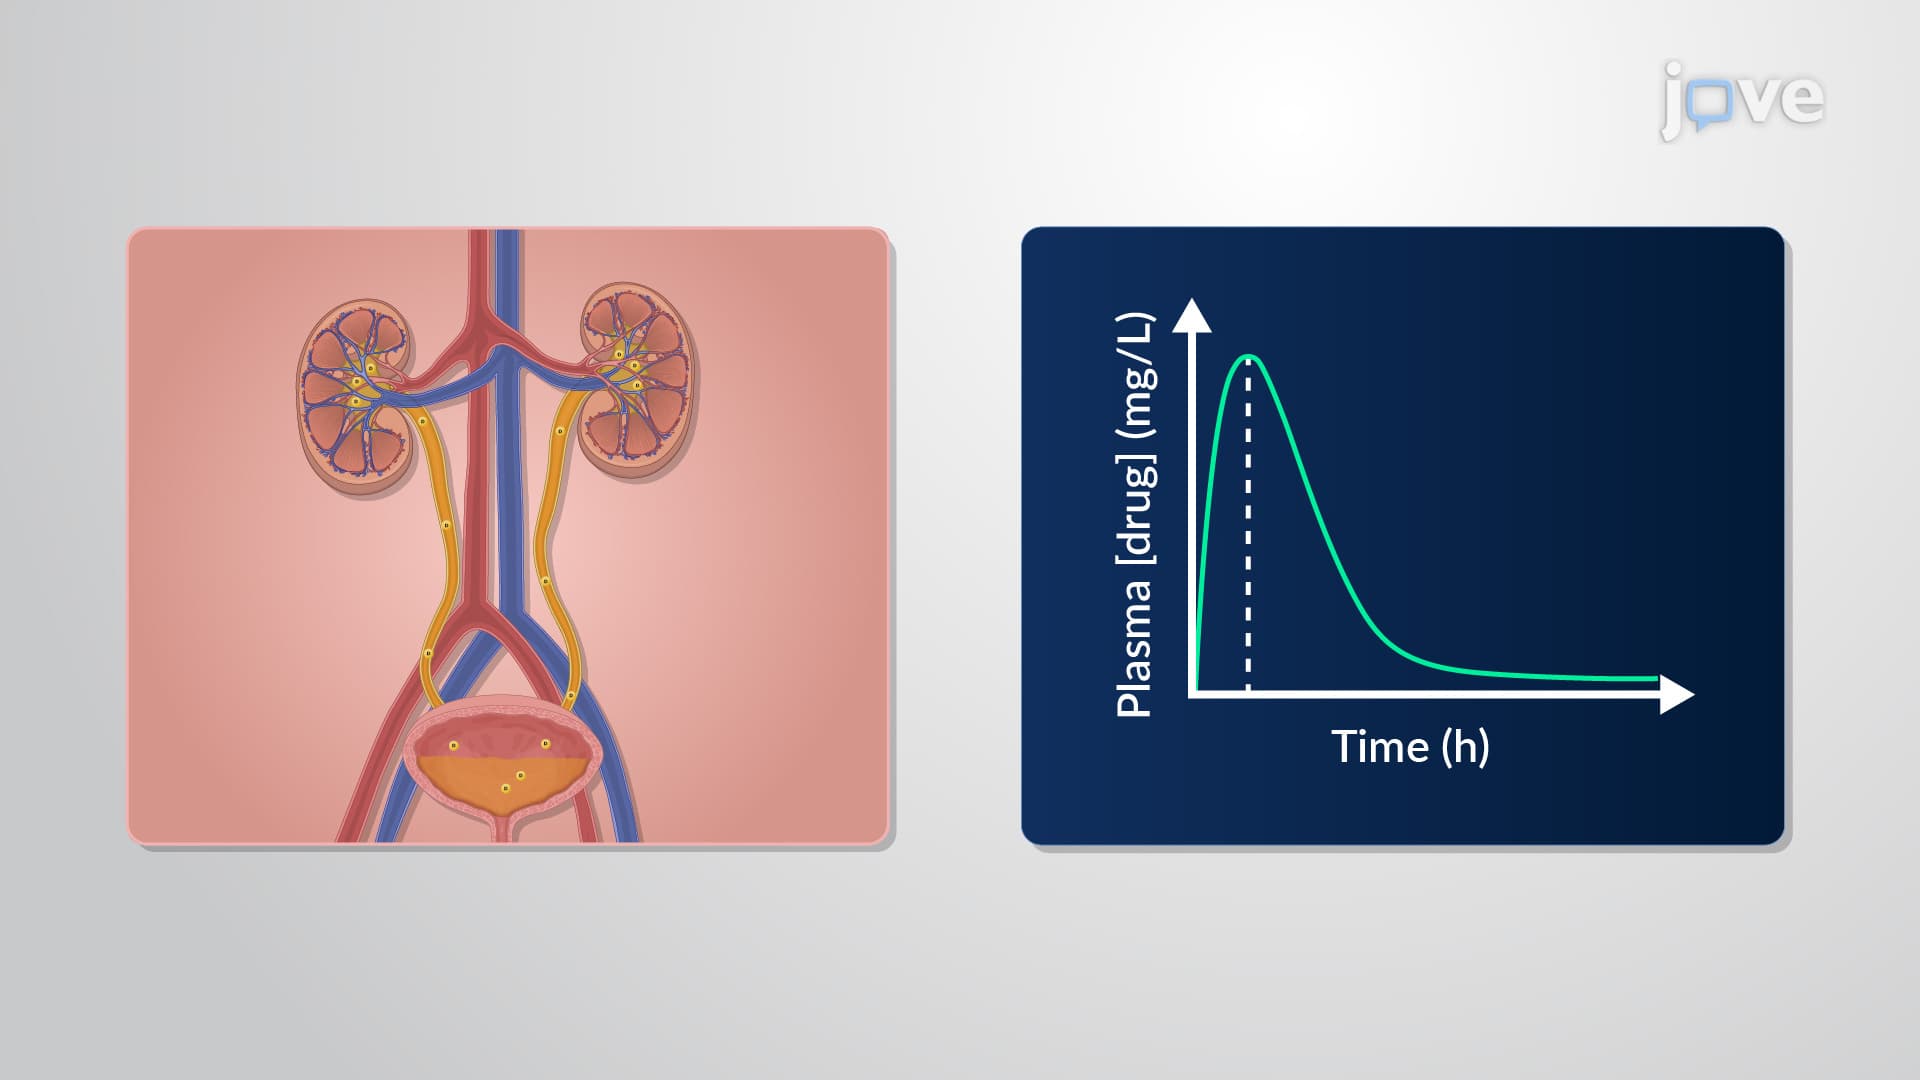
Parameters Affecting Nonlinear Elimination: Zero-Order Input, First-Order Absorption and Two-Compartment Model
When a drug is administered through a constant intravenous infusion and eliminated via nonlinear pharmacokinetics, it follows zero-order input. For example, oral drugs undergo first-order absorption upon administration and are eliminated through nonlinear pharmacokinetics.
In the case of subcutaneously administered drugs,...